+91 83682 47758
info@medivisorhealth.com
Medivisor India Treatment Logo
  • Home
    • About Us
    • Our Services
    • Our Team
    • Our Safety Measures
    • Loading treatments...
    • Loading hospitals...
    • Loading doctors...
    • Loading tests & diagnoses...
    • Treatment Cost
    • Treatment Process
    • Visa Process
    • Travel Guide
    • FAQs
    • Why Medivisor
    • Success Stories
    • Patient Activities
    • Social Activities
    • News Coverage
    • Blog
  • Become a Partner

Medivisor India Treatment is a trusted New Delhi-based medical travel company assisting international patients with advanced, affordable, and seamless treatment in India.

  • Medivisor House 359, Sector 1, Vaishali, Ghaziabad, (Delhi/NCR) India
  • +91 8368 247 758
  • info@medivisorhealth.com

About Us

  • About Us
  • Our Services
  • Our Team
  • Our Medical Advisors
  • Our Safety Measures
  • Join Our Network
  • Contact Us

India Treatment

  • Hospitals
  • Treatments
  • Treatment Cost
  • Treatment Process
  • Visa Process
  • Travel Guide
  • FAQs
  • Why Medivisor

Gallery

  • Patient Testimonials
  • Patient Activities
  • News Coverage
  • Blog

Get in Touch

© 2026 Medivisor India Treatment. All rights reserved.

Apollo Hospital, Financial District

Apollo Hospital, Financial District

D.No‑2‑105/6/SE, Financial District, Nanakramguda Serilingampally, Hyderabad, Telangana 500032

  1. Home
  2. Hospitals
  3. Apollo Hospital, Financial District

Quick Overview

2026

Established

Super

Speciality

400

Beds

110

Doctors

Top Multispeciality Hospital in Financial District, Hyderabad, India

Apollo Hospitals Financial District is a premier Super Specialty Hospital and Quaternary care centre designed to serve Hyderabad’s thriving IT and corporate ecosystem in the heart of Gachibowli. This state-of-the-art facility delivers precision care across all specialties powered by cutting-edge technology—such as AI-driven diagnostics, robotic-assisted surgeries, next-generation Advanced ICUs, and high-definition imaging—for faster, more accurate outcomes and minimally invasive procedures.

Advanced Medical Care

The institution seamlessly blends world-class specialist expertise with an advanced digital infrastructure and integrated electronic health systems to function as a fully equipped smart hospital. Focused on delivering innovative, precise, and compassionate care, the facility is strategically optimized to address the healthcare requirements of corporate professionals and families within the tech corridor.

Hospital at a Glance

  • Serves as a premier Super Specialty Hospital and Quaternary care centre in the heart of Gachibowli.

  • Designed to cater to the healthcare needs of Hyderabad’s thriving IT and corporate ecosystem.

  • Powered by cutting-edge medical technology including AI-driven diagnostics and robotic-assisted surgeries.

  • Features integrated electronic health systems and next-generation Advanced ICUs for precise and efficient outcomes.
May we help you?

Enter digits only (6-15 digits). We'll add your country code.

Apollo Hospital, Financial District

Neck Lift
Neck Lift

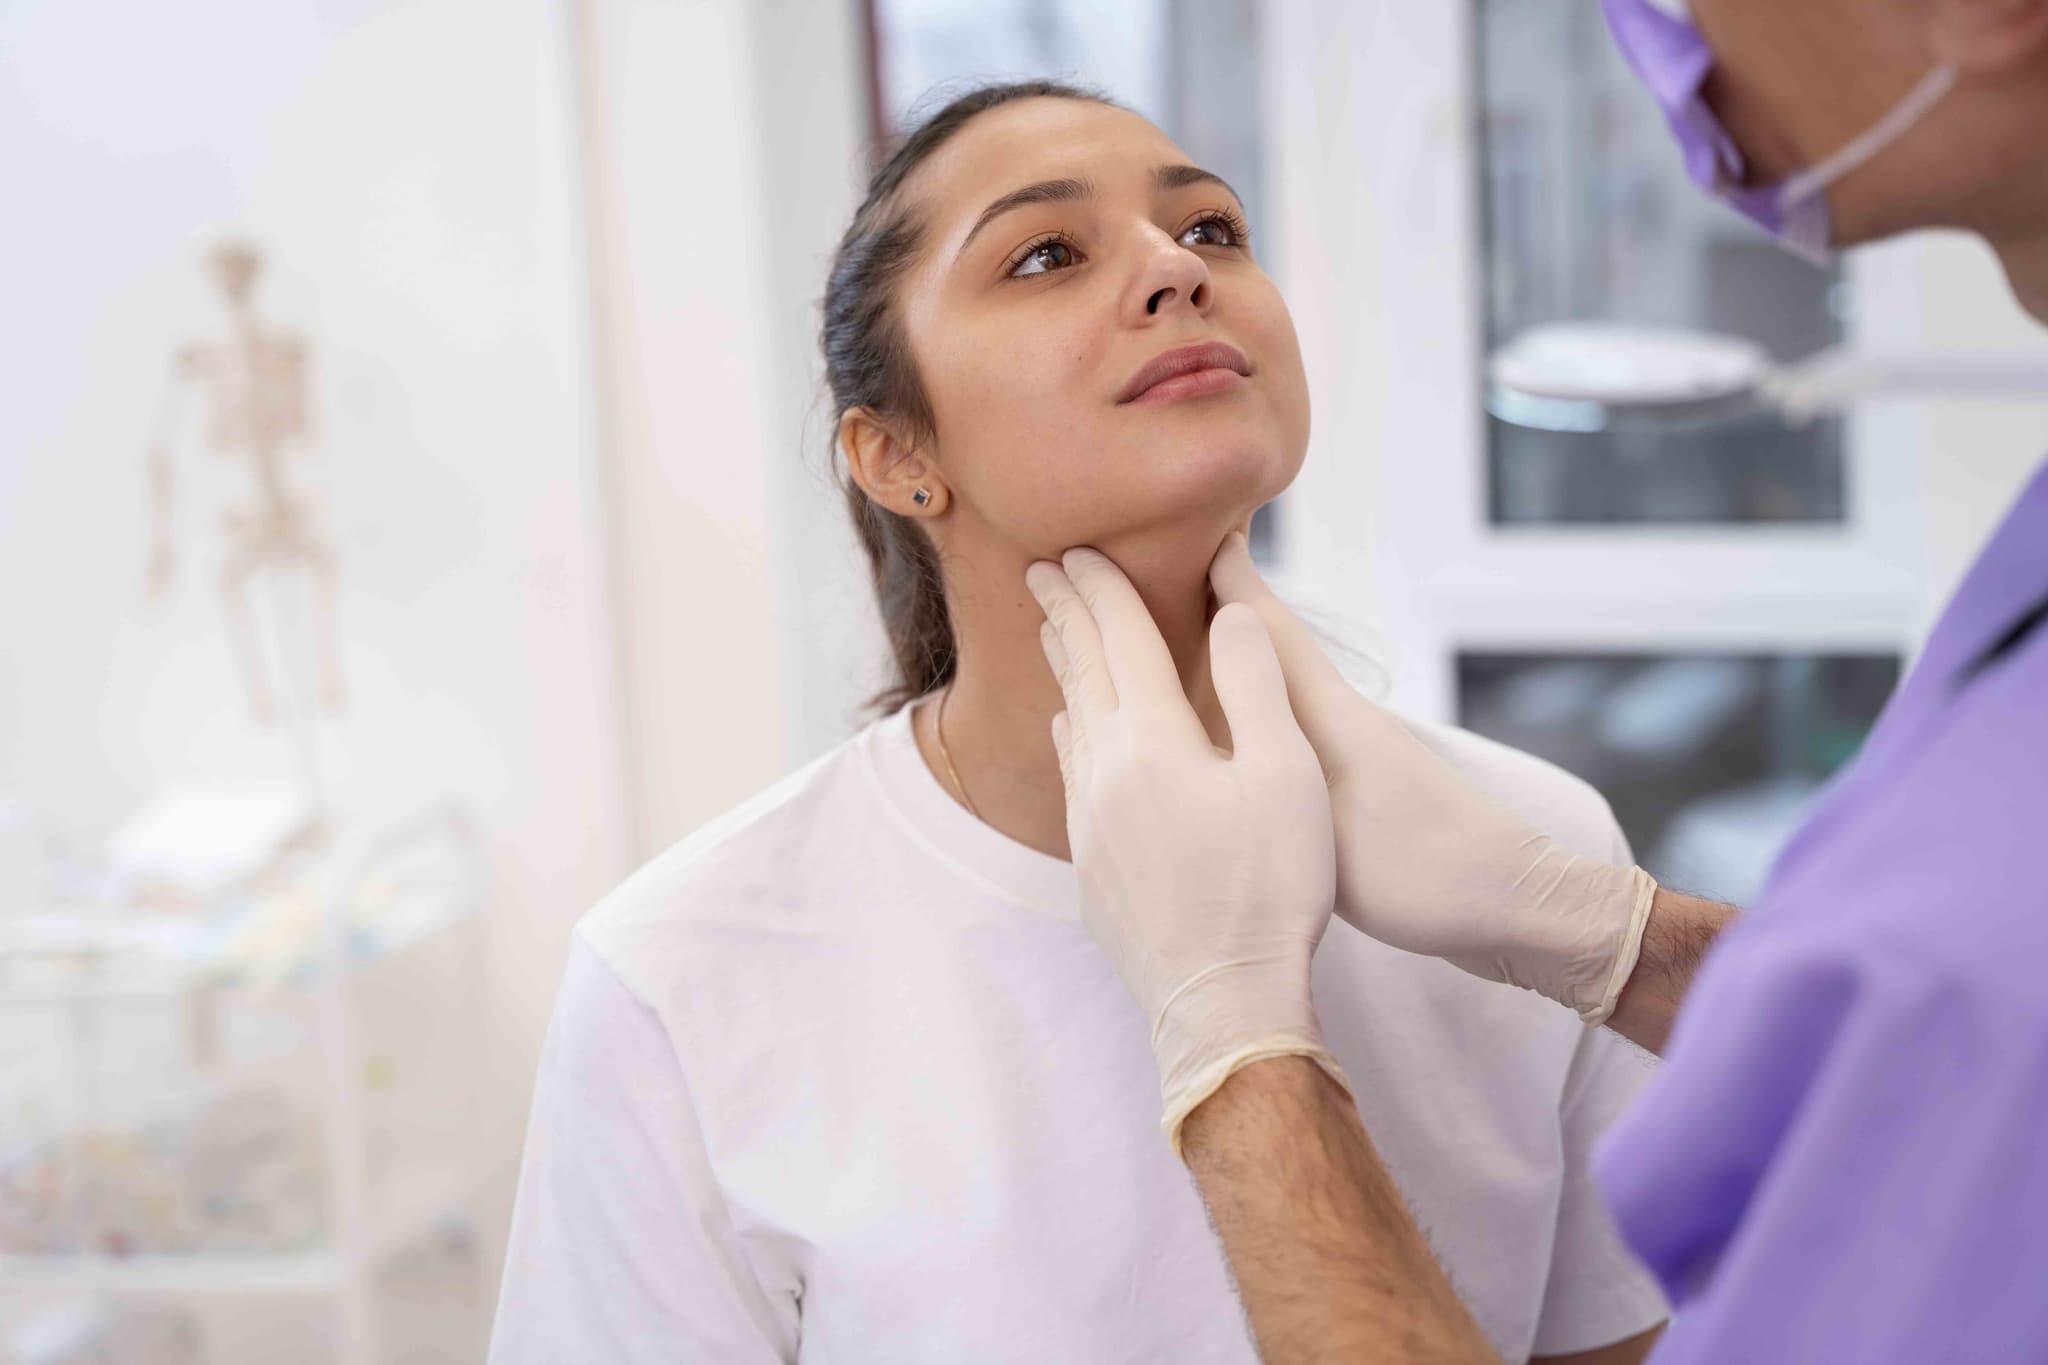
A neck lift, or lower rhytidectomy, is a surgical procedure designed to enhance the appearance of the neck and jawline by addressing the visible signs of aging. In 2026, it remains a primary solution for those seeking to correct skin laxity, muscle banding, and fat accumulation that does not respond to non-invasive treatments.

  • To address loose skin, often referred to as a "turkey wattle," where the skin has lost elasticity and hangs below the jaw.

  • If you have vertical cords or muscle banding caused by the weakening or protrusion of the platysma muscle.

  • To remove submental fat or excess fat deposits under the chin (double chin) and along the jowls.

  • When looking for long-lasting results that typically maintain a youthful profile for 10 to 15 years.

  • If non-invasive treatments have failed to provide the desired contour for the neck and jawline.

  • Platysmaplasty: A technique where the surgeon accesses neck muscles via small incisions to tighten and "sew" them together like a corset.

  • Cervicoplasty: A process focusing on the removal of excess skin, which is then re-draped and trimmed to create a sharper jaw angle.

  • Liposuction: Often performed alongside a lift to remove localized fat and refine the overall neck contour.

  • Combined Procedures: The surgery may be performed alone or in conjunction with a facelift or brow lift for comprehensive rejuvenation.

  • Anesthesia: The procedure is usually performed under general anesthesia or intravenous sedation.

  • Incisions: Standard incisions begin in front of the earlobe, wrap behind the ear, and end in the posterior scalp to hide scars in natural creases.

  • Surgical Access: Small incisions may also be made under the chin to access the platysma muscles directly.

  • Tissue Adjustment: Muscles are tightened, fat is removed or repositioned, and excess skin is trimmed away.

  • Duration: The surgical process typically takes between 2 to 4 hours depending on the complexity of the case.

  • Consult with a surgeon to determine if the anatomy requires platysmaplasty, cervicoplasty, or liposuction.

  • Discuss medical history and potential risks such as hematoma or nerve injury.

  • Arrange for a recovery period, as patients usually need 10 to 14 days off from sedentary work.

  • Follow specific instructions regarding fasting and medication adjustments before anesthesia.

  • Plan for post-operative support and a support person to assist during the first few days of recovery.

  • Physical Evaluation: To assess skin elasticity, muscle banding, and the degree of fat accumulation.

  • Medical Clearance: Standard pre-surgical tests to ensure the patient is fit for general anesthesia or sedation.

  • Anatomical Mapping: Determining incision placement based on the patient's hairline and natural skin creases.

  • Wear a compression bandage around the head and neck for several days to support new contours and minimize swelling.

  • Manage initial swelling and bruising, which typically peak around the third day post-operation.

  • Resume sedentary work and normal daily activities within 10 to 14 days.

  • Avoid strenuous physical activity and heavy lifting for at least 4 to 6 weeks to ensure proper healing.

  • Monitor for rare complications such as temporary numbness or weakness in the lower lip during the recovery process.

  • Provides a firmer, smoother foundation by tightening the underlying neck muscles.

  • Creates a sharper, more defined angle between the neck and the jawline.

  • Delivers significant improvement in appearance that can last between 10 to 15 years.

  • Corrects structural issues like muscle banding that non-surgical methods cannot reach.

  • Offers well-hidden scarring by utilizing natural creases and the hairline for incision placement.

Injectable Filler / Lip Augmentation

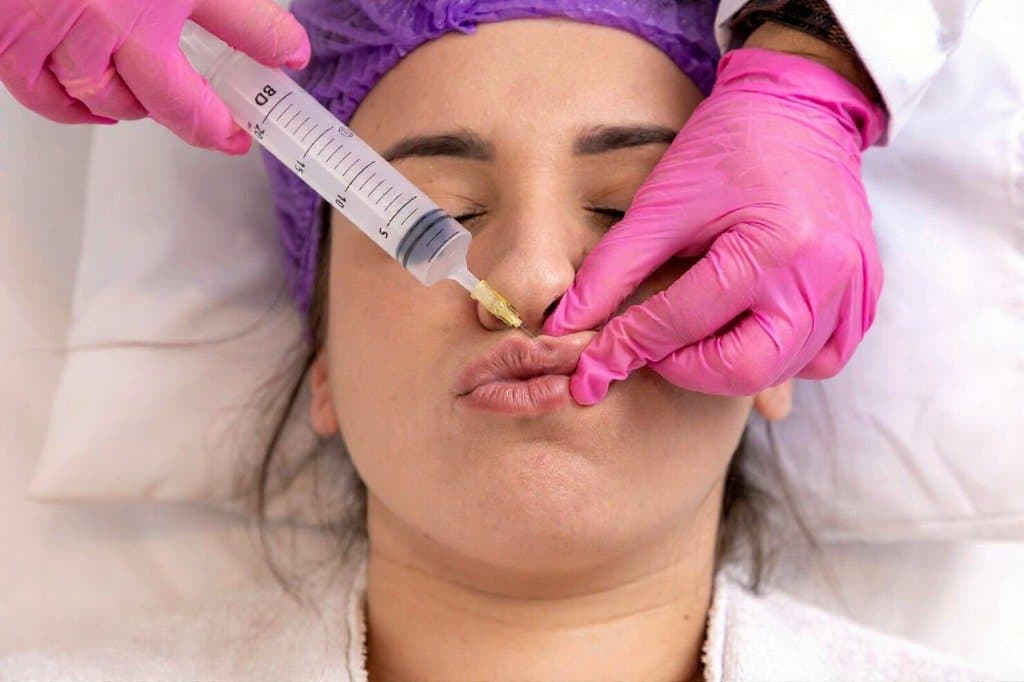
Injectable Fillers are the primary non-surgical method in 2026 for restoring volume, smoothing deep wrinkles, and enhancing facial features. Lip Augmentation remains the most requested filler procedure, focusing on achieving natural "pillowy" textures rather than overfilled results.

  • To add volume to naturally thin or thinning lips.

  • To define the lip borders, also known as the vermillion border.

  • To smooth "marionette lines" around the mouth.

  • To restore volume in the cheeks or under-eye hollows, referred to as tear troughs.

  • When seeking immediate results for volume loss with minimal downtime.

  • Hyaluronic Acid (HA): The gold standard material (e.g., Juvederm, Restylane) that holds moisture and is reversible using hyaluronidase.

  • Biostimulators: Products like Radiesse or Sculptra that encourage the body to produce its own collagen over time.

  • The "Lip Flip": Using a small amount of Botox to relax the upper lip muscle, making more of the lip visible without adding volume.

  • Russian Lips Technique: A method focusing on vertical height and a pronounced "Cupid's bow" instead of outward projection.

  • Cannula Injection: The use of a blunt-tipped cannula to reduce bruising and the risk of vascular complications compared to a needle.

  • Pain Management: Topical numbing cream is applied beforehand to ensure minimal discomfort.

  • Integrated Anesthesia: Most modern fillers are pre-mixed with Lidocaine, a numbing agent, to manage pain during injection.

  • Injection Process: The actual injections are precise and typically take between 15 to 30 minutes to complete.

  • Technique Selection: The injector uses either a needle or a blunt-tipped cannula depending on the target area and desired outcome.

  • Immediate Assessment: Results for HA fillers are visible immediately, allowing for real-time adjustments.

  • Avoid alcohol and blood thinners like Vitamin E or Fish Oil for 3 days prior to minimize bruising.

  • Ensure no dental cleanings or procedures are scheduled for 2 weeks before the appointment.

  • Discuss medical history and any previous filler experiences with the professional.

  • Confirm the practitioner is a licensed medical professional (Dermatologist or Plastic Surgeon).

  • Check that the clinic stocks Hyaluronidase in case of emergencies.

  • Immediate Assessment: HA fillers show instant volume changes during the session.

  • Day 1–2 Milestone: Swelling and bruising are most prominent; intermittent ice pack application is critical.

  • Day 3–5 Milestone: Swelling typically subsides and any small internal lumps begin to soften.

  • Week 2 Milestone: The filler fully integrates into the tissue, and the final result is judged for any "touch-ups".

  • Longevity Check: Lip fillers typically last 6 to 12 months, while cheek or jawline fillers can last 12 to 24 months.

  • Avoid massaging the treated area or sleeping on your face for the first 48 hours to prevent migration.

  • Refrain from intense heat, such as saunas or steam rooms, for 24 to 48 hours.

  • Avoid intense exercise for at least 24 to 48 hours to prevent increased swelling.

  • Do not schedule dental work for 2 weeks after injections to reduce infection risk.

  • Monitor for any signs of vascular occlusion, which requires immediate medical intervention.

  • Provides immediate restoration of facial volume and smoothing of wrinkles.

  • Offers a non-surgical alternative for enhancing features like lips, cheeks, and jawlines.

  • Allows for natural-looking results through specialized techniques like the "Russian Lip".

  • Features a quick procedure time with minimal recovery compared to surgical options.

  • Hyaluronic Acid options are reversible, providing an added layer of safety and flexibility.

Vaginoplasty (Vaginal Tightening)

Vaginoplasty, commonly referred to as vaginal tightening, is a surgical procedure in 2026 designed to tighten the vaginal canal and the surrounding pelvic floor muscles. It is most frequently sought by individuals who have experienced vaginal relaxation or laxity due to childbirth, aging, or significant weight loss.

This procedure is ideal for those looking to restore the structural integrity of the pelvic region. Key indications include:

  • Vaginal Laxity: A feeling of "looseness" or relaxation in the vaginal vault.

  • Muscle Separation: Weakened pelvic floor muscles that no longer provide adequate support.

  • Childbirth-Related Changes: Stretching or tearing of the vaginal tissues following one or more vaginal deliveries.

  • Pelvic Heaviness: A sensation of pressure or heaviness in the pelvic area due to tissue laxity.

  • Perineal Scarring: Visible or uncomfortable scarring from previous episiotomies or tears that require repair.

  • Traditional Surgical Vaginoplasty: The gold standard for significant laxity; involves the permanent structural repair and tightening of the pelvic muscles.

  • Perineoplasty: Often performed in conjunction with vaginoplasty to repair the perineum (the area between the vagina and anus) and restore its aesthetic and functional integrity.

  • Energy-Based Treatments: Utilizing laser or radiofrequency technology in 2026 for very mild cases of laxity or to improve tissue hydration.

  • Pelvic Floor Reconstruction: A more extensive approach for cases involving pelvic organ prolapse alongside vaginal relaxation.

  • Labiaplasty Integration: Frequently combined with other feminine rejuvenation procedures to address both internal and external concerns simultaneously.

  • Surgical Access: The surgeon works through the vaginal opening, meaning there are typically no external scars.

  • Tissue Removal: Excess vaginal lining (mucosa) is carefully measured and removed from the back of the vaginal canal.

  • Muscle Tightening: Strong, dissolvable sutures are used to pull the separated or weakened pelvic muscles closer together, narrowing the canal.

  • Perineal Repair: If needed, the perineal body is reconstructed to provide better support and a more youthful appearance to the vaginal opening.

  • Closure: The internal incisions are closed with fine, absorbable sutures that do not require manual removal.

  • Medical Clearances: A standard blood panel and physical exam are required to ensure the patient is fit for anesthesia.

  • Fasting: Patients must fast for 8–12 hours before the 1 to 2-hour procedure.

  • Gynecological Review: A recent clear Pap smear and an exam to rule out active infections are typically mandatory.

  • Nicotine Cessation: Stopping smoking several weeks before and after surgery is vital for the healing of delicate mucosal tissues.

  • Pelvic Floor Assessment: To determine the degree of muscle separation and ensure a surgical tightening is the appropriate solution.

  • Basic Blood Panel: To evaluate hemoglobin levels and clotting function.

  • ECG: Performed for patients over a certain age or with specific health histories to monitor heart health during anesthesia.

  • Urinalysis: To ensure there are no underlying urinary tract infections (UTIs) prior to the procedure.

  • Initial Days: Expect localized swelling, soreness, and minor spotting. Prolonged sitting should be avoided for the first few days.

  • Hygiene Protocol: Strict hygiene, including gentle rinsing or sitz baths, is required for the first 10 days to prevent infection.

  • Activity Timeline: Most patients return to light desk work within 2 weeks. Heavy lifting, squatting, and strenuous exercise are prohibited for 6 weeks.

  • Healing Window: Sexual intercourse and the use of tampons are strictly prohibited until the 6-to-8-week mark, following a clearance exam by the surgeon.

  • Restored Muscle Tone: Improves the strength and control of the pelvic floor muscles.

  • Enhanced Structural Integrity: Corrects the "gaping" or loose sensation associated with vaginal relaxation.

  • Long-Lasting Results: Provides a permanent structural repair that remains effective for many years, provided no subsequent vaginal births occur.

  • Improved Quality of Life: Resolves physical discomfort and the feeling of pelvic heaviness, contributing to better overall wellbeing.

Pectoral Implant Surgery

Pectoral implant surgery is a surgical procedure in 2026 designed to enhance the size and definition of the chest in men. It is primarily used by individuals who cannot achieve desired chest muscle development through exercise alone, or to correct structural asymmetries and congenital defects such as Poland Syndrome.

This procedure is ideal for men seeking a more contoured or athletic chest profile. Key indications include:

  • Inadequate Muscle Projection: Difficulty building chest mass despite consistent strength training.

  • Chest Asymmetry: Significant differences in the size or shape of the pectoral muscles.

  • Poland Syndrome: A congenital condition characterized by the underdevelopment or absence of the chest muscle on one side.

  • Post-Traumatic Reconstruction: Correcting chest wall defects resulting from previous injuries or surgeries.

  • Desire for Permanent Definition: Seeking a "chiseled" appearance that remains stable regardless of changes in exercise frequency.

  • Submuscular Placement: The 2026 standard, where the implant is placed beneath the pectoralis major muscle to ensure it is well-covered and moves naturally.

  • Solid Silicone Implants: Unlike breast implants, these are made of firm, cohesive silicone that mimics the feel of muscle and cannot leak or rupture.

  • Endoscopic-Assisted Surgery: Utilizing small cameras to create the implant pocket with high precision and minimal muscle trauma.

  • Transaxillary Approach: Placing the incision in the armpit to ensure there are no visible scars on the chest.

  • Hybrid Sculpting: Combining implants with liposuction of the abdomen or flanks to enhance the "V-taper" of the torso.

  • Surgical Access: A small incision is typically made in the natural fold of the armpit (axilla).

  • Pocket Creation: The surgeon carefully creates a space underneath the pectoralis major muscle, often using endoscopic tools for better visualization.

  • Implant Insertion: The solid silicone implant is inserted and positioned to provide optimal projection and lateral definition.

  • Symmetry Check: The surgeon verifies the balance between both sides of the chest to ensure a natural, athletic look.

  • Closure: Incisions are closed with dissolvable sutures, and a medical-grade compression vest is applied to stabilize the implants.

  • Fasting: Patients must fast for 8–12 hours prior to the procedure.

  • Medical Clearances: Standard blood tests and an ECG are required to assess fitness for general anesthesia.

  • Activity Planning: Arrange for 1–2 weeks off from work and ensure help is available for tasks involving arm movement.

  • Medication Review: Avoid blood-thinning medications and certain herbal supplements for 2 weeks prior to reduce bruising.

  • Basic Blood Panel: To evaluate hemoglobin levels, clotting function, and overall health.

  • ECG: Performed to monitor heart health during the 1.5 to 2.5-hour procedure.

  • Physical Assessment: To measure existing muscle mass and skin laxity, ensuring the correct implant size is selected.

  • Imaging (Optional): In complex cases or for Poland Syndrome, a CT or MRI may be used to map the chest wall.

  • Initial Days: Significant tightness and soreness are expected. Arm movement should be kept below shoulder height for the first 2–3 weeks.

  • Compression Therapy: A surgical vest must be worn 24/7 for approximately 4–6 weeks to prevent implant shifting or "flipping."

  • Activity Timeline: Light desk work can usually be resumed after 1 week. Most patients return to full-intensity gym training and chest exercises by the 3-month mark.

  • Long-Term Results: The implants are permanent and do not interfere with the ability to build natural muscle over the top once the area is fully healed.

  • Enhanced Athletic Profile: Provides immediate bulk and projection to the chest that may be difficult to achieve through weightlifting alone.

  • Correction of Defects: Effectively treats the visible signs of Poland Syndrome and other chest wall depressions.

  • Hidden Scarring: The transaxillary incision ensures that the surgical marks are concealed within the armpit.

  • Permanent Definition: Offers a lifelong structural change that does not require the maintenance of injectable fillers.

Chin Augmentation Surgery

In 2026, facial implants are a primary method for structural facial rejuvenation. Chin Augmentation (Genioplasty) focuses on strengthening a "weak" profile and defining the jawline, while Cheek Augmentation restores volume to the mid-face to create higher, more defined cheekbones and a more youthful contour.

Implants are ideal for individuals seeking permanent structural changes rather than temporary volume. Key indications include:

  • Receding Chin: A "weak" chin that makes the nose appear larger or the neck look less defined.

  • Mid-face Flatness: Lack of definition in the cheekbones due to genetics or age-related volume loss.

  • Facial Asymmetry: Significant differences in bone structure between the two sides of the face.

  • Desire for a Sharper Jawline: Seeking a more masculine or feminine "chiseled" look that fillers cannot achieve.

  • Permanent Solution: When a patient is tired of the maintenance and recurring costs associated with injectable fillers.

  • Silicone Implants: Smooth, flexible implants that are easy to place and remove if necessary.

  • Medpor (Porous Polyethylene): A material that allows your own tissue to grow into the implant, providing exceptional long-term stability.

  • Custom 3D-Printed Implants: Utilizing CT scans to create patient-specific implants tailored to your unique bone anatomy.

  • Sliding Genioplasty: A surgical alternative where the chin bone itself is cut and moved forward rather than using a synthetic implant.

  • Hybrid Contouring: Combining an implant with fat grafting to soften the transition between the implant and natural tissue.

  • Surgical Access: Incisions are made in discrete locations—either inside the mouth (lip area) or in the natural crease under the chin—to ensure no visible scarring.

  • Pocket Creation: The surgeon creates a precise space directly over the facial bone to house the implant.

  • Placement & Fixation: The implant is carefully inserted and, in some cases, secured with tiny titanium screws to prevent shifting.

  • Refinement: The surgeon assesses facial symmetry from multiple angles to ensure the new structure complements the nose and jaw.

  • Closure: Incisions are closed with dissolvable sutures, and a supportive bandage or "strap" may be applied to minimize initial swelling.

  • Dental Check-up: Because many incisions are made inside the mouth, your oral health must be excellent to prevent infection.

  • Fasting: Patients must fast for 8–12 hours before the procedure if general anesthesia or deep sedation is used.

  • Imaging: High-resolution CT scans or 3D photos are often taken to map the bone structure and select the correct implant size.

  • Medication Review: Avoiding blood thinners and specific supplements for 2 weeks prior to reduce the risk of hematoma.

  • 3D Facial Mapping: To simulate the aesthetic outcome and ensure the implant size provides a balanced look.

  • Basic Blood Panel: To evaluate overall health and clotting function.

  • ECG: Performed for patients over 40 or those with health conditions to ensure safety under anesthesia.

  • CT Scan: Often used for custom-made implants to provide an exact "blueprint" of the facial skeleton.

  • Initial Days: Expect significant swelling and a "tight" or "heavy" sensation. A soft-food diet is mandatory if internal mouth incisions were used.

  • Oral Care: Frequent use of antiseptic mouthwash is required for 7–10 days to keep internal incisions clean.

  • Activity Restrictions: Contact sports must be avoided for 6–8 weeks to prevent the implant from shifting before it is fully anchored.

  • Settling Period: While the new structure is visible immediately, it takes 3–6 months for the implant to fully "settle" and for residual swelling to vanish.

  • Permanent Enhancement: Provides a lifelong solution for facial structure without the need for touch-ups.

  • Improved Facial Harmony: Balances the proportions of the nose, chin, and forehead for a more attractive profile.

  • No Visible Scars: Using internal mouth incisions ensures that the surgical path is completely hidden.

  • Versatile Results: Implants can be customized in size and shape to achieve everything from subtle rejuvenation to dramatic sculpting.

Body Contouring (Post Bariatric)

Body Contouring after bariatric surgery is a sequence of reconstructive procedures in 2026 designed to remove massive amounts of redundant skin and residual fat. It is the definitive final step for patients who have lost significant weight (50–100+ lbs), as excess skin can cause persistent hygiene issues, chronic infections, and physical discomfort that exercise alone cannot resolve.

This reconstructive journey is recommended for those who have completed their weight-loss phase and are seeking to improve their quality of life. Key indications include:

  • Redundant Skin Folds: Excessive skin on the abdomen, arms, or thighs that interferes with movement or clothing.

  • Chronic Skin Irritation: Recurring rashes or infections (intertrigo) within the skin folds.

  • Functional Limitations: Heavy skin that causes back pain, postural issues, or prevents a return to active fitness.

  • Stabilized Weight: Successful maintenance of a stable weight for at least 6 to 12 months.

  • Psychological Closure: A desire to have one's physical appearance reflect their health and weight-loss achievements.

  • Phase 1 (The Core): Typically involves a Lower Body Lift or a Fleur-de-lis Abdominoplasty to stabilize the midsection.

  • Phase 2 (The Upper Body): Focuses on a Breast Lift (Mastopexy) and an Arm Lift (Brachioplasty).

  • Phase 3 (The Lower Extremities & Face): Includes a Thigh Lift or a Face and Neck Lift to address remaining laxity.

  • Auto-Augmentation: A 2026 standard where redundant tissue is used to rebuild volume in the breasts or buttocks, avoiding the need for synthetic implants.

  • Fleur-de-lis Technique: A specialized approach using both vertical and horizontal incisions to address massive skin redundancy in both directions.

  • Staged Planning: Due to the extensive nature of these surgeries, procedures are spaced 4–6 months apart to allow the body to recover and ensure patient safety.

  • Incision & Removal: The surgeon makes precise incisions to remove wide sections of skin and fat, carefully repositioning the remaining tissue for a natural look.

  • Muscle & Tissue Repair: Weakened muscles (especially in the abdomen) are tightened to provide structural support for the new body shape.

  • Refined Contouring: Targeted liposuction is used to smooth the transitions between the areas where skin was removed.

  • Closure: Complex, multi-layered suturing is used to manage tension on the long incisions, and surgical drains are placed to prevent fluid buildup.

  • Nutritional Optimization: Surgeons require comprehensive blood panels to ensure protein, iron, and B12 levels are optimized, as post-bariatric patients often have deficiencies.

  • Weight Maintenance: Patients must demonstrate a stable "plateau" weight for at least 6 months prior to the first stage.

  • Mental Health Assessment: In 2026, professional support is often encouraged to help patients adjust to their changing body image.

  • Smoking/Vaping Cessation: Strict abstinence is mandatory for several weeks before and after to ensure tissue survival and wound healing.

  • Comprehensive Metabolic Panel: To check electrolyte balance, kidney function, and liver health.

  • Protein & Micronutrient Testing: To confirm the patient has the nutritional reserves (especially albumin) needed for massive tissue healing.

  • ECG & Cardiac Clearance: Essential due to the multiple, lengthy surgical sessions required.

  • Standard Blood Panel: To evaluate hemoglobin and clotting factors to minimize the risk of post-operative anemia.

  • High-Intensity Healing: The first week of each stage requires around-the-clock assistance and careful drain management.

  • Compression Support: Heavy-duty medical compression garments are worn for 6–8 weeks to support the tissues and minimize swelling.

  • Total Timeline: A full body transformation typically takes 12 to 18 months to complete all stages and see the final settled results.

  • Scar Management: While scars are extensive and permanent, 2026 protocols include advanced topical treatments and laser therapies to help them fade over time.

  • Elimination of Skin Issues: Directly resolves chronic rashes, infections, and hygiene struggles associated with skin folds.

  • Restored Mobility: Dramatically improves the ability to exercise, run, and move without the hindrance of heavy skin.

  • Permanent Tissue Correction: Once the redundant skin is surgically removed, it does not return if weight remains stable.

  • Complete Transformation: Provides the physical and emotional "finish line" to a significant weight-loss journey.

Lower Body Lift Surgery

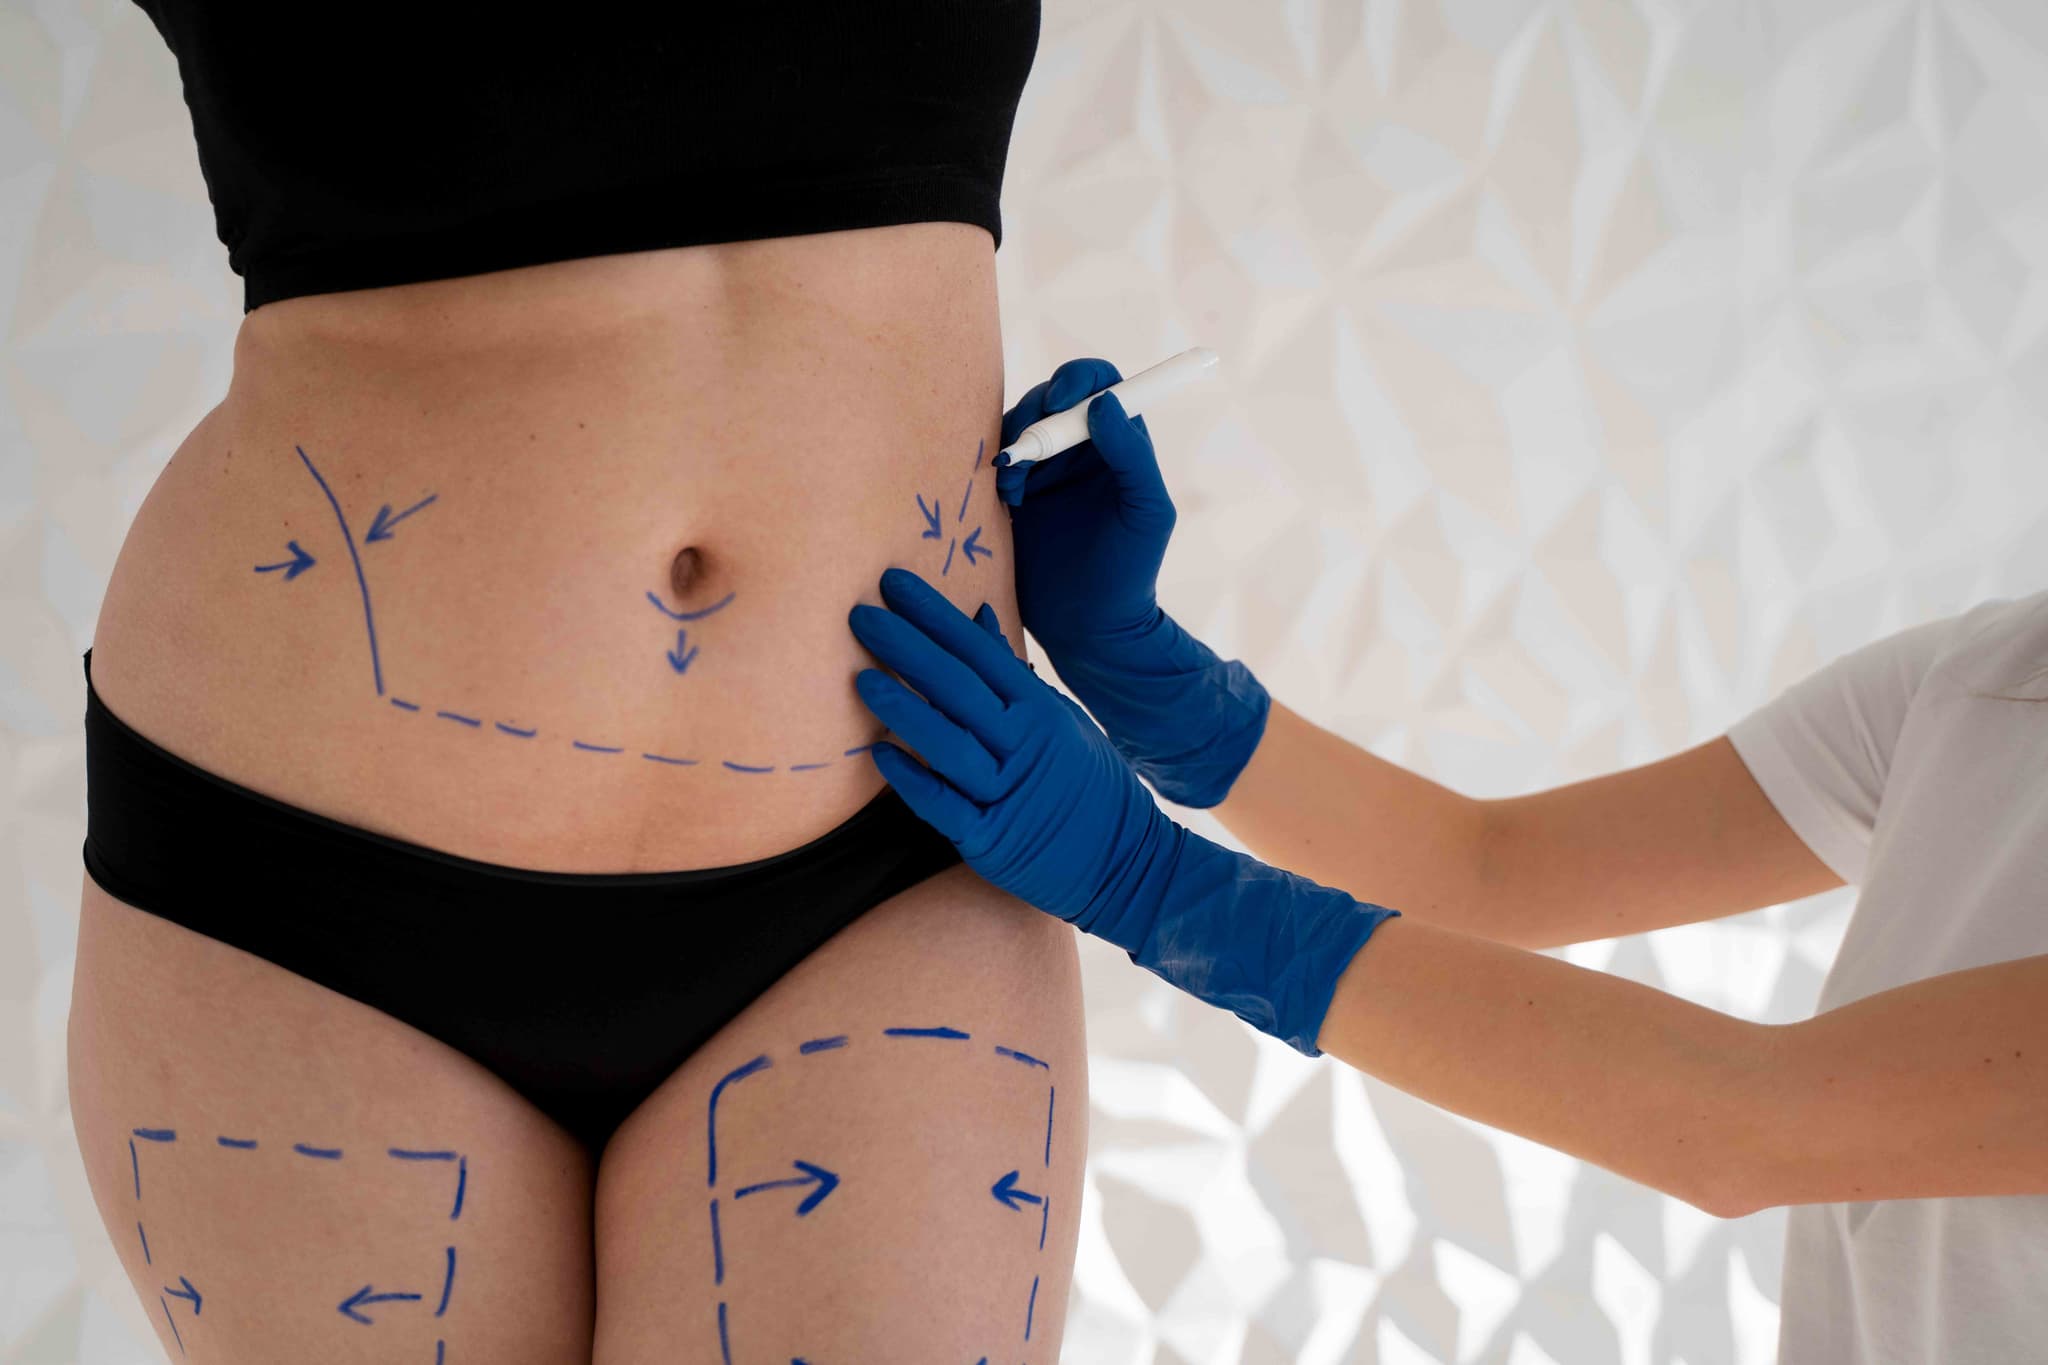
A Lower Body Lift, or belt lipectomy, is a comprehensive 360-degree surgical procedure in 2026 designed to remove a "belt" of excess skin and fat from the entire midsection. It is considered the gold standard for body contouring following massive weight loss (typically 50–100+ lbs) via bariatric surgery or lifestyle changes, where the skin lacks the elasticity to retract on its own.

This procedure is ideal for patients who have achieved significant weight loss and are left with redundant, sagging skin around their entire circumference. Key indications include:

  • Circumferential Skin Laxity: Excess skin that hangs around the abdomen, hips, and back.

  • Abdominal "Pannus": An apron of skin that hangs over the pubic area, often causing hygiene issues or discomfort.

  • Significant Buttock and Thigh Ptosis: Sagging of the gluteal tissue and outer thighs that interferes with movement.

  • Post-Bariatric Stabilization: When a patient has maintained a stable weight for 6–12 months after major weight loss.

  • Desire for Total Midsection Rejuvenation: When a standard tummy tuck is insufficient to address sagging at the hips and lower back.

  • Abdomen: Removes the excess skin apron and tightens the underlying abdominal muscles.

  • Buttocks: Lifts sagging gluteal tissue; can include "auto-augmentation" using the patient's own tissue to restore volume.

  • Hips and Flanks: Eliminates "love handles" and redundant skin along the sides of the torso.

  • Outer Thighs: Provides a significant lift to the lateral thighs, smoothing the transition from the hip to the leg.

  • Surgical Access: A continuous incision is made around the circumference of the torso, positioned where it can be hidden by a belt or underwear line.

  • Tissue Removal: The surgeon removes a large "belt" of skin and underlying fat from the entire midsection.

  • Muscle Repair: The abdominal muscles (rectus diastasis) are tightened to restore core strength and a flat stomach profile.

  • Lifting and Securing: The skin of the lower body is pulled upward, and the skin of the upper body is pulled downward, then secured to deep supportive tissues.

  • Closure: The 360-degree incision is closed in multiple layers to manage tension, and several surgical drains are placed.

  • Medical Clearances: Extensive blood work, an ECG, and a nutritional assessment are mandatory for this 5 to 8-hour surgery.

  • Weight Stability: Patients must provide evidence of a stable weight for at least 6 to 12 months.

  • Nutrition Optimization: In 2026, a high-protein diet is prescribed weeks before surgery to ensure the body has the resources for massive tissue healing.

  • Smoking Cessation: Strict abstinence from smoking and vapes is required for at least 6 weeks before and after to prevent incision failure.

  • Comprehensive Blood Panel: To check hemoglobin, protein levels, and clotting factors.

  • ECG and Cardiac Clearance: Essential due to the length of time the patient will be under general anesthesia.

  • Nutritional Screening: To ensure the patient does not have vitamin deficiencies common after bariatric surgery.

  • Physical Mapping: Detailed measurements of skin laxity to plan the precise location of the 360-degree incision.

  • Hospital Stay: Typically requires an overnight stay (1–2 nights) for monitoring and pain management.

  • Initial Milestones: Patients walk with a slight "stoop" for the first 1–2 weeks to protect the incisions. Drains are usually removed within 14 days.

  • Compression Therapy: Specialized garments (Fajas) are worn 24/7 for 6–8 weeks to reduce swelling and support the new contours.

  • Long-Term Healing: Swelling can take 6–12 months to fully resolve. Scars are permanent but fade significantly over the first year.

  • Total Body Transformation: Addresses the entire midsection in a single surgery, providing a more proportional and toned appearance.

  • Improved Mobility: Removes heavy, hanging skin that can cause physical discomfort or limit exercise.

  • Enhanced Hygiene: Eliminates skin folds that are prone to rashes, infections, and irritation.

  • Psychological Restoration: Provides a "final step" in the weight loss journey, helping patients feel their body truly reflects their hard work.

Thigh Lift Surgery
Thigh Lift Surgery

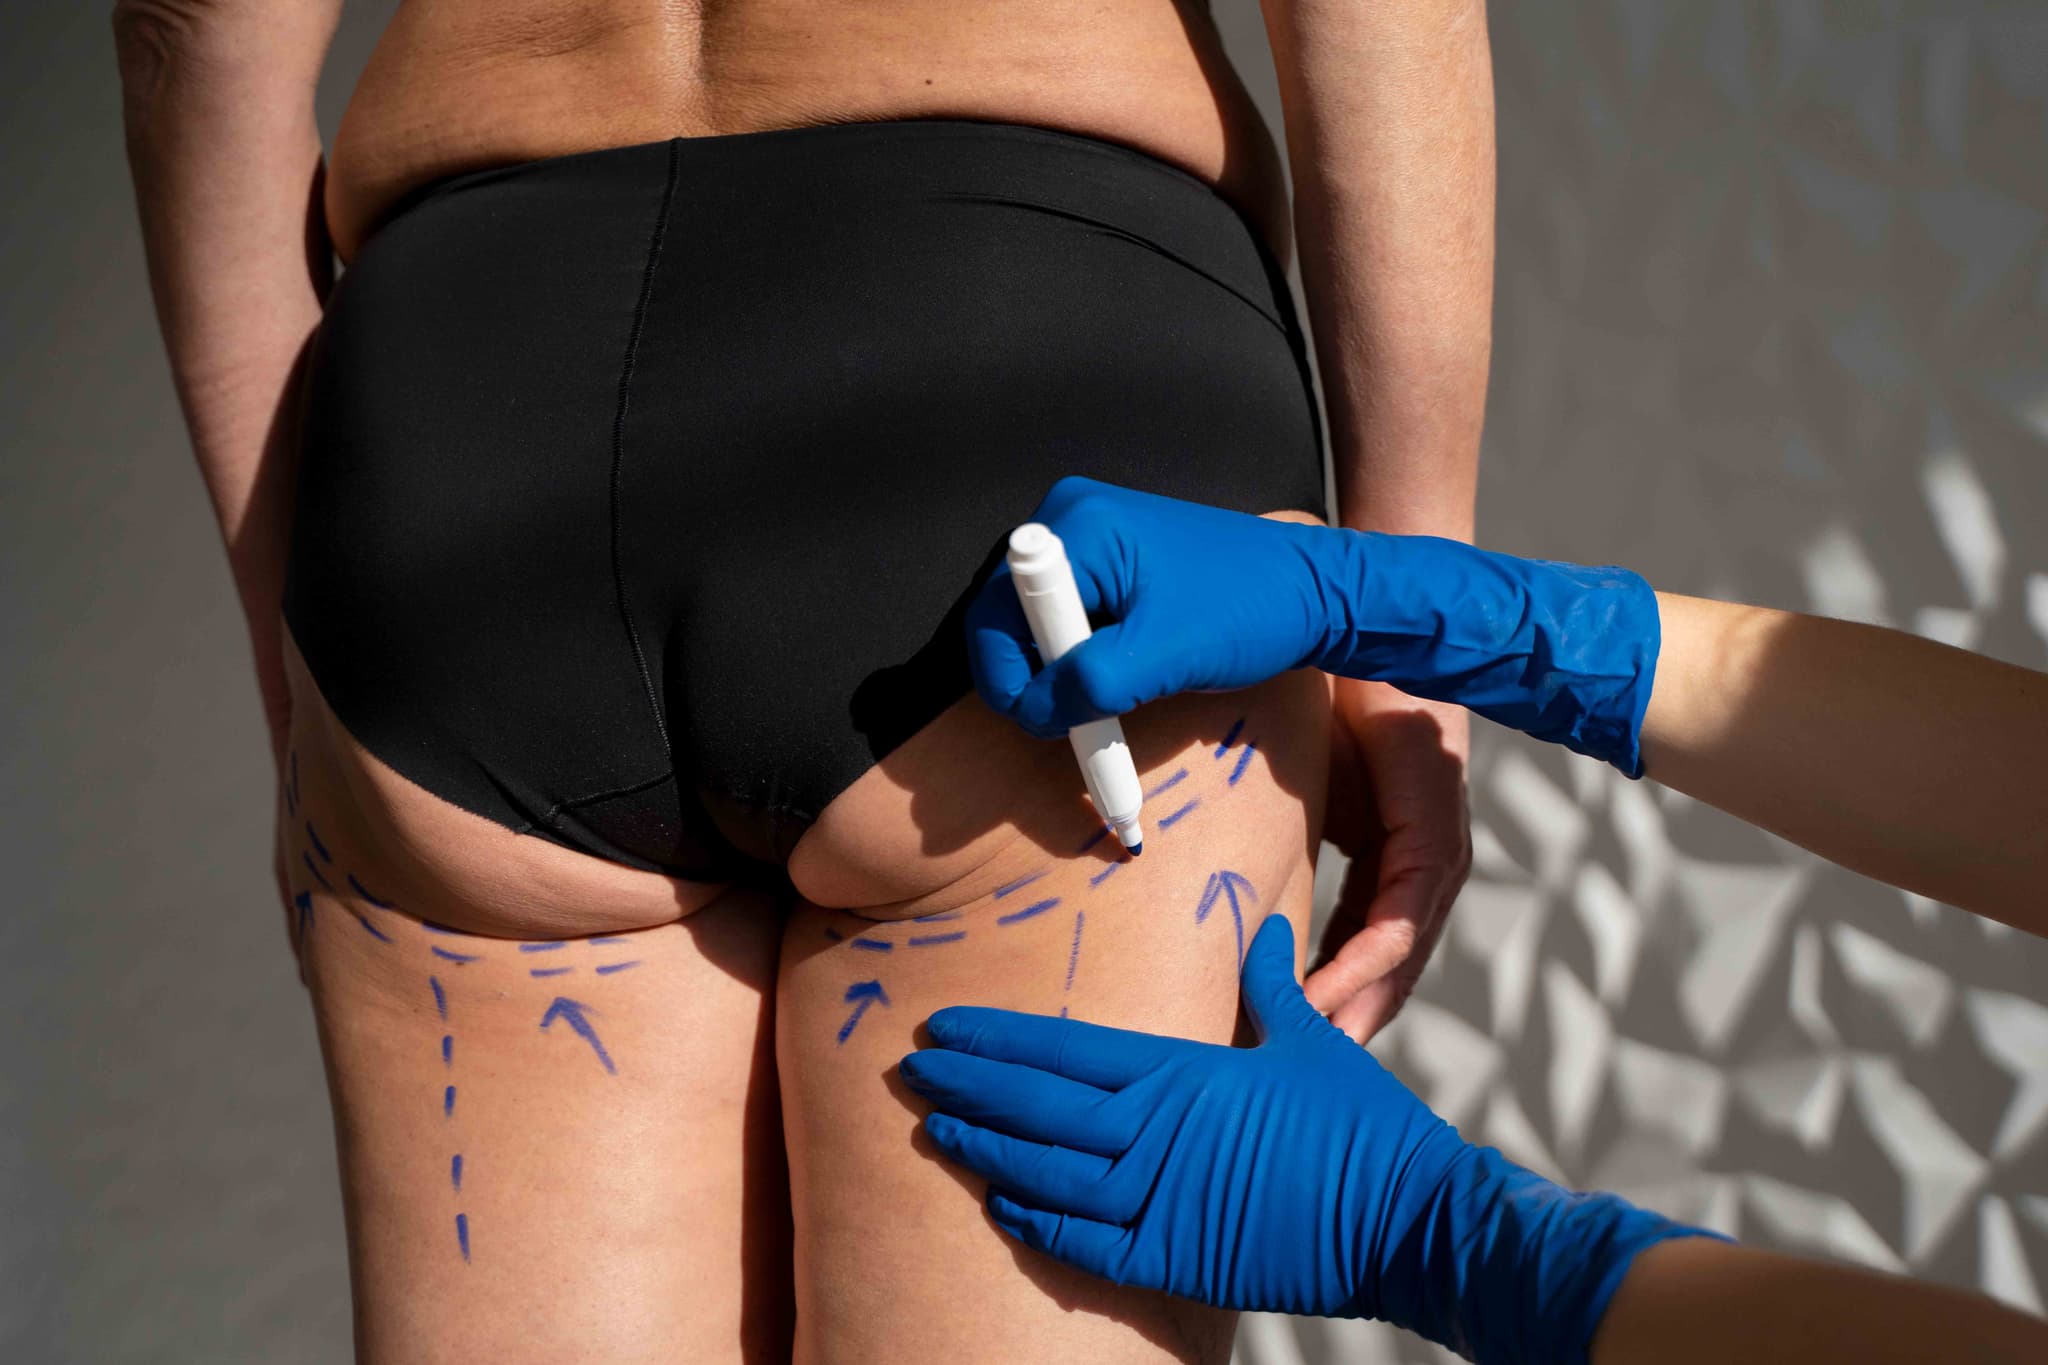
A Thigh Lift, or thighplasty, is a surgical procedure in 2026 designed to remove excess skin and fat from the thigh area. It is a highly effective solution for individuals dealing with skin laxity following significant weight loss or natural aging, where the skin has lost the elasticity required to respond to exercise alone.

This procedure is ideal for patients seeking a smoother, firmer lower body contour. Key indications include:

  • Significant Skin Sagging: "Crepey" or loose skin that hangs from the inner or outer thighs.

  • Post-Weight Loss: Redundant tissue remaining after major weight reduction that causes physical discomfort or chafing.

  • Lower Body Disproportion: Thighs that appear out of proportion with the rest of the toned lower body.

  • Persistent Fat & Skin: Localized fat deposits combined with loose skin that create "ripples" or folds.

  • Limited Mobility: Excess skin that interferes with walking, exercise, or finding comfortable clothing.

  • Inner (Medial) Thigh Lift: The most common technique, focusing on the upper-inner thigh with incisions hidden in the groin crease.

  • Vertical Thigh Lift: Addresses significant skin laxity extending toward the knee; requires a vertical incision along the inner thigh.

  • Outer (Lateral) Thigh Lift: Targets the outside of the thighs and "saddlebag" areas, often extending the incision toward the hip.

  • Spiral Thigh Lift: A comprehensive 360-degree approach for patients with massive weight loss, addressing the front, back, inner, and outer thigh.

  • Lipo-Thighplasty: A 2026 standard combining thorough liposuction with skin excision to ensure a more sculpted and defined result.

  • Surgical Access: Incisions are strategically placed in the groin fold or along the inner thigh, depending on the volume of tissue to be removed.

  • Fat Contouring: Liposuction is utilized to thin the fatty layer and shape the underlying contours of the leg.

  • Tissue Tightening: A wedge of skin and fat is removed, and the remaining tissue is pulled upward and secured to deep supportive structures.

  • Skin Smoothing: The skin is redraped over the new contour to eliminate sagging and dimples.

  • Closure: The surgeon uses multi-layered suturing to minimize tension on the skin, and compression bandages are applied immediately.

  • Fasting: Patients must fast for 8–12 hours before the 2 to 4-hour surgery.

  • Medical Clearances: Standard blood tests and an ECG are required to ensure the patient is fit for general anesthesia.

  • Weight Stability: Candidates should be at a stable weight for at least 6 months to ensure long-lasting results.

  • Hygiene Protocol: Patients may be prescribed an antibacterial wash to use for several days prior, especially around the groin area.

  • Basic Blood Panel: To evaluate hemoglobin levels and ensure optimal clotting function.

  • ECG: Performed to monitor heart health during the procedure.

  • Physical Assessment: To determine the degree of skin laxity and calculate the necessary incision length for effective correction.

  • Nicotine Screening: Because blood flow is critical for healing in the thigh area, many 2026 surgeons require a nicotine-free test.

  • Hospital Stay: Usually performed as an outpatient procedure, though a 1-night stay may be recommended for more extensive "Spiral" lifts.

  • Initial Milestones: Mobility is limited for the first week; patients must walk slightly hunched to avoid tension on groin incisions.

  • Compression Therapy: Medical-grade compression garments must be worn 24/7 for the first 3 to 6 weeks to support the tissue.

  • Activity Timeline: Most return to light desk work by week 3; full physical activity and high-impact leg workouts are typically resumed by week 8.

  • Smoother Silhouette: Effectively eliminates the "rippled" appearance of loose skin for a firmer look.

  • Reduced Chafing: Removing excess inner-thigh skin significantly reduces skin irritation and discomfort during movement.

  • Better Clothing Fit: Allows for a more comfortable and confident fit in swimwear, shorts, and fitted trousers.

  • Permanent Tissue Removal: Once the excess skin is surgically removed, the results are permanent as long as the patient maintains a stable weight.

Arm Lift (Brachioplasty)

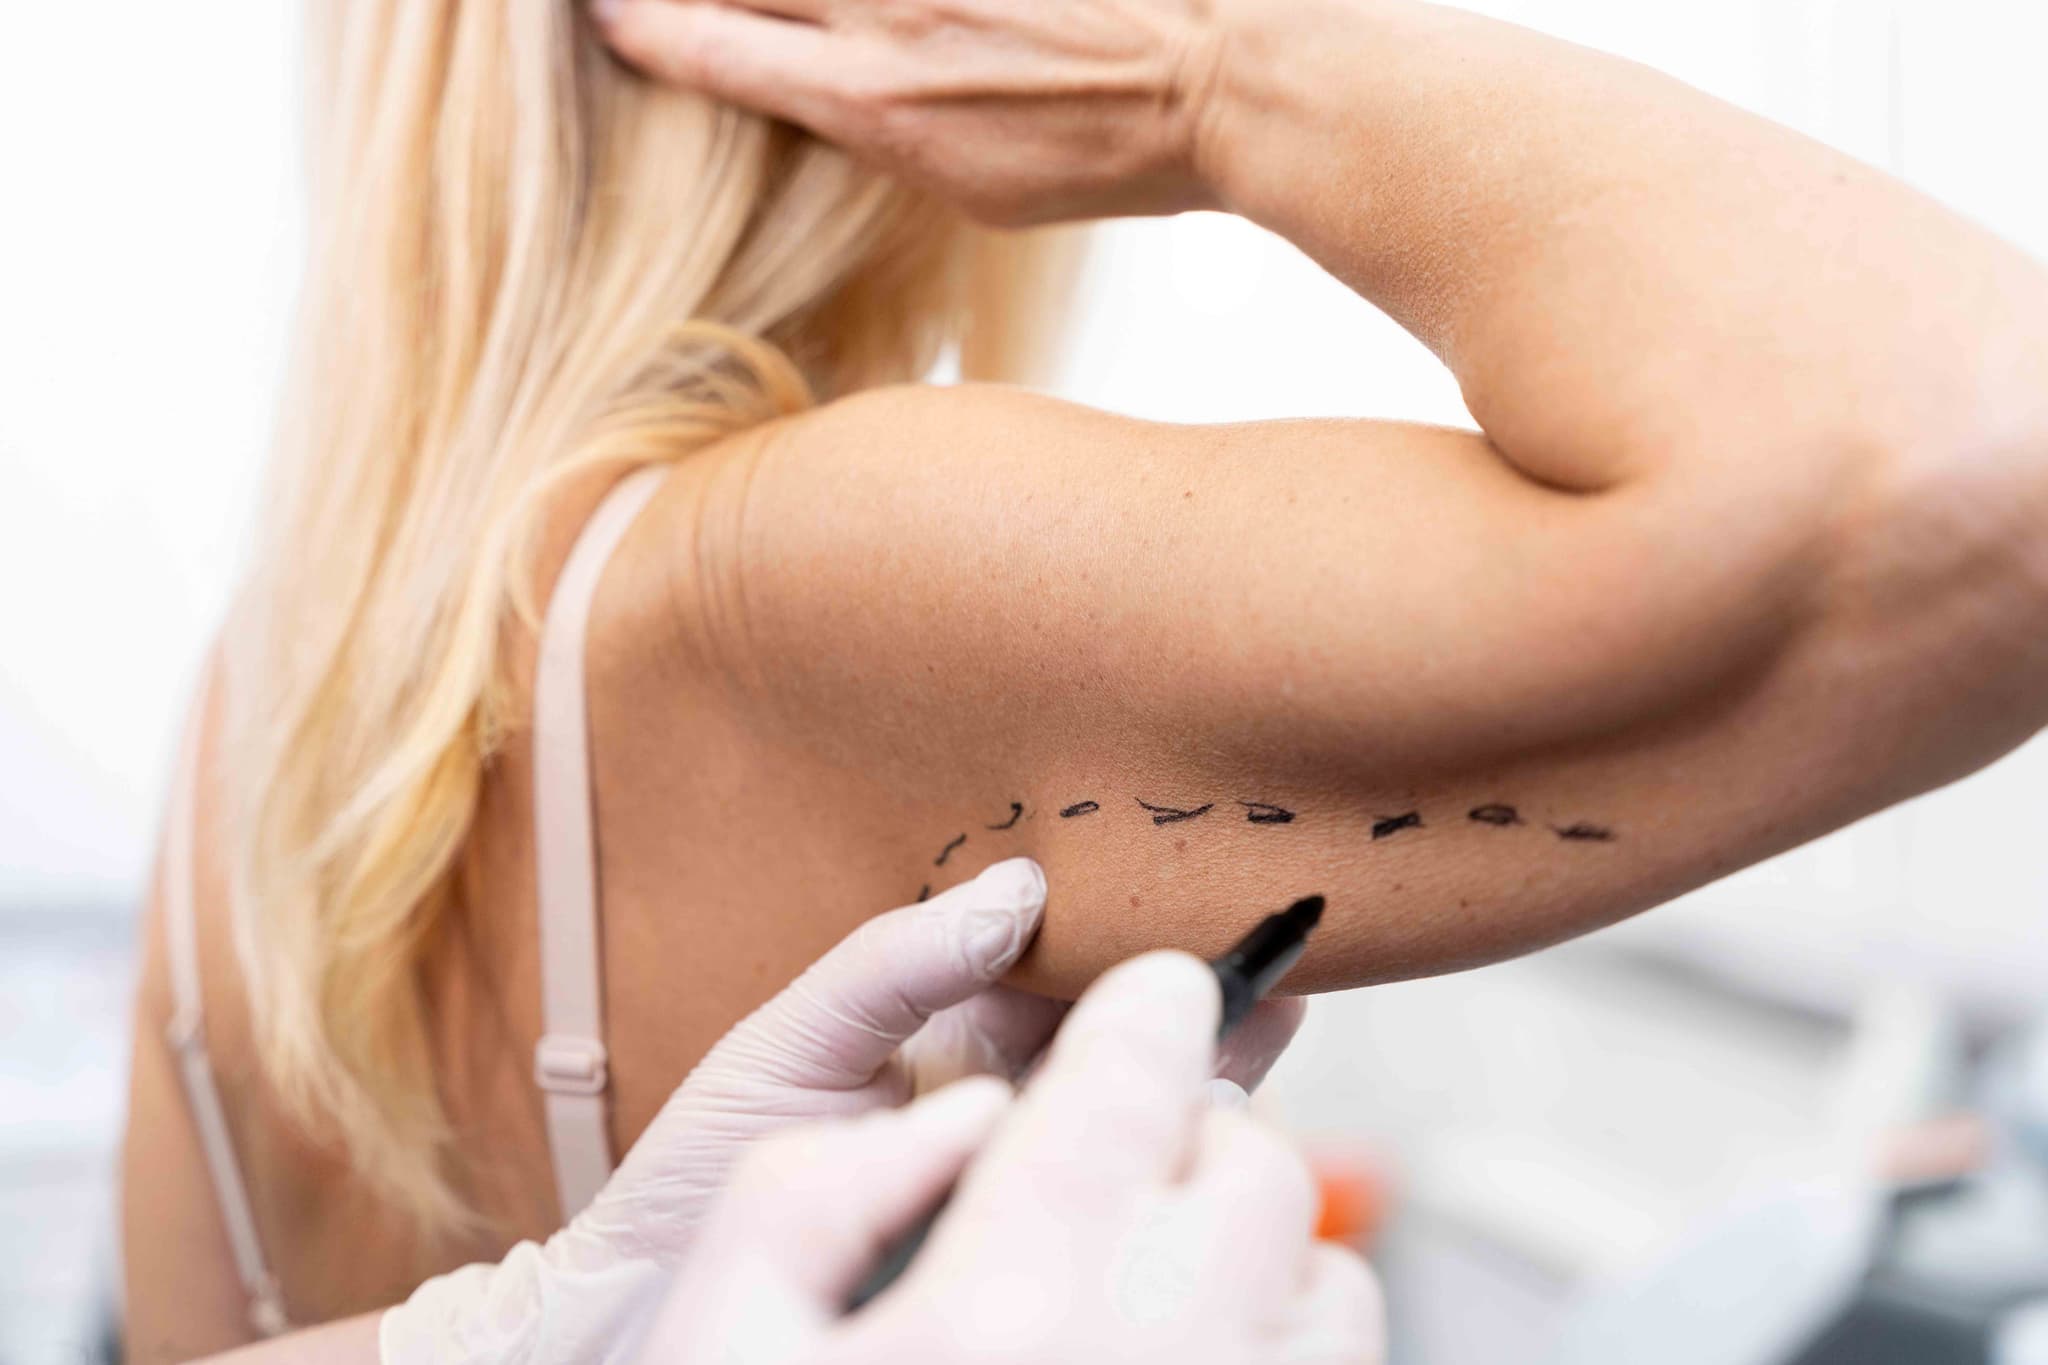
An Arm Lift, or brachioplasty, is a surgical procedure used in 2026 to remove excess, sagging skin and fat from the upper arms. Often referred to as correcting "bat wings," this procedure is most common among individuals who have experienced significant weight loss or natural aging where the skin has lost its ability to retract.

This procedure is ideal for those who have achieved a stable weight but are left with redundant skin that does not respond to exercise. Key indications include:

  • Significant Skin Laxity: Loose, "crepey" skin that hangs from the underside of the upper arm.

  • Post-Weight Loss: Excess tissue remaining after losing a significant amount of weight.

  • Stubborn Arm Fat: Localized fat deposits combined with loose skin that create a heavy arm appearance.

  • Ineffective Toning: When strength training has built muscle, but it remains hidden under sagging tissue.

  • Personal Comfort: Difficulty finding clothing that fits or feeling self-conscious in short-sleeved or sleeveless attire.

  • Traditional Brachioplasty: The most common method, involving an incision from the armpit to the elbow to remove significant amounts of skin.

  • Mini Arm Lift: Utilizes a smaller, crescent-shaped incision hidden in the armpit for patients with minimal sagging.

  • Extended Brachioplasty: The incision continues from the arm onto the side of the chest to address sagging lateral chest tissue.

  • Lipo-Brachioplasty: A 2026 hybrid approach using aggressive liposuction first to protect nerves and lymphatics, followed by skin removal.

  • Non-Surgical Skin Tightening: Radiofrequency or ultrasound treatments for very mild cases (not a substitute for surgery).

  • Surgical Access: The surgeon makes an incision along the underside or back of the arm, strategically placed to be as discrete as possible.

  • Fat Removal: Liposuction is often used first to thin the fat layer and contour the arm.

  • Tissue Tightening: The underlying supportive tissues are reshaped and tightened with internal sutures.

  • Skin Excision: The excess skin is trimmed away, and the remaining skin is smoothed over the new, toned contour.

  • Closure: The incisions are closed with multi-layered sutures, and the arms are wrapped in sterile dressings and compression sleeves.

  • Fasting: Patients must fast for 8–12 hours before the procedure.

  • Medical Clearances: Standard blood tests and an ECG are required to ensure the patient is fit for anesthesia.

  • Weight Stability: Ideal candidates should have maintained a stable weight for at least 6 months.

  • Medication Review: Patients must avoid medications that increase bleeding, such as aspirin or certain herbal supplements, for 2 weeks prior.

  • Basic Blood Panel: To evaluate hemoglobin levels, white blood cell count, and clotting ability.

  • ECG: Performed to monitor heart health during the 2 to 3-hour procedure under general anesthesia.

  • Physical Assessment: To measure the amount of excess skin versus fat and determine the most effective incision pattern.

  • Nicotine Test: In 2026, many surgeons require a nicotine-free test to ensure optimal wound healing and minimize scar widening.

  • Hospital Stay: Usually performed as an outpatient procedure; patients return home the same day.

  • Initial Milestones: Most patients return to light desk work and basic self-care within 1 week.

  • Compression Therapy: Specialized compression sleeves must be worn 24/7 for the first 3 to 4 weeks to manage swelling.

  • Activity Restrictions: No heavy lifting (over 5–10 lbs) or reaching over the head for 6 weeks to protect the incisions.

  • Toned Appearance: Creates a slender, more defined arm profile that reflects the patient’s actual fitness level.

  • Improved Mobility: Removes heavy, excess skin that can cause discomfort or chafing during physical activity.

  • Clothing Confidence: Allows for a wider range of clothing options, including sleeveless tops and well-fitted jackets.

  • Permanent Skin Removal: Once the excess skin is surgically removed, it does not return, provided a stable weight is maintained.

Mommy Makeover
Mommy Makeover

A Mommy Makeover is a customized combination of cosmetic procedures in 2026 designed to restore a woman’s body to its pre-pregnancy shape. Rather than a single surgery, it is a tailored surgical plan that typically addresses the "core" areas most affected by childbearing—the breasts and the abdomen—in a single operative session.

This procedure is ideal for women who have finished having children and wish to address multiple physical changes simultaneously. Key indications include:

  • Abdominal Laxity: Loose skin and weakened muscles (diastasis recti) following pregnancy.

  • Breast Changes: Deflated volume or sagging (ptosis) after breastfeeding or weight fluctuations.

  • Stubborn Fat Deposits: Localized fat in the hips, flanks, or thighs that resists diet and exercise.

  • Post-Pregnancy Body Changes: A desire to restore pre-pregnancy contours and improve body confidence.

  • Desire for Efficiency: Wishing to undergo anesthesia once and navigate a single recovery period for multiple concerns.

  • Abdominoplasty (Tummy Tuck): To tighten the abdominal wall and remove excess skin.

  • Breast Augmentation or Lift: To restore volume and/or reposition the breasts to a more youthful height.

  • Liposuction: Often used to contour the "love handles" and waistline for a more defined silhouette.

  • Hybrid Breast Rejuvenation: Utilizing fat grafting (from liposuction) alongside or instead of implants for a natural finish.

  • Labiaplasty: An optional procedure to address discomfort or aesthetic changes in the vaginal area.

  • Surgical Access: The surgeon performs the planned procedures sequentially, starting with breast surgery and concluding with the abdomen.

  • Targeted Repair: Muscles are tightened, excess skin is removed, and volume is restored according to the patient’s specific goals.

  • Pain Management: In 2026, long-acting "nerve blocks" (like Exparel) are often used to provide significant pain relief for the first 72 hours.

  • Advanced Sculpting: The surgeon uses liposuction to ensure a smooth, harmonious transition between the newly contoured breasts and abdomen.

  • Closure and Drains: Incisions are closed with multi-layered sutures, and surgical drains may be placed to manage fluid during the initial healing phase.

  • Timing: It is recommended to wait at least 6 to 12 months after your last pregnancy or finishing breastfeeding.

  • Childcare Planning: Dedicated help for children is essential, as you cannot lift a toddler for 4 to 6 weeks.

  • Fasting: Patients must fast for 8–12 hours before the 4 to 7-hour surgery.

  • Medical Clearances: Comprehensive blood work, an ECG, and a physical exam are required to ensure safety for a longer surgical session.

  • Basic Blood Panel: To evaluate hemoglobin levels and clotting function for a multi-procedure surgery.

  • ECG: Required to monitor heart health during extended general anesthesia.

  • Mammogram: Standard for any patient undergoing breast surgery to ensure baseline breast health.

  • BMI Assessment: To confirm the patient is at a stable "goal weight," as the makeover is a contouring procedure rather than a weight-loss tool.

  • Hospital Stay: Depending on the complexity, patients may go home the same day or stay for 1 night for observation.

  • Initial Challenges: The first week is the most demanding; mobility is limited, and standing fully upright may take 1 to 2 weeks.

  • Activity Restrictions: No heavy lifting (over 5–10 lbs) for 4 to 6 weeks. Most patients return to light desk work in 2 to 3 weeks.

  • Long-Term Results: Final body contours typically emerge within 6 months as swelling fully resolves and tissues settle.

  • Comprehensive Transformation: Addresses multiple areas of concern in a single surgical event.

  • Single Recovery Period: Streamlines the healing process, requiring only one period of downtime and one round of anesthesia.

  • Restored Core Stability: Repairing abdominal muscle separation improves posture and reduces back pain.

  • Enhanced Self-Confidence: Helps women feel more comfortable and "like themselves" again in their post-pregnancy bodies.

Brazilian Butt Lift (BBL)

A Brazilian Butt Lift (BBL) is a specialized fat transfer procedure that uses a patient's own fat to enhance the size, shape, and contour of the buttocks. This "two-in-one" procedure utilizes liposuction to harvest fat from donor sites—such as the abdomen, hips, or thighs—and re-injects it into the gluteal region to improve overall body proportions.

A BBL is ideal for individuals looking for a natural-feeling enhancement and improved body symmetry. Key indications include:

  • Flat or Sagging Buttocks: Lack of volume or definition in the gluteal area.

  • Asymmetrical Contour: Significant differences in shape or size between the two sides.

  • Body Proportionality: A desire for a "snatched" waist and a more rounded, hourglass silhouette.

  • Post-Weight Loss: Restoring fullness and shape lost after significant weight reduction.

  • Avoidance of Implants: Preference for using natural tissue (autologous fat) rather than synthetic foreign objects.

  • Subcutaneous Injection: Modern safety protocols strictly require fat to be injected into the space above the muscle to prevent serious complications.

  • Ultrasound-Guided BBL: The use of real-time ultrasound imaging to guide the cannula, ensuring precise fat placement and avoiding deep blood vessels.

  • Puregraft/Purification Systems: Advanced filtering technologies used to isolate the healthiest fat cells for a higher "take" or survival rate.

  • "Skinny BBL": A specialized technique for leaner patients that focuses on high-definition harvesting and targeted, smaller-volume transfer.

  • Hybrid BBL: Combining fat transfer with specialized skin-tightening technologies at the donor sites for a more sculpted result.

  • Fat Harvesting: The surgeon performs liposuction on pre-determined donor areas (like the "love handles" or stomach) to collect fat.

  • Purification: The harvested fat is processed to remove impurities, oils, and excess fluids, leaving only viable fat cells.

  • Fat Injection: The purified fat is injected into the buttocks through tiny incisions at various depths within the subcutaneous layer.

  • Sculpting: The surgeon carefully shapes the buttocks and the transition to the waist/thighs to create a harmonious, natural look.

  • Closure: Liposuction and injection sites are closed (often with a single stitch), and a medical-grade compression garment (Faja) is applied.

  • Fasting: Patients are required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Comprehensive blood work, an ECG, and a physical exam are necessary to ensure surgical safety.

  • Nutrition & Health: Patients should be at a stable weight and maintain a healthy, nutrient-rich diet to ensure high fat-cell viability.

  • Nicotine Cessation: Stopping all nicotine products several weeks before and after is mandatory, as smoking significantly reduces fat survival.

  • Basic Blood Panel: To evaluate hemoglobin levels, kidney function, and blood clotting factors.

  • ECG: Performed to monitor heart health during the 2 to 4-hour procedure under general anesthesia.

  • BMI Assessment: To ensure the patient has sufficient donor fat and falls within a safe weight range for elective surgery.

  • Skin Elasticity Check: To assess how well the skin will retract at the liposuction donor sites.

  • The "No-Sit" Phase: For the first 2–3 weeks, patients must avoid sitting or lying directly on the buttocks to ensure fat survival.

  • Support Tools: Specialized BBL pillows are used when sitting is absolutely necessary to shift pressure to the thighs.

  • Compression Therapy: Fajas (compression garments) must be worn for 6–8 weeks to support the donor sites and minimize swelling.

  • Activity Timeline: Light walking is encouraged immediately; desk work can typically be resumed after 2 weeks, and exercise after 6–8 weeks.

  • Natural Results: Uses the patient’s own tissue, providing a more natural look and feel than silicone implants.

  • Dual Transformation: Simultaneously contours problem areas (via liposuction) while enhancing the buttocks.

  • Permanent Enhancement: While some fat is absorbed, the 60–80% that survives is permanent as long as weight remains stable.

  • Improved Silhouette: Creates a more defined waist-to-hip ratio, enhancing both the front and side profiles.

Liposuction Surgery
Liposuction Surgery

Liposuction is a surgical fat-removal procedure used in 2026 to contour and reshape specific areas of the body. It is designed as a treatment for "stubborn" fat deposits that do not respond to traditional fitness or health-focused efforts, rather than as a primary tool for weight reduction.

This procedure is best suited for individuals near their stable goal weight who wish to address localized areas of concern. Key indications include:

  • Stubborn Fat Deposits: Pockets of fat in the abdomen, hips, thighs, or arms that persist despite a healthy lifestyle.

  • Body Contouring: A desire to improve the silhouette or "sculpt" certain areas for better proportion.

  • Submental Fat: Excess fat under the chin or along the jawline (double chin).

  • Lipomas: Benign fatty tumors that may require removal for comfort or appearance.

  • Gynecomastia: Excess fatty tissue in the male chest area.

  • Tumescent Liposuction: The standard technique utilizing a sterile saline solution to firm the fat, making it easier to remove while minimizing bruising.

  • Vaser (Ultrasound-Assisted): Uses ultrasound energy to "liquefy" fat cells, offering a gentler extraction for surrounding tissues.

  • Laser-Assisted (SmartLipo): Utilizes laser energy to melt fat and can provide a minor collagen-stimulating effect for the skin.

  • High-Definition (HD) Lipo: A specialized sculpting technique used to define the edges of muscle groups for an athletic appearance.

  • Power-Assisted Liposuction (PAL): Uses a vibrating cannula to allow the surgeon to remove fat more efficiently with less manual force.

  • Surgical Access: Tiny incisions (usually a few millimeters) are made in discrete locations near the target area.

  • Fluid Injection: The tumescent solution is injected to numb the area and constrict blood vessels.

  • Fat Removal: A thin tube called a cannula is inserted. The surgeon moves it to loosen the fat, which is then vacuumed out.

  • Sculpting: The surgeon carefully monitors the symmetry and contour of the area to ensure a smooth, balanced result.

  • Closure: Incisions are often left open slightly to allow for drainage or closed with a single stitch, and a compression garment is applied.

  • Fasting: Patients must fast for 8–12 hours before the procedure if receiving sedation or general anesthesia.

  • Medical Clearances: Standard blood tests and an ECG are required to ensure the patient is fit for the procedure.

  • Health Stability: Ideal candidates have maintained a stable weight for at least 6 months prior to surgery.

  • Medication Review: Patients should avoid aspirin, anti-inflammatory drugs, and specific herbal supplements that can increase the risk of bleeding.

  • Basic Blood Panel: To assess hemoglobin levels, kidney function, and blood clotting capability.

  • ECG: Required to monitor heart health, especially for larger volume procedures.

  • Skin Elasticity Assessment: To determine if the skin has enough snap-back to retract smoothly after fat removal.

  • Pregnancy Test: To ensure the patient is not currently pregnant before undergoing anesthesia.

  • Hospital Stay: Usually an outpatient procedure; patients return home the same day.

  • Compression Therapy: A specialized garment must be worn 24/7 for the first 2 weeks to prevent fluid buildup (seroma) and ensure smooth results.

  • Activity Timeline: Most patients return to light work within 1 week; strenuous exercise is typically resumed at the 4-week mark.

  • Long-Term Maintenance: While removed fat cells do not grow back, maintaining a balanced, healthy lifestyle is essential to prevent the expansion of remaining fat cells.

  • Permanent Fat Cell Removal: The fat cells extracted during the procedure are gone forever.

  • Precision Contouring: Allows for targeted reshaping of areas that are difficult to change through other means.

  • Immediate Silhouette Improvement: Provides a visible change in body proportions once initial swelling subsides.

  • Enhanced Confidence: Helps many patients feel more comfortable in their clothing and more satisfied with their physical profile.

Gynecomastia Treatment (Male Breast Reduction)

Gynecomastia surgery, or male breast reduction, is a procedure used in 2026 to reduce enlarged breast tissue in men. It addresses the appearance of "man boobs" caused by genetics, hormonal imbalances, certain medications, or weight fluctuations that do not respond to traditional diet or exercise.

This procedure is recommended for men who have completed puberty and are looking to achieve a more contoured chest. Key indications include:

  • Excess Glandular Tissue: Firm, rubbery tissue beneath the nipple that cannot be lost through exercise.

  • Stubborn Chest Fat: Localized fat deposits that create a feminine chest appearance despite a healthy lifestyle.

  • Sagging Skin: Loose skin on the chest following significant weight loss.

  • Asymmetry: One side of the chest appearing significantly larger or differently shaped than the other.

  • Psychological Impact: Feeling self-conscious or avoiding certain clothing and social activities due to chest appearance.

  • Liposuction: Utilizes a small cannula to vacuum out excess fatty tissue; often the primary method for "pseudo-gynecomastia."

  • Surgical Excision: The direct removal of firm glandular tissue or excess skin, typically performed through an incision around the nipple.

  • Vaser or Laser-Assisted Liposuction: 2026 standards often use these technologies to liquefy fat and stimulate skin tightening simultaneously.

  • High-Definition Sculpting: A technique used to etch the borders of the pectoral muscles for a more "athletic" and defined look.

  • Combination Approach: Using both liposuction for smooth contouring and excision for firm tissue removal to achieve the best result.

  • Surgical Access: Small incisions are made either in the armpit for liposuction or along the edge of the areola (periareolar) for excision.

  • Fat and Tissue Removal: The surgeon removes excess fat via liposuction and meticulously trims away the firm glandular tissue.

  • Chest Contouring: The remaining tissue is sculpted to ensure a smooth transition between the chest wall and the surrounding areas.

  • Nipple Repositioning: If necessary, the nipple and areola are shifted to a more natural position on the flattened chest mound.

  • Closure: The small incisions are closed with fine sutures, and a medical-grade compression vest is applied immediately to manage swelling.

  • Fasting: Patients are typically required to fast for 8–12 hours before the surgery.

  • Hormonal Evaluation: In 2026, blood tests are standard to rule out treatable hormonal imbalances or underlying medical causes.

  • Medical Clearances: Basic blood work and an ECG are performed to ensure the patient is fit for anesthesia.

  • Substance Review: Patients must avoid anabolic steroids, certain supplements, and nicotine for several weeks to ensure safe healing and permanent results.

  • Testosterone & Estrogen Panel: To check for hormonal fluctuations that may be contributing to tissue growth.

  • Chest Ultrasound: Sometimes used to differentiate between fatty tissue (adipose) and glandular breast tissue.

  • Basic Blood Panel: To evaluate hemoglobin levels, kidney function, and blood clotting ability.

  • ECG: Performed to monitor heart health during the 1.5 to 3-hour procedure.

  • Hospital Stay: Usually performed as an outpatient procedure; patients return home the same day.

  • Compression Therapy: A compression vest must be worn 24/7 for the first 3–4 weeks to ensure the skin adheres properly to the muscle.

  • Activity Timeline: Most patients return to desk work within 1 week. Light lower-body exercise is permitted by week 3.

  • Full Gym Access: Heavy lifting and chest-specific exercises (like bench presses) are typically restricted until the 6-week mark.

  • Masculine Chest Contour: Creates a flatter, firmer, and more traditionally masculine appearance.

  • Permanent Results: Provided the patient maintains a stable weight and avoids triggering substances, the removed tissue does not return.

  • Enhanced Confidence: Significantly improves self-esteem and comfort in tight-fitting clothing or at the beach/gym.

  • Minimal Scarring: Incisions placed along the border of the areola become nearly invisible once fully healed.

Breast Reduction Surgery

Breast Reduction, or reduction mammoplasty, is a surgical procedure in 2026 designed to remove excess breast fat, glandular tissue, and skin. Unlike many other cosmetic surgeries, it is frequently performed for functional and medical reasons to alleviate physical discomfort and improve a patient's overall quality of life.

This procedure is primarily recommended for individuals whose breast size causes physical pain or limits daily activities. Key indications include:

  • Chronic Pain: Persistent back, neck, and shoulder pain caused by the weight of large breasts.

  • Shoulder Grooving: Deep indentations in the shoulders caused by bra straps.

  • Skin Irritation: Chronic rashes or infections in the fold beneath the breasts (intertrigo).

  • Restricted Activity: Difficulty participating in sports or physical exercise due to breast size.

  • Postural Issues: Noticeable slumping or spinal discomfort caused by a heavy chest.

  • Vertical (Lollipop) Incision: An incision around the areola and a vertical line down to the breast crease; used for moderate reductions.

  • Inverted-T (Anchor) Incision: The most common technique for significant reductions, involving an incision around the areola, a vertical line, and a horizontal line along the breast fold.

  • Liposuction-Assisted Reduction: Sometimes used in 2026 as a standalone for fatty breast tissue or in combination with traditional methods to refine the lateral contours.

  • Nipple-Areola Repositioning: Shifting the nipple to a higher, more youthful position while maintaining its blood and nerve supply.

  • Areola Reduction: Reducing the diameter of the areola to ensure it is in proportion with the new breast size.

  • Surgical Access: Incisions are made following the chosen pattern (Lollipop or Anchor) to allow the surgeon to reach the underlying tissue.

  • Tissue Removal: The surgeon removes excess glandular tissue, fat, and skin to achieve the target weight and volume.

  • Reshaping and Lifting: The remaining breast tissue is reshaped and lifted into a higher, firmer position on the chest wall.

  • Nipple Relocation: The nipple-areola complex is moved upward to the center of the new breast mound.

  • Closure: The incisions are closed with multi-layered sutures, and surgical drains may be placed to prevent fluid accumulation during the initial 48 hours.

  • Fasting: Patients are typically required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Standard blood tests, an ECG, and a baseline mammogram are mandatory for surgical safety.

  • Documentation of Symptoms: In 2026, many insurance providers require documented proof of chronic pain or rashes to approve coverage.

  • Nicotine Cessation: Patients must stop all nicotine use several weeks before and after surgery to ensure proper blood flow and wound healing.

  • Mammogram: Essential to confirm breast health and identify any abnormalities before the tissue is modified.

  • Basic Blood Panel: To assess overall health markers, including hemoglobin and clotting function.

  • ECG: Performed to monitor the heart's rhythm during the 2 to 4-hour procedure under general anesthesia.

  • Tissue Weight Calculation: Surgeons often estimate the weight of tissue to be removed (in grams) to meet insurance requirements for medical necessity.

  • Hospital Stay: Often performed as an outpatient procedure, though some patients may stay 1 day for observation.

  • Initial Milestones: Most patients return to light daily activities and desk work within 1 week.

  • Activity Restrictions: No lifting heavier than 5–10 lbs (including groceries or children) for the first 3 to 4 weeks.

  • Long-Term Healing: Breasts settle into their permanent shape over 6 to 12 months, and scars continue to fade and flatten over the first year.

  • Physical Pain Relief: Significant and often immediate reduction in back, neck, and shoulder pain.

  • Improved Posture: Relieves the strain on the spine, allowing for a more upright and comfortable stance.

  • Increased Mobility: Makes physical exercise and sports significantly more comfortable and accessible.

  • Enhanced Body Proportion: Creates a balanced silhouette that better fits the patient's frame and clothing.

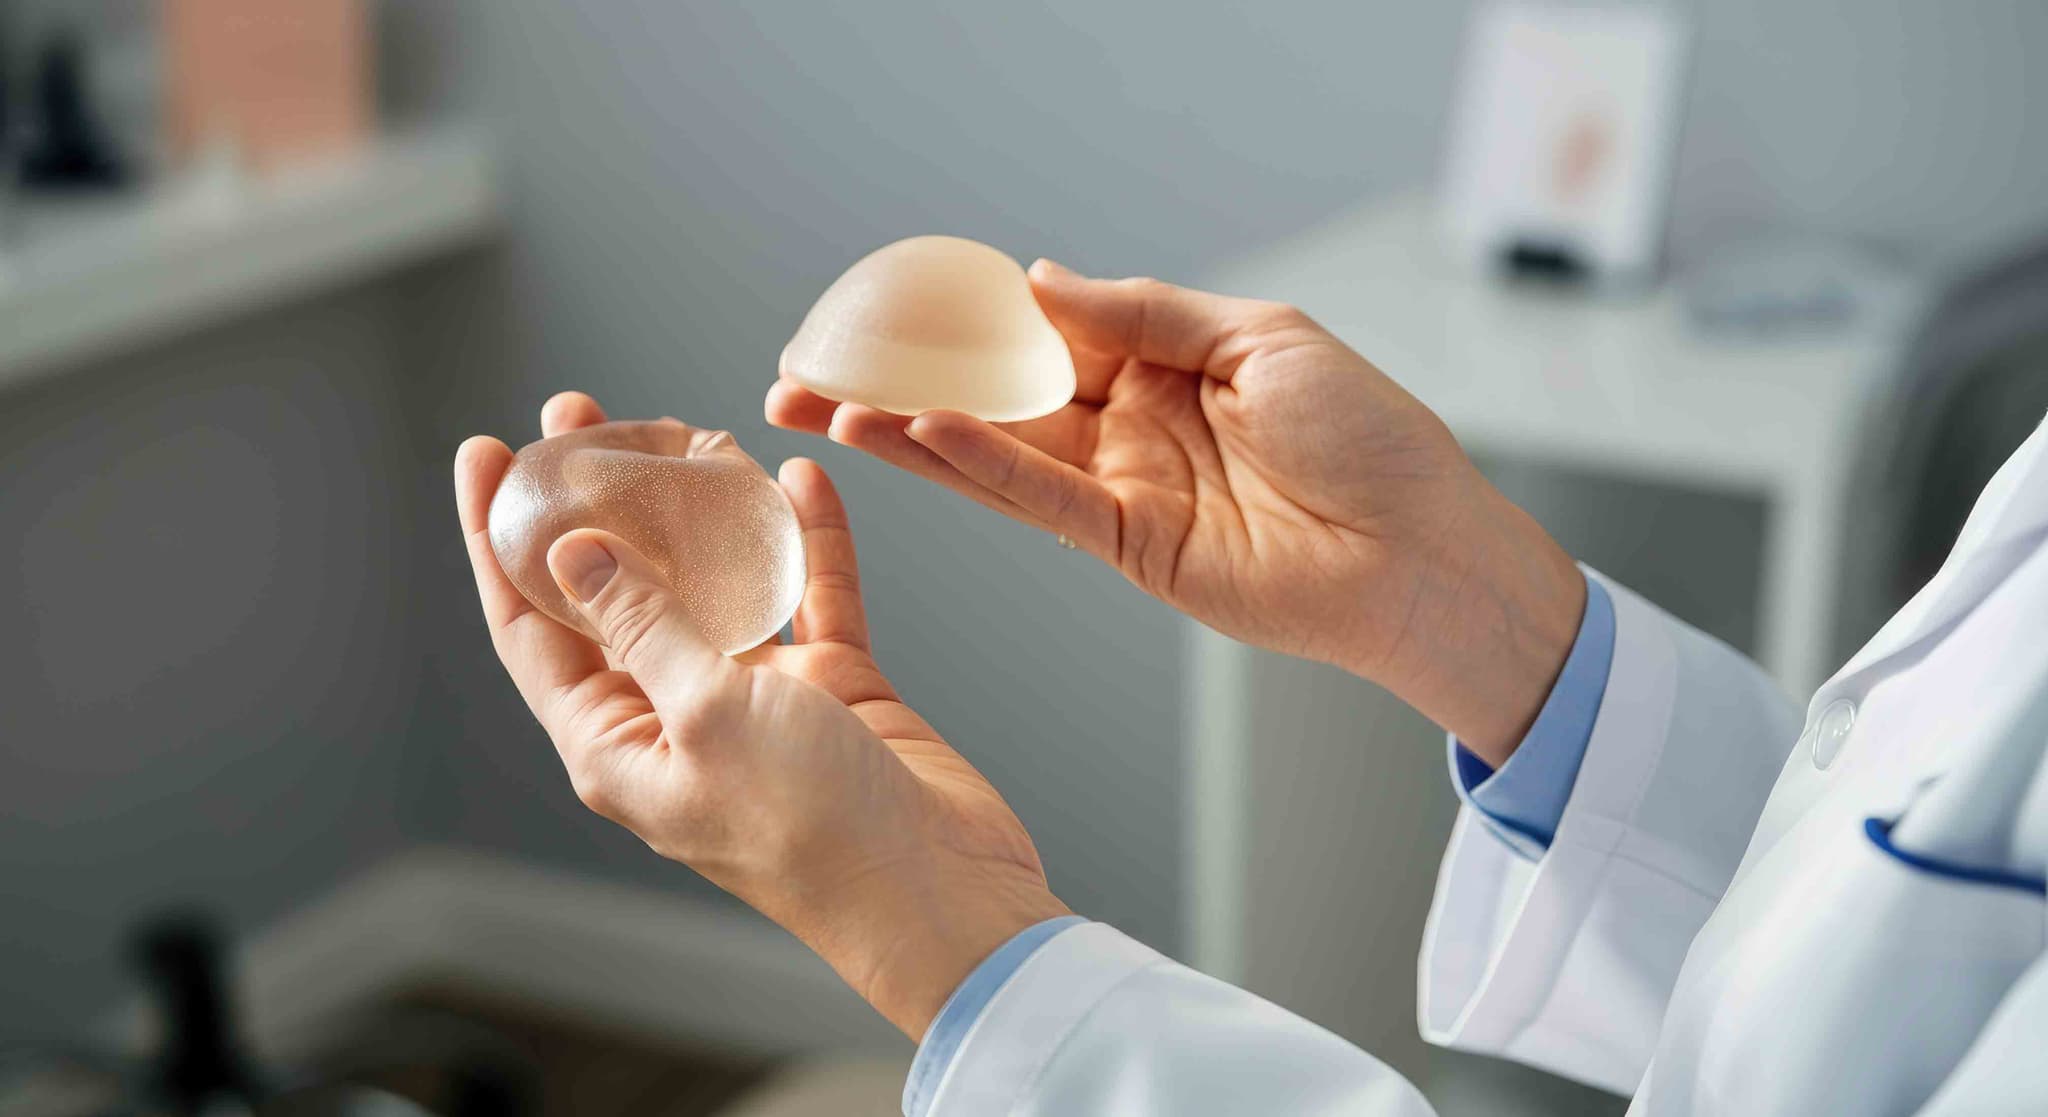
Breast Implants (Augmentation)

Breast Augmentation, or "augmentation mammoplasty," is a surgical procedure to increase breast size, change shape, or improve symmetry. In 2026, the focus has shifted toward "Natural Look" results, utilizing highly cohesive silicone gels and "hybrid" techniques that combine implants with the patient's own fat for a seamless finish.

This procedure is ideal for individuals looking to enhance their silhouette or restore volume. Key indications include:

  • Volume Loss: Restoring fullness lost due to pregnancy, breastfeeding, or significant weight loss.

  • Micromastia: Addressing naturally small breast size to achieve desired body proportions.

  • Asymmetry: Correcting significant differences in size or shape between the two breasts.

  • Cosmetic Refinement: Enhancing the "cleavage" area or improving the overall contour of the breast mound.

  • Reconstructive Needs: Following previous surgeries or injuries to restore a balanced appearance.

  • Silicone Gel Implants: The 2026 standard "gummy bear" implants that maintain their shape and provide a natural feel.

  • Saline Implants: Filled with sterile salt water; these allow for smaller incisions as they are filled after placement.

  • Hybrid Breast Augmentation: A modern technique combining a smaller implant with fat grafting (liposuction) to create softer edges.

  • Submuscular Placement: Placing the implant under the chest muscle for better coverage and a more natural look.

  • Subglandular Placement: Placing the implant over the muscle, typically offering a shorter initial recovery time.

  • Surgical Access: Incisions are made in discrete locations, such as the breast crease (inframammary), around the nipple (periareolar), or the armpit (transaxillary).

  • Pocket Creation: The surgeon creates a space either above or below the pectoral muscle to house the implant.

  • Implant Insertion: The selected implant is carefully placed and positioned to ensure optimal symmetry and contour.

  • "Internal Bra" Support: In some 2026 cases, surgical mesh (ADMs) is used to provide extra internal support and prevent the implant from shifting.

  • Closure: The incisions are closed with multi-layered sutures, and a surgical support bra is applied to stabilize the new volume.

  • Fasting: Patients are typically required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Standard blood tests, an ECG, and a baseline mammogram are required to ensure patient safety.

  • Nicotine Cessation: Stopping all nicotine products several weeks before and after surgery is essential to prevent healing complications.

  • Medication Review: Avoiding medications like aspirin or ibuprofen that can increase the risk of post-operative bruising.

  • Mammogram: Essential for documenting breast health and ensuring no underlying masses are present before surgery.

  • Basic Blood Panel: To evaluate overall health, hemoglobin levels, and clotting function.

  • ECG: Performed to monitor heart health during the 1 to 2-hour procedure under general anesthesia.

  • Pregnancy Test: To ensure the patient is not currently pregnant before undergoing anesthesia and surgery.

  • Hospital Stay: Usually performed as an outpatient procedure; patients return home the same day.

  • Initial Milestones: Most patients return to non-strenuous desk work within 1 week.

  • Activity Restrictions: Upper-body workouts and heavy lifting are restricted for 4 to 6 weeks.

  • Long-Term Settling: Implants typically "drop and fluff" (settle into their natural position) over a period of 3 to 6 months.

  • Enhanced Body Proportion: Creates a balanced silhouette and improves the fit of clothing and swimwear.

  • Restored Fullness: Effectively addresses "deflated" breast tissue following life events like pregnancy or weight loss.

  • High Safety Standards: Modern 2026 cohesive gel implants and smooth surfaces offer high durability and lower complication rates.

  • Boosted Self-Confidence: Resolves long-standing concerns regarding breast size or symmetry with immediate, visible results.

Breast Lift Surgery (Mastopexy)

A Breast Lift, or mastopexy, is a surgical procedure designed to raise and firm the breasts by removing excess skin and tightening the surrounding tissue. It is primarily used to correct "ptosis" (sagging) caused by pregnancy, breastfeeding, weight fluctuations, or the natural aging process.

This procedure is ideal for individuals who are satisfied with their breast size but unhappy with the position or shape. Key indications include:

  • Breast Ptosis: Breasts that have lost their youthful shape and begun to sag.

  • Nipple Position: Nipples that point downward or fall below the breast crease.

  • Stretched Skin: Loss of skin elasticity leading to a "heavy" or pendulous appearance.

  • Large Areolas: Enlarged areolas that have stretched over time and are out of proportion with the breast.

  • Post-Weight Loss/Pregnancy: Changes in breast volume and skin tightness following significant life events.

  • Crescent Lift: A minor lift involving a small incision along the top half of the areola.

  • Peri-Areolar (Donut) Lift: A circular incision around the entire areola, ideal for mild sagging.

  • Vertical (Lollipop) Lift: An incision around the areola and a vertical line down to the breast crease, used for moderate sagging.

  • Inverted-T (Anchor) Lift: The most comprehensive technique for major sagging, involving incisions around the areola, vertically down, and along the breast crease.

  • Internal Bra Technique: A 2026 trend using specialized mesh or sutures to provide extra internal support and long-term stability.

  • Surgical Access: Incisions are made based on the chosen technique (Crescent, Lollipop, or Anchor) to access the underlying tissue.

  • Reshaping: The surgeon lifts and reshapes the breast tissue to create a firmer, more youthful contour.

  • Nipple Repositioning: The nipple and areola are moved to a higher, more centered position on the breast mound.

  • Skin Removal: Excess, stretched skin is carefully trimmed away to tighten the remaining envelope.

  • Closure: Incisions are closed with fine sutures, and a specialized surgical support bra is typically applied immediately.

  • Fasting: Patients are typically required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Standard blood tests, an ECG, and often a baseline mammogram are required for patients over a certain age.

  • Medication Review: Avoiding aspirin, anti-inflammatory drugs, and certain supplements that can increase bleeding risks.

  • Nicotine Cessation: Stopping all nicotine products several weeks before and after surgery is mandatory to ensure proper wound healing.

  • Mammogram: To ensure breast health and establish a baseline before changing the breast architecture.

  • Basic Blood Panel: To evaluate overall health, hemoglobin levels, and clotting function.

  • ECG: Performed to monitor heart health during the 2 to 3-hour procedure under general anesthesia.

  • Physical Assessment: To determine the grade of ptosis and select the appropriate incision technique.

  • Hospital Stay: Usually performed as an outpatient procedure, with patients returning home the same day.

  • Initial Milestones: Most patients return to desk work and light daily activities within 1 week.

  • Activity Restrictions: No heavy lifting or high-impact exercise (like running) for 4 to 6 weeks.

  • Support Garments: A surgical bra must be worn initially, followed by a supportive sports bra; underwire bras must be avoided for at least 6 to 8 weeks.

  • Youthful Contour: Restores a firmer, higher, and more aesthetically pleasing breast shape.

  • Improved Body Proportion: Repositions the nipples and reshapes the breast mound to better suit the patient's frame.

  • Clothing Fit: Allows for a wider range of clothing and swimwear styles to fit more comfortably and attractively.

  • Long-Term Transformation: Provides a durable correction that can be further enhanced when combined with implants (Mastopexy-Augmentation).

Brow Lift Surgery (Browplasty)

A Brow Lift, or forehead lift, is a surgical procedure designed to reposition a sagging or "hooded" brow, reduce forehead wrinkles, and open up the appearance of the eyes. It is frequently combined with blepharoplasty (eyelid surgery) for a complete and harmonious upper-face rejuvenation.

A brow lift is ideal for patients who look "tired," "sad," or "angry" even when well-rested. Key indications include:

  • Sagging Brows: Eyebrows that have dropped into a low position, creating a heavy appearance.

  • Hooded Eyes: Excess skin from the brow area weighing down the upper eyelids.

  • Forehead Furrows: Deep horizontal wrinkles across the forehead that do not respond to non-surgical treatments.

  • Frown Lines: Vertical creases between the eyebrows (glabellar lines).

  • Asymmetrical Brows: When one eyebrow is significantly lower than the other.

  • Endoscopic Brow Lift: The most common modern technique, utilizing a tiny camera and specialized tools through small incisions hidden within the hair.

  • Temporal (Lateral) Brow Lift: Focuses specifically on lifting the outer corners or "tails" of the eyebrows.

  • Trichophytic Brow Lift: An incision is made at the hairline, specifically designed for patients who wish to lift the brow while lowering a high hairline.

  • Coronal Brow Lift: The traditional method involving an ear-to-ear incision; reserved for severe sagging cases.

  • Non-Surgical Brow Lift: Using neurotoxins or thread lifts for temporary elevation without surgery.

  • Surgical Access: Depending on the technique, small incisions are made within the hair or along the hairline to ensure scars remain hidden.

  • Tissue Repositioning: The surgeon lifts the skin and underlying tissues of the forehead to a more youthful, elevated position.

  • Muscle Modification: The muscles that cause deep frown lines are weakened or released to smooth the forehead surface.

  • Securing the Lift: Specialized sutures, screws, or absorbable devices are used to hold the brow in its new position during the healing process.

  • Closure: The incisions are closed with sutures or surgical staples, and the head is typically wrapped in a supportive bandage.

  • Fasting: Patients are typically required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Comprehensive blood tests and a physical exam are conducted to ensure fitness for anesthesia.

  • Hair Care: Patients may be asked to wash their hair with antimicrobial soap but avoid any chemical treatments (dyes/perms) several days prior.

  • Medication Review: Avoiding aspirin and anti-inflammatory drugs for 2 weeks to minimize the risk of bruising and bleeding.

  • Basic Blood Panel: To evaluate overall health and ensure proper blood clotting.

  • ECG: Performed for older patients to monitor heart rhythm during the 1 to 2-hour procedure.

  • Physical Assessment: To evaluate the degree of brow ptosis (sagging) and forehead skin elasticity.

  • 3D Facial Mapping: Often used to plan the desired height and arch of the brow for a natural result.

  • Hospital Stay: Usually performed as an outpatient procedure; patients return home the same day.

  • Initial Milestones: Bandages are removed within 1–3 days; sutures or staples are typically removed by the end of the first week.

  • Scalp Management: Temporary numbness or itching on the scalp is common and usually resolves within a few months.

  • Activity Timeline: Most patients return to work within 2 weeks; strenuous exercise can typically be resumed after 1 month.

  • Refreshed Appearance: Eliminates the "tired" or "angry" look by opening up the eye area.

  • Smoother Forehead: Significantly reduces deep horizontal furrows and frown lines for a more youthful look.

  • Long-Lasting Results: Provides a durable correction that typically remains effective for 10 to 12 years.

  • Natural-Looking Scars: Advanced endoscopic techniques ensure that surgical marks are completely concealed within the hairline.

Asymmetrical Face (Facial Implant Surgery)

A Facelift, or rhytidectomy, is a major surgical procedure in 2026 designed to rejuvenate the face by repositioning skin and tightening the underlying muscles. It is the most comprehensive solution for addressing sagging tissues caused by aging, gravity, and the loss of facial volume.

This procedure is ideal for individuals looking to reverse significant signs of facial aging. Key indications include:

  • Formation of Jowls: Loose skin and fat deposits along the jawline.

  • Sagging Cheeks: Loss of mid-face volume and downward displacement of cheek tissues.

  • Loose Neck Skin: Often referred to as "turkey neck" or prominent vertical bands in the neck.

  • Deep Nasolabial Folds: Deepening creases running from the nose to the corners of the mouth.

  • Facial Tissue Laxity: General sagging that does not respond to non-surgical fillers or skin tightening treatments.

  • Full Facelift: The standard approach for significant aging, addressing the lower face, jawline, and neck.

  • Mini Facelift: A less invasive option focusing on the jawline and jowls, ideal for moderate sagging with shorter recovery times.

  • Deep Plane Facelift: An advanced technique that lifts the muscle and skin as one unit for superior mid-face rejuvenation.

  • SMAS (Superficial Musculoaponeurotic System) Lift: Focuses on tightening the muscular layer beneath the skin to ensure a natural, long-lasting look.

  • Neck Lift: Specifically targets the area under the chin and the neck muscles, often performed in conjunction with a facelift.

  • Surgical Access: Incisions are strategically placed in the hairline at the temples and continue around the ear to ensure scars are hidden in natural folds.

  • Muscle Repositioning: The surgeon lifts and tightens the SMAS layer (the underlying muscle) to provide a structural foundation for the face.

  • Skin Redraping: The skin is carefully draped over the newly contoured facial structures, and excess skin is trimmed away.

  • Closing the Incisions: Fine sutures are used to close the incisions, and the head is typically wrapped in a compression bandage to manage swelling.

  • Verification: The surgeon ensures facial symmetry and a natural "un-pulled" appearance before concluding the procedure.

  • Fasting: Patients are typically required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Comprehensive blood tests and a physical exam are conducted to ensure fitness for general anesthesia.

  • Smoking Cessation: Patients must quit smoking and vaping several weeks before and after surgery to prevent tissue necrosis and ensure healthy blood flow.

  • Medication Review: Avoiding aspirin and blood-thinning supplements to minimize the risk of hematoma or excessive bruising.

  • Basic Blood Panel: To evaluate health markers and clotting ability.

  • ECG: To monitor heart rhythm and ensure safety during a 3 to 6-hour procedure.

  • Physical Assessment: To evaluate skin elasticity, bone structure, and the degree of tissue laxity.

  • 3D Facial Imaging: Often used to simulate potential outcomes and plan the surgical trajectory.

  • Hospital Stay: Usually performed as an outpatient procedure, though some patients may stay 1 day for observation.

  • Initial Milestones: Compression bandages are typically removed within 48 hours; sutures are removed by the end of the first week.

  • Activity Timeline: Most patients return to work or social settings within 2 to 3 weeks; light exercise is generally permitted after 1 month.

  • Long-Term Care: Scars must be protected from sun exposure for 6 to 12 months, and results typically remain effective for 10 to 15 years.

  • Natural Rejuvenation: Modern techniques avoid the "wind-tunnel" look by focusing on muscle tightening rather than just skin stretching.

  • Long-Lasting Results: Provides a decade or more of improved facial contour compared to temporary non-surgical options.

  • Comprehensive Correction: Addresses the face and neck simultaneously for a harmonious and youthful appearance.

  • Enhanced Jawline Definition: Effectively eliminates jowls and tightens the neck for a sharper, more defined profile.

Rhinoplasty Nose Surgery

Rhinoplasty, or nose reshaping, is a highly individualized surgical procedure designed to enhance facial harmony or improve nasal function. In 2026, modern techniques like preservation rhinoplasty—which maintains the nose's natural framework rather than removing it—are the standard for achieving authentic, long-lasting results.

This procedure is recommended for both aesthetic refinement and the correction of functional breathing issues. Key indications include:

  • Facial Imbalance: A nose that is disproportionately large, small, or wide in relation to other facial features.

  • Nasal Humps or Depressions: Visible bumps or "scoops" on the bridge of the nose.

  • Deviated Septum: Internal structural issues that cause chronic nasal congestion or difficulty breathing.

  • Tip Deformity: A nasal tip that is bulbous, drooping, or upturned.

  • Post-Traumatic Repair: Correcting nasal deformities or fractures caused by previous injuries.

  • Open Rhinoplasty: Involves a small incision across the columella for maximum visibility during complex structural changes.

  • Closed Rhinoplasty: All incisions are made inside the nostrils, leaving no visible external scars.

  • Functional Rhinoplasty (Septorhinoplasty): Focuses on repairing internal structures to improve breathing while simultaneously refining the shape.

  • Preservation Rhinoplasty: A modern approach that reshapes the nose by adjusting existing tissue rather than removing significant amounts of bone and cartilage.

  • Non-Surgical Rhinoplasty: A temporary option using dermal fillers to smooth bumps or improve symmetry without surgery.

  • Surgical Access: Depending on the method, incisions are placed either inside the nostrils or across the narrow strip of skin between them.

  • Reshaping: The surgeon carefully adjusts the underlying bone and cartilage to achieve the desired shape or to clear obstructed airways.

  • Structural Support: In 2026 practice, cartilage grafts (often from the septum) may be used to reinforce the nasal tip or bridge for long-term stability.

  • Closure: The skin is redraped over the new framework, and incisions are closed with fine sutures.

  • Splinting: An external splint is typically applied to protect and support the new nasal structure during the first week of healing.

  • Fasting: Patients are required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Comprehensive blood tests and a physical exam are conducted to ensure the patient is fit for general anesthesia.

  • Smoking Cessation: Patients must quit smoking and vaping several weeks before and after surgery to prevent tissue necrosis and ensure proper blood flow.

  • Medication Review: Avoiding aspirin, ibuprofen, and certain herbal supplements that can increase bleeding risks.

  • Nasal Endoscopy: A detailed internal examination to check for a deviated septum, polyps, or other obstructions.

  • 3D Facial Mapping: High-resolution digital imaging used to plan the surgery and simulate potential aesthetic outcomes.

  • Standard Blood Panel: To confirm healthy hemoglobin levels and clotting function.

  • ECG: To monitor heart health and ensure safety during the procedure.

  • Hospital Stay: Usually performed as an outpatient procedure, allowing the patient to return home the same day.

  • Initial Milestones: The external splint is removed after 1 week. Most patients return to work or light activities by the end of week 2.

  • Activity Restrictions: No nose blowing for 2–3 weeks and no heavy eyewear resting on the bridge for 4–6 weeks.

  • Long-Term Evolution: While 80% of swelling subsides within 3 months, the final refined shape of the nasal tip may take up to a year to fully emerge.

  • Enhanced Facial Symmetry: Provides a balanced appearance by aligning the nose with the forehead, chin, and cheeks.

  • Improved Respiratory Function: Corrects internal blockages, leading to better sleep and easier breathing during physical activity.

  • Boosted Self-Confidence: Resolves long-standing insecurities regarding nasal shape or size.

  • Permanent Results: Surgical rhinoplasty provides a lifelong correction of both aesthetic and structural concerns.

Abdominoplasty (Tummy Tuck)

Abdominoplasty, or a tummy tuck, is a major surgical procedure designed to remove excess abdominal skin and fat while tightening weakened or separated muscles. It is most commonly sought after pregnancy or significant weight loss when the skin lacks the natural elasticity to retract on its own.

This procedure is ideal for individuals who have stabilized their weight but struggle with abdominal concerns that do not respond to diet or exercise. Key indications include:

  • Skin Laxity: Loose, sagging skin on the abdomen following pregnancy or massive weight loss.

  • Diastasis Recti: Separation of the abdominal muscles, which often causes a persistent protrusion or "bulge."

  • Excess Stubborn Fat: Localized fat deposits in the midsection that resist traditional weight loss methods.

  • Poor Core Stability: Weakened abdominal walls that contribute to back pain or poor posture.

  • Significant Contouring Needs: When a patient is at their goal weight but desires a firmer, flatter midsection.

  • Full (Standard) Abdominoplasty: Addresses both the upper and lower abdomen, involving a hip-to-hip incision and repositioning of the navel.

  • Mini Tummy Tuck: Focuses specifically on the area below the belly button with a smaller incision and no navel repositioning.

  • Extended Tummy Tuck: Targets the abdomen and the flanks (love handles) for a more comprehensive body contour.

  • Fleur-de-lis Abdominoplasty: Utilizes both vertical and horizontal incisions for patients with significant skin redundancy following massive weight loss.

  • Lipo-Abdominoplasty: Combines the skin tightening of a tummy tuck with liposuction for superior contouring and definition.

  • Surgical Access: A horizontal incision is made low on the abdomen, strategically placed to be hidden by swimwear or undergarments.

  • Muscle Repair: The surgeon pulls the weakened or separated abdominal muscles together and stitches them into a tighter, firmer position.

  • Tissue Removal: Excess skin and fat are carefully trimmed away to create a smooth abdominal profile.

  • Navel Repositioning: In full procedures, the belly button is brought through a new opening to maintain a natural appearance.

  • Closure and Drains: The incisions are closed with sutures, and surgical drains may be placed to prevent fluid accumulation during early healing.

  • Fasting: Patients are typically required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Comprehensive blood tests and an ECG are conducted to ensure the patient is fit for general anesthesia.

  • Smoking Cessation: Patients must quit smoking several weeks before and after surgery to prevent tissue necrosis and healing complications.

  • Medication Review: Adjusting medications, specifically blood thinners or certain supplements, as directed by the surgical team.

  • Basic Blood Panel: To check hemoglobin levels and ensure there are no underlying infections.

  • ECG: To monitor the heart's rhythm and ensure safety during a procedure that lasts 2 to 5 hours.

  • Physical Assessment: To measure skin elasticity and the degree of muscle separation (diastasis recti).

  • Pregnancy Test: To ensure the patient is not currently pregnant, as the procedure is not recommended during or immediately before pregnancy.

  • Hospital Stay: Depending on the complexity, patients may go home the same day or stay for 1–2 days for observation.

  • Support Garments: A compression garment or abdominal binder must be worn 24/7 for approximately 6 weeks to reduce swelling.

  • Activity Restrictions: Light walking is encouraged immediately; however, heavy lifting (over 5–10 lbs) and strenuous exercise must be avoided for 6–8 weeks.

  • Long-Term Results: Final contours typically emerge within 3 to 6 months, while scars continue to fade over 12 to 18 months.

  • Improved Core Strength: Tightening the abdominal muscles provides better support for the spine and reduces back pain.

  • Enhanced Body Contour: Removes "overhanging" skin and stubborn fat for a flatter, firmer appearance.

  • Clothing Fit: Patients often find that clothing fits more comfortably and look more tailored to their frame.

  • Long-Term Solution: Provides permanent removal of excess skin and fat, assuming the patient maintains a stable weight.

Pericardiocentesis
Pericardiocentesis

Pericardiectomy is a surgical procedure to remove part or all of the pericardium, the thin sac surrounding the heart. This surgery is performed to allow the heart to move and pump freely when the sac has become diseased, scarred, or restrictive.

  • Persistent fatigue or weakness during physical exertion

  • Significant swelling in the legs, ankles, or abdomen (edema)

  • Shortness of breath, especially when lying down or exercising

  • Chronic chest pain that does not improve with medication

  • Signs of heart failure caused by a restrictive or stiff heart sac

  • Constrictive Pericarditis: The sac becomes stiff, thick, or calcified, preventing heart expansion.

  • Recurrent Pericarditis: Chronic inflammation that fails to respond to standard medical treatments.

  • Persistent Pericardial Effusion: Frequent or dangerous buildup of fluid around the heart.

  • Partial Agenesis: A rare congenital defect where part of the pericardium is missing.

  • Post-Viral Scarring: Long-term thickening of the sac following a severe viral infection.

  • Anesthesia: The surgery is performed under general anesthesia and typically takes 2 to 3 hours.

  • Approach: Surgeons usually use a median sternotomy (breastbone incision) to access the heart.

  • Support: A heart-lung bypass machine is often used to maintain circulation during the surgery.

  • Removal: The surgeon carefully removes the damaged or scarred pericardial tissue.

  • Closing: Once the heart is free to expand fully, the incision is closed with sutures or staples.

  • Hospital Stay: Patients typically remain in the hospital for 5 to 7 days for close monitoring.

  • Monitoring: The medical team tracks heart rhythm, fluid levels, and lung function post-surgery.

  • Initial Healing: Pain management and respiratory therapy are prioritized during the first week.

  • Full Recovery: It generally takes 6 to 8 weeks to return to normal daily activities and work.

  • Activity: Gradual walking and light movement are encouraged to prevent blood clots.

  • Surgical Cure: This is often a definitive cure for constrictive pericarditis.

  • Survival Rate: Long-term survival is approximately 80% at 5 years, depending on the cause.

  • Potential Risks: Includes standard heart surgery risks like infection, bleeding, or blood clots.

  • Arrhythmias: Some patients may experience temporary abnormal heart rhythms during recovery.

  • Success Factor: Outcomes are generally excellent when the surgery is performed before heart damage occurs.

  • Restores the heart's ability to fill with blood and expand normally

  • Immediate relief from the restrictive pressure causing heart failure symptoms

  • Significant reduction in fluid retention and swelling throughout the body

  • Improved physical stamina and the ability to return to an active lifestyle

  • Eliminates the need for long-term anti-inflammatory medications in chronic cases

URS (Ureteroscopy)
URS (Ureteroscopy)

URS (Ureteroscopy) is a minimally invasive surgical procedure used to diagnose and treat issues in the urinary tract, most commonly kidney stones located in the ureter or kidney. Because the procedure utilizes the body's natural openings, it requires no external incisions or surgical cuts. This advanced endoscopic approach allows urologists to reach and treat stones that are too large or too high to pass on their own, often providing immediate relief from renal colic.

  • Obstructing Ureteral Stones: When a stone is stuck in the ureter, causing severe pain, nausea, or potential kidney damage.

  • Large Kidney Stones: For stones located within the kidney that are unlikely to pass naturally or are causing chronic discomfort.

  • Failed Shockwave Therapy: If previous non-invasive treatments (like ESWL) have failed to break the stone into small enough pieces.

  • Diagnostic Necessity: To investigate the cause of blood in the urine (hematuria) or to biopsy suspicious lesions within the ureter or renal pelvis.

  • Bilateral Stones: When stones are present in both ureters, URS can sometimes address both sides in a single surgical session.

  • Access: A urologist inserts a thin, flexible, or rigid lighted telescope called a ureteroscope through the urethra and bladder, guiding it carefully up into the ureter or kidney.

  • Anesthesia: The surgery is typically performed under general anesthesia and usually takes between 30 minutes to 2 hours, depending on the size and number of stones.

  • Visualization: A sterile saline solution is used to gently expand the bladder and ureter, providing a clear 3D view of the stones and the urinary tract lining.

  • Treatment:
    Small Stones: These are captured and removed whole using a specialized tiny wire basket device.
    Larger Stones: These are fragmented into tiny, dust-like pieces using a high-precision Holmium laser beam.

  • Stone Extraction: Once fragmented, the pieces are either extracted with the basket or left to pass naturally and painlessly in the urine.

  • Stent Placement: Frequently, a small temporary tube called a ureteral stent (JJ stent) is placed in the ureter at the end of the procedure to ensure proper urine drainage and to manage internal swelling.

  • Imaging (CT or KUB): High-resolution scans to determine the exact size, density, and location of the stones.

  • Urine Culture: To ensure there is no active urinary tract infection (UTI) before the instruments are introduced.

  • Medication Audit: You may be asked to stop taking blood thinners (like aspirin or warfarin) several days before the procedure to minimize bleeding.

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Hydration: Your doctor may encourage increased fluid intake in the days leading up to the procedure to help flush the urinary system.

  • Urinalysis: To check for signs of infection, blood, or crystals in the urine.

  • Blood Panels: A routine check of your blood count, electrolytes, and kidney function (creatinine and BUN levels).

  • ECG: A standard heart check to confirm cardiovascular stability for the duration of the procedure.

  • Coagulation Profile: To ensure your blood clots normally, which is essential for a safe endoscopic procedure.

  • Recovery Timeline: URS is often an outpatient procedure, allowing most patients to go home the same day. Most can resume light activities within 2 to 3 days, with a full recovery typically taking one week.

  • Initial Symptoms: For the first 24–48 hours, it is normal to experience mild pelvic pain, pinkish or reddish blood in the urine, and a frequent urge to urinate.

  • Critical Hydration: It is essential to drink 2–3 liters of water daily to flush out any remaining stone fragments and residual blood.

  • Stent Removal: If a stent was placed, it is typically removed in a quick, separate outpatient procedure 4 to 14 days after the surgery.

  • Activity Restrictions: Avoid heavy lifting and strenuous exercise for at least one week to allow the ureter to heal and reduce the risk of bleeding.

  • Immediate Stone Clearance: Unlike medications, URS offers the fastest way to physically remove an obstructing stone and stop the associated pain.

  • No Surgical Scars: By using the body's natural pathways, there is zero impact on your physical appearance and no wound care is required.

  • High Success Rate: Modern laser technology can break even the hardest stones (such as calcium oxalate monohydrate) that other treatments cannot touch.

  • Protects Kidney Function: Rapidly removing an obstruction prevents the backup of urine (hydronephrosis), which can lead to permanent kidney scarring or infection.

  • Precision Mapping: The high-definition cameras on modern ureteroscopes allow for a thorough inspection of the entire upper urinary tract, ensuring no small stones are left behind.

Percutaneous Nephrolithotomy (PCNL)

Percutaneous Nephrolithotomy (PCNL) is a minimally invasive "keyhole" surgery specifically used to remove large kidney stones—usually those over 2 cm—that cannot be passed naturally or treated effectively with standard shockwave therapy. This procedure allows surgeons to reach the kidney through a tiny incision in the back, providing a direct route to extract complex or "staghorn" stones that would otherwise require major open surgery.

  • Large Kidney Stones: Specifically those larger than 2 cm in diameter which are too substantial for laser ureteroscopy or shockwave lithotripsy.

  • Staghorn Calculi: Complex stones that branch out to fill the various drainage channels (calyces) of the kidney.

  • Failed Previous Treatments: When other non-invasive methods have failed to break or clear the stone.

  • Stones in Diverticula: When a stone is trapped in a small outpouching of the kidney that is difficult to access through the ureter.

  • Cystine or Stones of High Density: Very hard stones that are resistant to being broken by external sound waves.

  • Anesthesia: The surgery is performed under general anesthesia, ensuring you are completely asleep and comfortable throughout the procedure.

  • Positioning: You are typically placed in a prone (face-down) or supine (face-up) position to allow the surgeon precise access to the kidney through the flank.

  • The Incision: A small, "keyhole" incision (approximately 1 cm) is made in your flank area (the side of your back).

  • Access & Fragmentation:
    A protective sleeve is inserted through the incision directly into the kidney's collecting system.
    A nephroscope (a specialized thin camera) is passed through the sleeve to locate the stone under high magnification.
    If the stone is too large to remove whole, the surgeon uses a lithotripter (a laser, ultrasound, or pneumatic device) to fragment the stone into smaller, manageable pieces.

  • Extraction: The fragments are then physically removed from the kidney using specialized graspers or suction.

  • Drainage: To ensure the kidney heals properly, a nephrostomy tube (draining to an external bag) or an internal ureteral stent is often left in place temporarily.

  • Medical Evaluation: Comprehensive blood and urine tests to rule out active infection and assess kidney function.

  • Advanced Mapping: A high-resolution CT scan or intravenous pyelogram (IVP) to map the exact 3D location of the stones and the surrounding anatomy.

  • Antibiotic Protocol: A preventative dose of antibiotics is administered to minimize the risk of post-surgical infection.

  • Fasting: Adhering to "nothing by mouth" instructions after midnight on the night before your surgery.

  • Medication Audit: You will be asked to stop taking blood thinners (like aspirin, warfarin, or clopidogrel) several days before the procedure to prevent bleeding.

  • Urine Culture: Essential to confirm the urine is sterile before entering the kidney with surgical instruments.

  • CT Stone Protocol: A specialized scan to determine the "Hounsfield units" (density) of the stone, which helps the surgeon choose the right fragmentation tool.

  • Complete Blood Count (CBC): To establish a baseline for your red and white blood cells.

  • ECG: A standard heart check to confirm cardiovascular stability for a procedure that typically lasts 1 to 4 hours.

  • Hospital Stay: Most patients stay in the hospital for 1 to 2 days for close monitoring of kidney drainage and comfort levels.

  • Tube Management: If a nephrostomy tube was used, it is typically removed before you leave the hospital or at a quick follow-up visit a few days later.

  • Initial Symptoms: It is normal to see small amounts of blood in your urine (hematuria) or feel moderate soreness at the incision site for 1–2 weeks.

  • Activity Restrictions: Avoid strenuous activity, heavy exercise, or lifting anything heavier than 4 kg (approx. 9 lbs) for at least 2 weeks.

  • Hydration: Drinking plenty of fluids is critical to help flush out any remaining tiny microscopic stone fragments.

  • Follow-Up: A check-up is scheduled for 4 to 6 weeks after surgery, often including an X-ray or ultrasound to confirm the kidney is stone-free and functioning correctly.

  • Highest Clearance Rate: PCNL offers the highest "stone-free" rate for large and complex stones compared to any other surgical or non-surgical method.

  • Direct Extraction: Because stones are physically removed rather than just broken, there is a lower risk of fragments getting stuck in the ureter later.

  • Minimally Invasive: Despite treating large stones, the "keyhole" approach means less pain, smaller scars, and a much faster recovery than traditional open kidney surgery.

  • One-Step Solution: Even the largest staghorn stones can often be cleared in a single surgical session.

  • Protects Kidney Health: Rapidly clearing an obstructing stone prevents long-term pressure damage (hydronephrosis) and reduces the risk of recurrent kidney infections.

Extracorporeal Shockwave Lithotripsy (Non-Surgical)

Extracorporeal Shock Wave Lithotripsy (ESWL) is a purely non-invasive medical procedure. It is the only treatment that can break kidney stones from outside the body, using high-energy acoustic pulses.

  • Stone Size: ESWL is most effective for kidney stones that are under 2 cm.

  • Stone Location: Ideal for stones located in the kidney or the upper part of the ureter.

  • Symptomatic Stones: When stones cause persistent pain, urinary tract infections, or localized blockage.

  • Patient Preference: For individuals seeking a treatment option that requires no incisions, no catheters, and no internal scopes.

  • Stone Composition: Best suited for stones that are not excessively hard, such as those primarily composed of uric acid or certain calcium clusters.

  • Imaging & Mapping: The urologist uses Fluoroscopy (continuous X-ray) or Ultrasound to find the stone's exact 3D coordinates.

  • The "Coupling" Process: A water-filled cushion or a thick layer of conductive gel is placed against your back to transmit energy into the body.

  • Pain Management: While non-surgical, you are usually given sedation or a local anaesthetic block to keep you still and relaxed during the "thumping" sensation.

  • Medication Audit: Pausing blood thinners (like aspirin or warfarin) for several days prior to prevent bruising or bleeding around the kidney.

  • Fasting: Maintaining "nil per oral" (NPO) status for 6–8 hours before the procedure if sedation is being administered.

  • Shockwave Generation: A machine called a Lithotripter creates thousands of targeted shockwaves (usually 2,000 to 3,000 pulses).

  • The "Ramping" Technique: The doctor starts at a low power level to "soften" the stone and slowly increases the intensity to protect kidney tissue.

  • Direct Stress: Physical pressure from the acoustic pulses travels through the liquid "bridge" to crack the stone.

  • Cavitation: Tiny bubbles form and collapse on the stone's surface, acting like "micro-hammers" to turn the stone into "sand" or "gravel."

  • Duration: The entire fragmentation process usually takes 45 to 60 minutes.

  • KUB X-ray: A standard X-ray of the Kidneys, Ureters, and Bladder to confirm the stone is "radio-opaque" (visible to X-rays).

  • Renal Ultrasound: To check for "hydronephrosis" (swelling of the kidney) caused by the stone.

  • Non-Contrast CT Scan: The gold standard for measuring the "Hounsfield Units" (hardness) of the stone to predict if it will break.

  • Urine Culture: To ensure there is no active infection, as breaking an infected stone can release bacteria into the bloodstream.

  • Coagulation Profile: Blood tests to ensure your blood clots normally before the high-energy pulses are applied.

  • Observation: You stay in a recovery room for 1–2 hours to monitor for any reaction to the sedation or severe internal bruising.

  • Hydration Therapy: You are instructed to drink 3 to 4 litres of water daily to "wash out" the stone dust.

  • Medical Expulsive Therapy (MET): You are often prescribed Alpha-blockers (like Tamsulosin) to relax the ureter so fragments can pass with less pain.

  • Straining Urine: You will be given a fine-mesh strainer to catch pieces for chemical analysis to determine the stone's mineral type.

  • Haematuria: It is normal to see blood in the urine for 24–48 hours as fragments move through the urinary tract.

  • Follow-up Imaging: An X-ray or Ultrasound is typically done 2 to 4 weeks later to ensure the kidney is "Stone-Free."

  • Zero Incisions: As a completely extracorporeal treatment, there is a significantly lower risk of hospital-acquired infections compared to surgery.

  • Quick Recovery: Most patients return to work and normal activities within 24–48 hours after the procedure.

  • Precision Targeting: Advanced lithotripsy technology allows for real-time tracking, adjusting the focus even as the patient breathes.

  • Avoidance of General Anaesthesia: Many cases can be performed under light sedation, making it safer for elderly patients or those with heart conditions.

  • Repeatable Treatment: If a stone is particularly large, ESWL can be safely repeated or combined with other minor procedures to ensure total clearance.

Mini-PCNL / Micro-PCNL

Mini-PCNL is a "small-access" surgery used for stones between 1 cm and 2.5 cm. Micro-PCNL is an "all-in-one" needle surgery, usually reserved for stones around 1 cm to 1.5 cm.

  • Stone Size: Ideal for stones between 1 cm and 2.5 cm that are too large for ESWL but don't require standard PCNL.

  • Stone Hardness: When stones are too dense to be broken from outside the body by shockwaves.

  • Lower Pole Stones: Particularly effective for stones located in the bottom part of the kidney which are difficult to clear otherwise.

  • Failed Previous Treatments: When non-invasive methods like ESWL have failed to fragment the stone.

  • Patient Preference: For those seeking a higher "stone-free rate" with minimal scarring and a faster return to daily activities.

  • Mini-PCNL Access: A tiny incision (about 5 mm to 8 mm) is made in the flank area to allow for a thin telescope.

  • Micro-PCNL Access: Uses a specialized 1.5 mm needle—about the thickness of an injection needle—to enter the kidney without a traditional incision.

  • Laser Fragmentation: Utilization of high-power Holmium or Thulium Lasers to break stones into smaller pieces or fine dust.

  • Vortex Suction: A mechanism used in Mini-PCNL to automatically pull fragments out through the sheath using saline irrigation.

  • Dusting Technique: In Micro-PCNL, the laser turns the stone into a fine powder that washes out naturally through urine.

  • Anesthesia: Both procedures are performed under General Anesthesia to ensure the patient is completely asleep and still.

  • Imaging Guidance: Surgeons use Live X-ray (Fluoroscopy) and Ultrasound simultaneously to guide the needle or scope to the stone.

  • Nephroscopy: A thin Mini-Nephroscope or a tiny Micro-Lens camera is inserted directly into the kidney to visualize the stone.

  • Fragmentation: The laser fiber is passed through the scope or needle to precisely target and break the stone.

  • Stent Placement: In Mini-PCNL, a small internal JJ stent may be left for 1–2 weeks to ensure proper kidney drainage.

  • Fasting: Maintaining a "nil per oral" status for at least 8 hours before the procedure for anesthesia safety.

  • Medication Review: Suspending blood thinners several days in advance to minimize the risk of bleeding during the kidney puncture.

  • Antibiotic Prophylaxis: Receiving a dose of intravenous antibiotics just before the procedure to prevent urinary tract infections.

  • Hydration: Ensuring adequate fluid intake in the days leading up to the surgery to maintain good kidney function.

  • Clearance: Obtaining medical clearance, especially for patients with pre-existing heart or lung conditions.

  • NCCT KUB: A non-contrast CT scan to determine the exact size, location, and hardness (Hounsfield units) of the stone.

  • Urine Culture: To confirm the urine is sterile; surgery is postponed if an active infection is detected.

  • Coagulation Profile: Blood tests (PT/INR) to ensure the blood clots normally before making the kidney access.

  • Renal Function Test: Checking Creatinine and Urea levels to assess how well the kidneys are functioning.

  • ECG and Chest X-ray: Standard pre-anesthetic tests to ensure heart and lung fitness for general anesthesia.

  • Hospital Stay: Typically 24 hours for Mini-PCNL, while Micro-PCNL is often performed as a daycare (same-day) procedure.

  • Hydration Therapy: Drinking 3–4 litres of water daily is essential to flush out laser-dusted particles and fragments.

  • Physical Activity: Most patients return to light desk work within 3–4 days but should avoid heavy lifting for 2 weeks.

  • Urine Appearance: Expect light-pink or blood-tinged urine for 1–2 days as the kidney heals.

  • Stent Removal: If a JJ stent was placed, a minor follow-up procedure is required to remove it after 7–14 days.

  • High Stone-Free Rate: Provides a much higher chance of complete stone removal in a single session compared to ESWL.

  • Minimal Pain: Small access points lead to significantly less post-operative pain and a reduced need for painkillers.

  • Cosmetic Results: The incisions are so small (or non-existent in Micro-PCNL) that they often require no stitches and leave no visible scars.

  • Safety: Lower risk of bleeding and kidney damage compared to traditional, large-tract PCNL.

  • Fast Recovery: Allows for a quicker discharge from the hospital and a rapid return to a normal lifestyle.

Transurethral Resection of Prostate (TURP)

Transurethral Resection of the Prostate (TURP) is a surgical treatment used to treat urinary problems caused by an enlarged prostate (Benign Prostatic Hyperplasia or BPH). It is often called the "Gold Standard" because it is highly effective and requires no external incisions.

  • Moderate to Severe BPH Symptoms: When urinary frequency, urgency, or a weak stream significantly impact your quality of life.

  • Incomplete Bladder Emptying: If you consistently feel that your bladder is not empty after urinating, which can lead to infections.

  • Recurrent Urinary Tract Infections: When an enlarged prostate causes stagnant urine that leads to frequent UTIs.

  • Bladder Stones or Kidney Damage: When the obstruction is severe enough to cause secondary complications in the urinary system.

  • Failure of Medication: If alpha-blockers or 5-alpha reductase inhibitors are no longer providing sufficient relief.

  • Monopolar TURP: The traditional method using a wire loop and an electric current with glycine irrigation fluid.

  • Bipolar TURP: A modern advancement using saline irrigation, which significantly reduces the risk of "TURP Syndrome" and allows for safer treatment of larger prostates.

  • Resectoscope Access: A thin, lighted tube is inserted through the tip of the penis into the urethra, requiring no external cuts or stitches.

  • Wire Loop Resection: An electric current is passed through a loop to precisely "shave" away excess tissue blocking the urine flow.

  • Continuous Irrigation: Sterile fluid is pumped through the scope during surgery to wash away blood and tissue fragments.

  • Anesthesia: Performed under Spinal Anesthesia (numbing from the waist down) or General Anesthesia to ensure the patient is completely comfortable.

  • Insertion: The surgeon guides the resectoscope through the urethra until it reaches the prostate gland.

  • Tissue Removal: The obstructing lobes of the prostate are shaved into small chips using the electrified wire loop.

  • Fragment Flushing: The shaved tissue pieces are gathered and flushed out of the bladder at the conclusion of the surgery.

  • Catheterization: A three-way Foley catheter is inserted to allow for continuous bladder irrigation immediately following the procedure.

  • Medical Evaluation: Includes a Uroflowmetry test to measure urine speed and an ultrasound to determine the exact prostate size.

  • Medication Adjustment: You must stop blood thinners (like aspirin or warfarin) 5–7 days before surgery to prevent internal bleeding.

  • Fasting: Maintaining a "nil per oral" status for 6–8 hours before the procedure for anesthesia safety.

  • Antibiotic Prophylaxis: A preventative dose of antibiotics is given intravenously just before surgery to minimize infection risks.

  • PSA Testing: A blood test to screen for prostate-specific antigen levels prior to surgical intervention.

  • Urine Routine & Culture: To ensure there is no active infection before entering the urinary tract.

  • Prostate Ultrasound (TRUS): To map the dimensions of the prostate and plan the volume of tissue to be resected.

  • Cystoscopy: Occasionally performed beforehand to visualize the narrowness of the urethra and the shape of the prostate.

  • Blood Coagulation Profile: Testing PT/INR and Platelet counts to ensure safe surgical healing.

  • Basic Metabolic Panel: Checking kidney function (Creatinine) and electrolytes, especially important for managing irrigation fluid balance.

  • Hospital Stay: Most patients stay for 1 to 2 days until the urine is clear and the catheter can be safely removed.

  • Bladder Irrigation: While in the hospital, a sterile fluid "washes" the bladder through the catheter to prevent blood clots.

  • Hydration Therapy: Drinking at least 2–3 litres of water daily at home is essential to flush the healing surgical site.

  • Activity Restrictions: Avoid heavy lifting (over 5 kg) or vigorous exercise for 4–6 weeks to prevent secondary bleeding.

  • Sexual Activity: Avoid sexual intercourse for 4 weeks to allow the internal area to seal completely.

  • Urination Changes: It is normal to feel a temporary burning sensation or urgency for a few weeks as the raw prostatic bed heals.

  • Immediate Symptom Relief: Most patients experience a significantly stronger urine stream and better bladder emptying almost immediately after recovery.

  • No External Scarring: Because the surgery is entirely internal, there are no visible scars or wound care requirements on the skin.

  • Long-Term Durability: TURP results typically last for 15 years or more, often providing a permanent solution for BPH symptoms.

  • Bipolar Safety: Modern Bipolar technology allows surgeons to treat patients with heart conditions or larger prostates more safely than ever before.

  • Diagnostic Benefit: The shaved tissue is always sent for biopsy to confirm the absence of any hidden cancerous cells.

Laser Prostate Surgery (HoLEP / ThuLEP)

Laser prostate surgery, specifically HoLEP (Holmium Laser Enucleation of the Prostate) and ThuLEP (Thulium Laser Enucleation of the Prostate), is a modern, bloodless alternative to traditional TURP. Instead of shaving the prostate in small pieces, the laser "peels" the obstructing tissue away as a whole, making it highly effective for even the largest prostate glands.

  • Very Large Prostate: Especially effective for prostates over 80–100 grams that are too large for standard TURP.

  • High Risk of Bleeding: Ideal for patients who cannot safely stop blood thinners, due to the laser's superior vessel-sealing properties.

  • Severe Urinary Retention: When a patient is completely unable to pass urine and requires a catheter.

  • Recurrent Prostate Issues: For those who have had previous prostate surgery and are experiencing regrowth of obstructing tissue.

  • Desire for Fast Recovery: For patients who want a shorter hospital stay and quicker removal of the urinary catheter.

  • HoLEP (Holmium Laser): Uses a "pulsed" laser beam, which is excellent for "blunt dissection" (peeling) the prostate lobes away from the capsule.

  • ThuLEP (Thulium Laser): Uses a "continuous wave" laser that provides smoother cutting and even better blood vessel sealing (hemostasis).

  • Enucleation Technique: The surgeon uses the laser to peel away the entire obstructing lobe, similar to removing the flesh of an orange from its peel.

  • Morcellation: A specialized "blender-like" device is used to grind the large peeled-off lobes inside the bladder and vacuum them out.

  • Transurethral Access: The entire procedure is performed through the urethra using a laser-integrated scope, requiring no external incisions.

  • Anesthesia: Performed under General Anesthesia or Spinal Anesthesia to ensure the patient is completely still and pain-free.

  • Laser Dissection: The laser fiber is used to cut along the "capsule" of the prostate, separating the obstructing tissue from the healthy outer shell.

  • Simultaneous Cauterization: As the laser cuts, it seals every blood vessel it touches, resulting in minimal to no blood loss.

  • Intra-vesical Morcellation: Once the tissue is moved into the bladder, the morcellator sucks up and removes the fragments in a matter of minutes.

  • Final Inspection: The surgeon verifies that the bladder is clear of debris and that there is no active bleeding before finishing.

  • Catheter Placement: A Foley catheter is inserted at the end of the procedure, which is typically removed within 24 hours.

  • Imaging & Size Check: An Ultrasound (TRUS) or MRI is performed to measure the exact prostate volume and map the anatomy.

  • Urine Culture: A sterile urine sample is mandatory; any active infection must be treated with antibiotics before the laser is used.

  • Medication Audit: Patients on Aspirin or Warfarin usually stop these 5–7 days prior, though some laser cases can proceed while on thinners if necessary.

  • Fasting: Maintaining a "nil per oral" (NPO) status for 6–8 hours before the operation for anesthesia safety.

  • Medical Clearance: Ensuring heart and lung fitness for the procedure, especially since it is often performed on older patients.

  • Uroflowmetry: To measure the baseline speed and force of the urine stream before surgery.

  • Post-Void Residual (PVR) Volume: An ultrasound test to see how much urine remains in the bladder after peeing.

  • PSA Blood Test: To screen for prostate-specific antigen levels and rule out other underlying conditions.

  • Basic Metabolic Panel: Checking kidney function (Creatinine) and electrolytes to ensure the body can handle the procedure.

  • Coagulation Profile: Testing the blood's ability to clot (PT/INR) to ensure a safe, bloodless surgical outcome.

  • Hospital Stay: Usually a 24-hour stay; many patients are discharged the very next morning after the catheter is removed.

  • Immediate Results: Most patients notice an immediate, forceful urine stream once the initial catheter is taken out.

  • Hydration Therapy: Drinking 2.5–3 litres of water daily for the first week is essential to flush out any minor laser-charred debris.

  • Activity Rules: You can usually return to desk work within 3–5 days, but avoid heavy lifting (over 10 kg) for at least 2 weeks.

  • Retrograde Ejaculation: This is common (90% of cases), where semen travels into the bladder during orgasm; it is harmless but affects fertility.

  • Temporary Urgency: A frequent "urge" to pee or minor leaking may occur for the first few weeks as the internal capsule heals.

  • Superior Hemostasis: The laser's ability to seal vessels as it cuts makes this the safest option for patients with bleeding disorders or heart issues.

  • Complete Tissue Removal: By following the natural "capsule," laser surgery removes more obstructing tissue than TURP, reducing the risk of regrowth.

  • Shorter Catheter Time: Most patients are catheter-free within 24 hours, significantly reducing the risk of catheter-associated infections.

  • Treatment of Any Size: Unlike other minimally invasive methods, HoLEP and ThuLEP can treat prostates of virtually any size (even over 200 grams).

  • Minimal Side Effects: Lower risk of "TURP Syndrome" and other fluid-balance complications due to the use of saline irrigation.

Transurethral Incision of the Prostate (TUIP)

Transurethral Incision of the Prostate (TUIP) is a specialized surgical treatment for men with urinary symptoms caused by a moderately enlarged prostate (usually less than 30 grams) or a narrowing of the bladder neck. Unlike TURP or Laser surgery, no tissue is removed; instead, the "tight" area is widened to allow for better flow.

  • Small to Moderately Enlarged Prostate: Specifically indicated for prostates under 30 grams where the blockage is at the bladder neck.

  • Bladder Neck Obstruction: When the primary cause of urinary symptoms is a narrowing of the opening between the bladder and the urethra.

  • Preservation of Fertility: For men who wish to minimize the risk of retrograde ejaculation (dry orgasm) often associated with other prostate surgeries.

  • High-Risk Patients: For those who may not tolerate longer surgical procedures, as TUIP is significantly faster than TURP.

  • Failure of Medical Management: When medications like alpha-blockers are no longer providing sufficient relief for urinary flow.

  • Cystoscope Access: A thin, lighted scope is inserted through the tip of the penis into the urethra, requiring no external incisions.

  • Electric Knife Incision: The use of a specialized wire or knife to make one or two small, deep cuts (grooves) in the bladder neck.

  • Laser Incision: A modern alternative using a laser fiber to precisely cut the prostate and bladder neck tissue.

  • Channel Widening: Unlike "shaving" tissue, the mechanism relies on making a structural cut that allows the bladder neck to "spring open."

  • Minimal Tissue Trauma: A technique that avoids the removal of prostate mass, leading to significantly less internal wounding.

  • Anesthesia: Performed under Spinal Anesthesia (numbing from the waist down) or General Anesthesia for patient comfort.

  • Insertion: The surgeon guides the cystoscope through the urethra until the junction of the bladder and prostate is visualized.

  • Creating Grooves: The surgeon makes precise incisions through the prostate and the muscle of the bladder neck.

  • Widening: By cutting the tight muscle ring, the urethral channel is widened, immediately reducing the resistance to urine flow.

  • Catheterization: A Foley catheter is placed at the end of the 20–30 minute procedure to assist with initial healing and drainage.

  • Prostate Sizing: A Transrectal Ultrasound (TRUS) is essential to confirm the prostate is small enough (under 30g) for this technique.

  • Urodynamic Study: A test to confirm that the blockage is at the bladder neck and not caused by a weak bladder muscle.

  • Medication Review: You must stop blood thinners (like Aspirin or Warfarin) 5–7 days prior to surgery to prevent bleeding.

  • Fasting: Maintaining a "nil per oral" status for 6–8 hours before the procedure for anesthesia safety.

  • Antibiotic Prophylaxis: A dose of antibiotics is given intravenously just before surgery to prevent urinary tract infections.

  • Uroflowmetry: To measure the speed and force of the urine stream to establish a baseline for post-operative comparison.

  • Post-Void Residual (PVR): An ultrasound to measure how much urine is left in the bladder after peeing.

  • Urine Culture: To ensure the urinary tract is sterile before the procedure; any infection must be treated first.

  • Basic Metabolic Panel: Checking kidney function (Creatinine) and electrolytes to ensure surgical fitness.

  • Coagulation Profile: Testing the blood's ability to clot (PT/INR) to ensure safe healing of the internal incisions.

  • Hospital Stay: Often performed as a Daycare (Same-Day) procedure, or a maximum stay of 24 hours.

  • Catheter Removal: The Foley catheter is typically removed within 24 to 48 hours after the surgery.

  • Hydration Therapy: Drinking 2–3 litres of water daily is essential to flush the urinary tract as the "grooves" heal.

  • Activity Restrictions: Most patients can return to light work within 2–3 days but should avoid heavy lifting for 2 weeks.

  • Urinary Sensations: It is normal to feel a temporary urgency or stinging for the first few days post-surgery.

  • Fertility Preservation: Most men maintain normal ejaculation after TUIP, as the risk of retrograde ejaculation is much lower than with TURP.

  • Rapid Recovery: Due to the minimal tissue trauma, patients experience a much faster return to normal activities than with traditional surgery.

  • High Safety Profile: With very little bleeding and a short operative time, TUIP is an excellent option for patients with minor health concerns.

  • Functional Success: Effectively treats the root cause of bladder neck obstruction, providing a forceful urine stream immediately.

  • No External Scars: The procedure is entirely internal, leaving no visible marks and requiring no wound care on the skin.

  • Preservation of Sexual Health: Offers the best chance of maintaining normal sexual function and fertility compared to other surgical BPH treatments.

Radical Prostatectomy (Open/Laparoscopic/Robotic)

Radical Prostatectomy is the surgical removal of the entire prostate gland and surrounding tissues, typically performed to treat Prostate Cancer. Unlike treatments for an enlarged prostate (BPH) which only remove the "core," this treatment removes the entire organ to ensure the cancer is fully eliminated.

  • Localized Prostate Cancer: When imaging confirms the cancer is confined within the prostate capsule (Stages T1 or T2).

  • Aggressive Disease: For patients with a higher Gleason Score who require definitive surgical removal rather than "active surveillance."

  • Long Life Expectancy: Typically recommended for patients expected to live 10+ years, where surgical removal offers the best long-term cure rate.

  • Failure of Radiation: As a "salvage" treatment if the cancer returns after previous radiation therapy.

  • Patient Preference: For individuals who prefer the psychological certainty of having the cancerous organ physically removed.

  • Robotic-Assisted (Da Vinci): The modern gold standard. The surgeon sits at a console controlling robotic arms with 3D magnification and 360-degree "wristed" instruments for extreme precision.

  • Laparoscopic Surgery: A minimally invasive approach using 5–6 "keyhole" incisions, a camera, and long instruments to operate while viewing a 2D screen.

  • Open Surgery (Retropubic): The traditional method involving a single 4–5 inch incision in the lower abdomen to remove the gland.

  • Nerve-Sparing Technique: A meticulous process where the surgeon peels the delicate "neurovascular bundles" away from the prostate to preserve sexual function.

  • Vesicourethral Anastomosis: The reconstructive step where the bladder is stitched directly back to the urethra to restore the urinary path after the gland is removed.

  • Anesthesia: Performed under General Anesthesia to ensure the patient is completely asleep and the abdominal muscles are relaxed.

  • Dissection: The surgeon carefully separates the prostate from the bladder above it and the urethra below it.

  • Lymph Node Removal: Depending on the cancer's aggressiveness, nearby pelvic lymph nodes are often removed to check for microscopic spread.

  • Gland Extraction: The entire prostate and the attached seminal vesicles are removed as a single unit.

  • Catheterization: A Foley catheter is inserted through the penis into the bladder to act as a "splint" while the new connection (anastomosis) heals.

  • Drain Placement: A small suction tube may be left in the abdomen for 24–48 hours to remove excess surgical fluid.

  • Cancer Staging: Includes a Multiparametric MRI (mpMRI) and often a PSMA PET-CT scan to ensure the cancer has not spread.

  • Biopsy Review: The surgical team reviews the Gleason Score and genomic markers to plan the extent of the surgery.

  • Pelvic Floor Training: Patients are taught Kegel exercises weeks before surgery to strengthen the muscles responsible for urinary control.

  • Medication Audit: Patients must stop blood thinners (like Aspirin or Warfarin) 7–10 days prior to the operation.

  • Fasting: Maintaining a "nil per oral" status for 8 hours before the procedure for anesthesia safety.

  • PSA Blood Test: To establish the final pre-operative baseline for monitoring future "undetectable" levels.

  • EKG and Chest X-ray: Standard tests to ensure heart and lung fitness for a multi-hour surgical procedure.

  • Basic Metabolic Panel: Checking kidney function (Creatinine) and electrolytes to manage IV fluids during surgery.

  • Coagulation Profile: Testing PT/INR and Platelet counts to ensure safe surgical healing and minimal blood loss.

  • Complete Blood Count (CBC): To check baseline hemoglobin levels in case a blood transfusion is required (rare in robotic cases).

  • Hospital Stay: Usually 1–2 days for Robotic/Laparoscopic surgery, or 3–4 days for the Open approach.

  • Catheter Management: The Foley catheter must remain in place for 7 to 14 days to allow the bladder-urethra connection to heal water-tight.

  • Trial of Void: After 1–2 weeks, the catheter is removed in the clinic to ensure the patient can urinate independently.

  • Activity Restrictions: No heavy lifting (over 5kg) or driving for 4 weeks; early walking is encouraged to prevent blood clots.

  • Urinary Incontinence: Most patients experience leaking initially; this typically improves over 3–6 months with consistent pelvic floor exercises.

  • Erectile Dysfunction (ED): It can take 6–18 months for erections to return; doctors often start "Penile Rehabilitation" medication shortly after surgery.

  • Definitive Cure: Offers the highest probability of completely eliminating localized prostate cancer in a single treatment.

  • Pathological Certainty: Removing the gland allows for a total biopsy, giving the most accurate information on the cancer's stage and grade.

  • Robotic Precision: The 3D-high-definition view in 2026 allows surgeons to see nerves and vessels that are nearly invisible to the naked eye.

  • Predictable Monitoring: Post-surgery, the PSA level should drop to "undetectable," making it very easy to monitor for any future recurrence.

  • Limb-Sparing Mindset: Modern techniques focus heavily on "quality of life" preservation, aiming for the "Trifecta" of cancer control, continence, and potency.

Partial Nephrectomy (Kidney-Saving Surgery)

Partial Nephrectomy, also known as "Kidney-Sparing Surgery," is a complex procedure where only the diseased part of the kidney (usually a tumor) is removed, leaving the healthy, functioning kidney tissue intact. This is the preferred treatment for smaller kidney tumors to preserve as much renal function as possible.

  • Small Renal Masses: Typically the first choice for tumors less than 4 cm (Stage T1a) and many tumors up to 7 cm (Stage T1b).

  • Solitary Kidney: When a patient only has one functioning kidney, making it critical to avoid a total removal.

  • Bilateral Kidney Tumors: When tumors are present in both kidneys, requiring a sparing approach on one or both sides.

  • Pre-existing Kidney Disease: For patients with diabetes or hypertension who are at higher risk for future chronic kidney disease.

  • Genetic Predisposition: For patients with conditions like Von Hippel-Lindau (VHL) syndrome who may develop multiple tumors over their lifetime.

  • Robotic-Assisted (Da Vinci): The modern standard for precision. It allows the surgeon to perform complex suturing within the tight "ischemia" time window using 3D magnification.

  • Laparoscopic Surgery: A minimally invasive approach using small incisions and specialized instruments to remove the tumor and repair the kidney.

  • Open Surgery: Often reserved for very large or centrally located tumors where the surgeon needs direct physical access to the kidney.

  • Nerve and Vessel Sparing: A technique focusing on identifying the specific arterial branches feeding the tumor to avoid clamping the entire renal blood supply.

  • Renorrhaphy (Repair): The reconstructive phase where the "hole" left in the kidney is stitched closed using specialized sutures and hemostatic agents.

  • Anesthesia: Performed under General Anesthesia to ensure total patient comfort and muscle relaxation.

  • The "Clamping" Phase: To prevent heavy bleeding, the surgeon temporarily clamps the Renal Artery. This must usually be completed in under 20–30 minutes to protect kidney health.

  • Tumor Excision: The surgeon cuts out the tumor along with a small "margin" of healthy tissue to ensure no cancer cells remain.

  • Hemostasis: Specialized "bolsters" or glues are often applied to the raw surface of the kidney to stop bleeding instantly.

  • Unclamping: The artery clamp is removed, and the surgeon verifies that the kidney regains its pink color and shows no signs of active bleeding.

  • Drain Placement: A small tube is left in the side for 24–48 hours to monitor for any internal fluid or blood collection.

  • 3D Imaging: A high-resolution CT Scan or MRI with contrast is mandatory to map the "Renal Nephrometry Score" and tumor depth.

  • Kidney Function Test: A DTPA Scan or serum creatinine test is performed to establish a baseline for how well both kidneys are working.

  • Blood Prep: "Cross-matching" for blood units is done in advance due to the highly vascular nature of the kidney.

  • Medication Audit: You must stop all blood thinners (Aspirin, Warfarin, etc.) 7–10 days prior to the operation.

  • Fasting: Maintaining a "nil per oral" status for 8 hours before the procedure for anesthesia safety.

  • Complete Blood Count (CBC): To check baseline hemoglobin levels and ensure the body is ready for surgery.

  • Coagulation Profile: Testing PT/INR and Platelet counts to ensure the kidney repair will clot effectively.

  • Chest X-ray and EKG: Standard pre-operative checks to ensure heart and lung fitness for general anesthesia.

  • Urinalysis: To rule out any existing urinary tract infections before the procedure.

  • Electrolyte Panel: Checking sodium, potassium, and calcium levels to ensure the body’s chemistry is balanced.

  • Hospital Stay: Usually 2–3 days for Robotic/Laparoscopic surgery and 4–5 days for the Open approach.

  • Catheterization: A Foley catheter is placed in the bladder for 1–2 days to monitor urine output and filtration.

  • Activity Restrictions: No heavy lifting (over 5kg) or strenuous exercise for 6 weeks to prevent the repair from bleeding.

  • Hydration Therapy: Drinking 2–2.5 litres of water daily is recommended to keep the kidneys working at a steady, healthy pace.

  • Urine Leak Risk: If the repair isn't water-tight, a temporary JJ Stent may be placed to allow the kidney to heal.

  • Follow-Up Imaging: A CT scan is typically repeated at 3 or 6 months to monitor the surgical site and ensure no recurrence.

  • Preservation of Function: By saving the healthy part of the kidney, patients have a much lower risk of requiring dialysis in the future.

  • Oncological Equivalent: Modern studies show that for appropriately selected tumors, a partial removal is just as effective as a total removal for cancer control.

  • Robotic Precision: 2026 robotic technology allows for "ultra-selective clamping," where only the tumor's blood supply is stopped, leaving the rest of the kidney "warm."

  • Faster Recovery: Minimally invasive techniques lead to less pain, smaller scars, and a quicker return to normal life compared to traditional surgery.

  • Lower Cardiovascular Risk: Maintaining two functioning kidneys is linked to better long-term heart health and blood pressure control.

Cystoscopy
Cystoscopy

Cystoscopy and Hypospadias Repair are fundamental urological procedures used to diagnose and correct anatomical issues within the urinary tract. While Cystoscopy is a diagnostic tool that provides a direct view of the bladder and urethra, Hypospadias Repair is a delicate reconstructive surgery. In many clinical cases, especially in pediatric urology, these procedures are performed together to ensure that the internal urinary anatomy is healthy before external reconstruction begins.

  • Congenital Misalignment: When a newborn is identified with a urethral opening on the underside of the penis rather than the tip.

  • Persistent Curvature: A condition known as "chordee," where the penis curves downward, often accompanying hypospadias.

  • Unexplained Hematuria: The presence of blood in the urine that requires internal visualization via cystoscopy.

  • Recurrent Urinary Tract Infections (UTIs): To rule out structural blockages or "valves" within the urethra.

  • Difficulties with Urination: A weak or misdirected urinary stream in children or adults.

  • Pre-Surgical Mapping: Performing a cystoscopy to ensure the proximal urethra is clear before starting a complex reconstruction.

  • Proximal Hypospadias: Severe cases where the urethral opening is located near the scrotum or perineum.

  • Redo (Revision) Surgery: Patients who have had a previous unsuccessful repair and require specialized tissue grafts.

  • Prostatic Utricle: An internal pocket sometimes found in children with hypospadias that must be identified via cystoscopy.

  • Intersex/DSD Conditions: Cases where urological reconstruction is part of a broader multidisciplinary care plan.

  • Adult Hypospadias: Complex repairs in adults which may involve strictures or scar tissue from childhood.

  • Cystoscopy: A thin, lighted tube (cystoscope) is gently inserted through the urethra. The surgeon uses high-definition monitors to inspect the lining of the bladder and the urethral path.

  • TIP Repair (Tubularized Incised Plate): The most common corrective technique where the existing urethral plate is used to create a new, functional tube.

  • Grafting: In severe cases, tissue may be taken from the foreskin or the inside of the cheek (buccal mucosa) to reconstruct the urinary channel.

  • Chordee Correction: If the penis is curved, the surgeon releases the fibrous tissue causing the bend to ensure a straight functional result.

  • Stenting: A small, flexible tube (stent) is often placed in the new urethra for 5 to 10 days to ensure it remains open during the initial healing phase.

  • Anesthesia: Children undergo general anesthesia for both procedures to ensure comfort and precision.

  • Robotic-Assisted MicrosurgeryUsing robotic systems for proximal repairs to achieve ultra-precise suturing of the delicate urethral tissues, reducing the risk of fistulas.

  • 3D-Printed Urethral ScaffoldsExperimental but progressing technology where bio-compatible scaffolds are used to help grow a new urethra in complex revision cases.

  • Ultra-Thin Fiber-Optic CystoscopesDigital scopes that are significantly thinner and more flexible than traditional models, minimizing tissue trauma during diagnostic exams.

  • Tissue EngineeringUtilizing lab-grown epithelial cells to create custom grafts, potentially eliminating the need to harvest tissue from the mouth.

  • Laser-Assisted Tissue BondingUsing specialized lasers to "weld" tissue edges together with high precision, creating a more watertight seal than traditional stitches.

  • Virtual Reality (VR) Surgical PlanningSurgeons use 3D reconstructions from scans to "rehearse" complex urological repairs before entering the operating room.

  • Optimal Timing: For children, the procedure is ideally scheduled between 6 and 18 months of age for faster healing and minimal psychological impact.

  • NPO Guidelines: Strict fasting instructions prior to surgery to ensure the safety of general anesthesia.

  • Hygiene and Skin Care: Ensuring the diaper area is free of rashes or infections before the scheduled surgery date.

  • Medication Review: Discussing any supplements or medications that could affect blood clotting.

  • Psychological Support: Providing "play therapy" or age-appropriate explanations for older children to reduce anxiety.

  • Retrograde Urethrogram: An X-ray test sometimes used alongside cystoscopy to map the urethral path.

  • Flow Rate Testing: Post-operative measurements to ensure the new urinary stream is strong and unobstructed.

  • Stent Management: Monitoring the drainage of the temporary stent to ensure proper kidney and bladder function.

  • Fistula Screening: Regular check-ups to ensure there are no unintended openings or "leaks" in the newly constructed channel.

  • Cosmetic Assessment: Evaluating the symmetry and appearance of the glans (tip) and the straightness of the penis.

  • Restored Functionality: Corrects the urinary stream, allowing for a normal standing position during urination and ensuring future reproductive health.

  • High Success Rates: Modern "TIP" repairs have a very high success rate with minimal complications for distal cases.

  • Comprehensive Diagnosis: The use of cystoscopy ensures that no internal anatomical surprises are missed before the external work begins.

  • Psychological Well-being: Early correction prevents the self-esteem issues that can arise from anatomical differences as a child grows.

  • Synergistic Care: Combining diagnosis and repair into a single session reduces the need for multiple anesthetic exposures.

  • Most patients go home the same day or after a single night of observation.

  • Double-diapering techniques are often used to protect the stent and keep the surgical site clean.

  • Pain management typically involves a combination of local nerve blocks administered during surgery and oral medications at home.

  • Baths are usually restricted for the first few days, though sponge baths are encouraged to maintain hygiene.

  • A follow-up visit is scheduled within the first 10 days to remove the stent and assess the early healing of the new urethra.

  • A normal, functional urinary stream directed from the tip of the penis.

  • A straight anatomical result that supports healthy physical and sexual development.

  • Significant reduction in the risk of long-term urological complications like strictures or infections.

  • Confidence for the child as they reach developmental milestones like potty training.

  • The peace of mind for parents knowing a complex congenital issue has been permanently resolved.

Kidney Transplant Surgery

Kidney transplant surgery is a life-saving procedure where a healthy kidney from a donor (living or deceased) is placed into a patient with end-stage renal disease (ESRD). It is generally the preferred treatment over lifelong dialysis, offering a significantly better quality of life and higher long-term survival rates. This procedure restores the body's ability to filter waste and maintain fluid balance naturally.

  • End-Stage Renal Disease (ESRD): When your kidneys have lost approximately 90% of their function due to chronic conditions.

  • Diabetes Mellitus: One of the leading causes of kidney failure that can be effectively managed through transplantation.

  • Chronic High Blood Pressure: Persistent hypertension that has caused irreversible damage to the kidney's filtering units (nephrons).

  • Polycystic Kidney Disease (PKD): A genetic disorder causing numerous cysts to grow in the kidneys, eventually leading to failure.

  • Preemptive Transplant: For patients whose kidney function is declining but who have not yet started dialysis, as this often leads to the best long-term outcomes.

  • Anesthesia: The operation is performed under general anesthesia and typically takes between 3 to 4 hours.

  • Placement: The donor kidney is placed in the lower abdomen (usually the right or left groin area).

  • Native Kidneys: Your original kidneys are generally left in place unless they are causing specific complications like chronic infection or severe high blood pressure.

  • Vascular Connections: The donor kidney's artery and vein are surgically attached to your existing iliac blood vessels in the lower abdomen to establish blood flow.

  • Ureteral Connection: The donor's ureter (the tube that carries urine) is connected directly to your bladder to allow for natural voiding.

  • Monitoring: Once blood starts flowing, the new kidney often begins producing urine immediately, though it can sometimes take several days to fully "wake up."

  • Transplant Evaluation: A comprehensive series of medical, surgical, and psychological tests to ensure you are a suitable candidate for the procedure.

  • Compatibility Testing: Blood typing (A, B, AB, or O) and tissue typing (HLA matching) to find the best possible donor match.

  • Crossmatch Test: A final blood test mixed with the donor's cells to ensure your immune system will not immediately attack the new organ.

  • Dental and Cancer Screenings: Ensuring there are no active infections or undiagnosed malignancies that could be exacerbated by anti-rejection medication.

  • Fasting: Following strict "nothing by mouth" instructions for 8 hours prior to your scheduled surgery.

  • Echocardiogram: A detailed heart ultrasound to ensure your cardiovascular system can handle the surgery.

  • Chest X-ray: To rule out any active lung infections or fluid buildup prior to anesthesia.

  • Panel Reactive Antibody (PRA) Test: Measures the level of antibodies in your blood to determine how difficult it will be to find a compatible match.

  • CT Scan of the Pelvis: To evaluate the blood vessels in the lower abdomen where the new kidney will be attached.

  • ECG: A routine heart check to confirm cardiac stability for the duration of the procedure.

  • Hospital Stay: Typically lasts 3 to 7 days for the recipient to monitor organ function and manage post-operative pain.

  • Lifelong Medication: You must take immunosuppressant (anti-rejection) drugs daily for the rest of your life to prevent your immune system from attacking the new kidney.

  • Physical Restrictions: Avoid lifting objects heavier than 4.5 kg (10 lbs) for at least 6 to 8 weeks to allow the abdominal wall to heal.

  • Driving and Work: Driving is usually restricted for 2 to 6 weeks, and most people can return to professional work within 8 to 12 weeks.

  • Dietary Adjustments: While restrictions are fewer than on dialysis, you must avoid raw/undercooked foods and grapefruit/grapefruit juice, which can dangerously interfere with anti-rejection medications.

  • Eliminates Dialysis: A successful transplant removes the need for time-consuming dialysis treatments, providing true freedom and independence.

  • Higher Energy Levels: Restoring natural kidney function helps correct anemia and remove toxins, leading to significantly increased vitality.

  • Fewer Dietary Restrictions: Patients can enjoy a much broader range of foods and fluids compared to the strict limitations of a renal diet.

  • Improved Long-term Survival: Statistics consistently show that transplant recipients live longer than patients who remain on long-term dialysis.

  • Cost-Effective Care: While the initial surgery is intensive, the long-term cost of maintaining a healthy transplant is much lower than the ongoing cost of dialysis.

Slip Disc (Lumbar Discectomy)

Lumbar Discectomy is a surgical procedure to remove the fragmented or protruding portion of a herniated disc (slip disc) that is compressing a spinal nerve. It is most commonly performed in the lower back (lumbar spine) to relieve radiating leg pain, known as sciatica, by decompressing the affected nerve root.

  • Failed Conservative Treatment: When 6–12 weeks of physical therapy, NSAIDs, or steroid injections fail to provide relief.

  • Radiculopathy (Sciatica): Severe, radiating pain, numbness, or weakness that travels down the leg and into the foot.

  • Neurological Deficit: Progressive muscle weakness or a "foot drop" caused by sustained nerve compression.

  • Cauda Equina Syndrome: An emergency condition involving loss of bowel or bladder control or "saddle anesthesia" (numbness in the groin).

  • Significant Functional Impairment: When back and leg pain prevents the performance of basic daily activities or work.

  • Microdiscectomy (Gold Standard): Using a high-powered operating microscope to minimize the incision size and improve visualization of the nerve.

  • Endoscopic Discectomy: An ultra-minimally invasive technique using a tiny camera and specialized tools inserted through a small tube.

  • Laminotomy/Laminectomy: Removing a small portion of the vertebral bone (lamina) to create a window to access the spinal canal.

  • Tubular Retractor Discectomy: Using a series of dilating tubes to part the muscles rather than cutting them, reducing post-operative soreness.

  • Sequestrectomy: Removing only the free-floating disc fragment without entering the main disc space, which may reduce the risk of future collapse.

  • Positioning: The patient is placed face down on a specialized surgical frame that opens the spaces between the vertebrae.

  • Incision: A small 2–3 cm midline incision is made in the lower back directly over the level of the herniation (most commonly L4-L5 or L5-S1).

  • Exposure: The surgeon moves the spinal muscles aside and removes a small amount of ligament and bone to view the spinal canal.

  • Nerve Protection: The compressed nerve root is gently retracted to one side to expose the herniated disc material underneath.

  • Fragment Removal: The surgeon identifies the "jelly-like" protrusion and removes it. The healthy portion of the disc is left intact to serve as a shock absorber.

  • Closure: The muscles return to their original position, and the skin is closed with dissolvable stitches and surgical glue.

  • Confirmation of the herniation level via MRI to ensure the surgical site matches the patient's clinical symptoms.

  • Smoking cessation is mandatory for several weeks prior, as nicotine restricts blood flow to the spine and significantly hinders healing.

  • Fasting (NPO) for 8–12 hours before the procedure to ensure safety during general anesthesia.

  • Discussion of the "BLT" (Bending, Lifting, Twisting) restrictions that will be required immediately following the surgery.

  • Lumbar MRI: The primary diagnostic tool used to visualize the disc herniation and its relationship to the nerve roots.

  • X-ray (Flexion/Extension): Performed to ensure there is no underlying spinal instability or "slipped" vertebrae (spondylolisthesis).

  • Electromyography (EMG): Occasionally used to confirm which specific nerve is being damaged and to assess the severity of the nerve injury.

  • Blood Panels: Routine screens to ensure the patient is fit for anesthesia and has no signs of active infection.

  • Most procedures are performed as same-day (outpatient) surgeries or require only a single overnight stay.

  • Patients are encouraged to stand and walk within 4 hours of waking up to promote circulation and prevent stiffness.

  • The "BLT" Rule: For the first 6 weeks, you must strictly avoid Bending at the waist, Lifting anything over 2kg, and Twisting the spine.

  • Incisions must be kept dry for the first 3–5 days; stitches are usually dissolvable and do not require removal.

  • Physical therapy typically begins around the 6-week mark to strengthen the core and multifidus muscles that support the spine.

  • Over 90% of patients report immediate and dramatic relief from radiating leg pain (sciatica).

  • Minimally invasive techniques allow for smaller scars, less muscle damage, and a faster return to daily life.

  • Prevents permanent nerve damage by removing the source of chronic compression and inflammation.

  • Restores the ability to perform physical activities, work, and exercise without the limitation of debilitating leg pain.

Cervical Discectomy
Cervical Discectomy

Cervical Discectomy is a surgical procedure to remove a herniated or degenerative disc in the neck (cervical spine). It is performed to relieve pressure on the spinal cord or nerve roots, which typically causes neck pain, radiating arm pain (brachialgia), or weakness. By removing the damaged disc, the surgeon creates more space for the neural structures to function properly.

  • Radiculopathy: Persistent arm pain, numbness, or "electric shock" sensations that have not improved with 6–12 weeks of conservative therapy.

  • Cervical Myelopathy: Urgent signs of spinal cord compression, such as clumsiness in the hands, loss of fine motor skills, or difficulty walking/balance issues.

  • Failed Conservative Care: When physical therapy, activity modification, and anti-inflammatory medications fail to provide adequate relief.

  • Progressive Weakness: Measurable loss of strength in the arms, shoulders, or grip due to sustained nerve compression.

  • Disc Degeneration: Severe wear and tear that leads to spinal instability or significant narrowing of the spinal canal (stenosis).

  • Anterior Cervical Discectomy and Fusion (ACDF): The most common method, reaching the disc from the front of the neck and fusing the vertebrae together for stability.

  • Cervical Disc Replacement (Arthroplasty): Inserting a mechanical artificial disc to maintain neck motion and potentially protect the surrounding discs from extra wear.

  • Posterior Cervical Discectomy: Approaching the disc from the back of the neck, typically used for specific types of "lateral" herniations that do not require a fusion.

  • Minimally Invasive Discectomy: Using specialized retractors and microscopes to minimize tissue damage and speed up recovery time.

  • Hybrid Surgery: A combination of fusion at one level and disc replacement at another for multi-level cervical disease.

  • Approach: For the common anterior (front) approach, a 2–3 cm horizontal incision is made in a skin fold on the front of the neck.

  • Pathway: The surgeon gently moves the windpipe (trachea) and esophagus to the side to gain a direct view of the front of the spine.

  • Discectomy: The entire damaged disc is removed, and the surgeon uses a microscope to ensure all bone spurs or fragments are cleared from the nerves.

  • Stabilization (ACDF): A bone graft or synthetic cage is placed into the empty disc space. A small titanium plate and screws are usually attached to hold the bones steady.

  • Stabilization (Replacement): A specialized metal and plastic joint is secured into the space to allow for continued flexion, extension, and rotation.

  • Closure: The internal tissues return to their natural positions, and the skin is closed with dissolvable sutures or surgical glue.

  • Confirmation of the specific disc level (most commonly C5-C6 or C6-C7) using high-resolution MRI and X-ray imaging.

  • Smoking cessation is mandatory for 4–6 weeks prior to surgery; nicotine significantly prevents the bone from fusing and increases the risk of complications.

  • Fasting (NPO) for at least 8 hours prior to the procedure to ensure safety under general anesthesia.

  • Pre-operative screening to ensure the patient can safely tolerate the retraction of the esophagus and neck tissues.

  • Cervical MRI: The gold standard for identifying disc herniations and the degree of spinal cord or nerve root compression.

  • X-rays (Static and Dynamic): Used to assess overall spinal alignment and check for any abnormal movement (instability) between vertebrae.

  • CT Scan: Sometimes required to better visualize "hard" bone spurs (osteophytes) that may be contributing to the compression.

  • Electromyography (EMG): Performed to confirm that the arm symptoms are originating from the neck and not from other sites like the elbow or wrist.

  • Many patients undergo the procedure as a same-day surgery or require only a single overnight stay for observation.

  • Depending on the surgeon’s preference and the complexity of the case, a soft or hard neck brace may be worn for 2 to 6 weeks.

  • Walking is encouraged immediately after surgery; however, lifting is strictly limited to less than 2–3 kg for the first 6 weeks.

  • Temporary hoarseness or a "lump in the throat" sensation when swallowing is common and usually fades within 2–4 weeks.

  • Driving is typically restricted for 2 weeks or until the patient can comfortably turn their head to check blind spots without pain.

  • Extremely high success rates (over 90–95%) for the permanent relief of radiating arm pain and "electric shock" sensations.

  • Prevents the progression of permanent spinal cord damage and neurological deficits in patients with myelopathy.

  • Restores the ability to perform daily tasks, such as writing, buttoning clothes, and walking, by decompressing the neural pathways.

  • Provides significant stabilization to the neck, reducing the chronic "deep" ache associated with degenerative disc disease.

Spinal Decompression Surgery

Spinal Decompression Surgery is a general term for various procedures performed to relieve pressure on the spinal cord or nerve roots. It is most commonly used to treat Spinal Stenosis (narrowing of the spinal canal) caused by bone spurs, thickened ligaments, or bulging discs, allowing the neural structures to function without compression.

  • Neurogenic Claudication: Leg pain, heaviness, or cramping that occurs when walking or standing and is relieved by sitting or leaning forward.

  • Radiculopathy: Shooting pain, numbness, or "pins and needles" that radiates into the arms or legs due to a pinched nerve.

  • Failed Conservative Care: When physical therapy, activity modification, and epidural steroid injections fail to improve quality of life after 3–6 months.

  • Progressive Weakness: Measurable loss of motor function, such as a weakened grip or a "foot drop," indicating severe nerve compromise.

  • Spinal Stenosis: Diagnostic confirmation of a narrowed spinal canal that correlates with the patient's physical limitations and pain patterns.

  • Laminectomy: The "gold standard" procedure where the entire bony arch (lamina) at the back of the vertebra is removed to create significant room for the spinal cord.

  • Laminotomy: A less invasive approach where only a small portion of the lamina is removed, creating a "window" to access a specific pinched nerve.

  • Foraminotomy: Enlarging the "exit holes" (foramina) where the nerve roots leave the spinal canal to relieve localized compression.

  • Discectomy: Removing the specific portion of a herniated disc that is pressing directly against a spinal nerve.

  • Corpectomy: An extensive procedure where a portion of the vertebral body and adjacent discs are removed to decompress the spinal cord across a larger area.

  • Positioning: The patient is placed face down (prone) on a specialized surgical frame that minimizes pressure on the abdomen and helps open the spinal spaces.

  • Incision: A midline incision is made over the affected area of the spine. The length of the incision depends on how many levels of the spine require decompression.

  • Muscle Retraction: The spinal muscles are gently moved aside to expose the bony elements of the vertebrae.

  • Bone and Ligament Removal: The surgeon carefully removes the bone spurs (osteophytes), thickened ligaments, or portions of the lamina that are encroaching on the spinal canal.

  • Nerve Inspection: The surgeon uses magnification to ensure the nerve roots are completely free and "floating" within the newly enlarged space.

  • Closure: The muscles are allowed to return to their natural position, and the incision is closed with sutures, staples, or surgical glue.

  • Confirmation of the degree of narrowing via high-resolution MRI or CT Myelogram to plan the exact surgical levels.

  • Smoking cessation is mandatory for at least 4 weeks prior to surgery, as nicotine significantly hinders bone and tissue healing and increases the risk of infection.

  • Fasting (NPO) for 8–12 hours before the procedure to ensure safety under general anesthesia.

  • Evaluation of spinal stability via X-rays to determine if a fusion might be necessary in addition to the decompression.

  • Lumbar or Cervical MRI: The primary diagnostic tool used to visualize the soft tissues, nerves, and the extent of the canal narrowing.

  • X-rays (Flexion/Extension): Used to check for spinal instability, such as one vertebra sliding over another (spondylolisthesis).

  • CT Scan: Provides detailed images of the bony structures, which is helpful for mapping out dense bone spurs or ligament calcification.

  • Electrodiagnostic Studies (EMG/NCS): Performed to confirm that the symptoms are caused by spinal compression rather than peripheral nerve issues like diabetes or carpal tunnel.

  • Hospital stays vary from same-day discharge for simple procedures to 2–4 days for multi-level laminectomies.

  • Patients are encouraged to stand and walk within 4–6 hours of surgery to promote circulation and prevent complications like blood clots or pneumonia.

  • The "BLT" Restrictions: For the first 6 weeks, patients must strictly avoid Bending at the waist, Lifting anything over 3-5kg, and Twisting the spine.

  • Physical therapy typically begins 4–6 weeks post-operatively to strengthen the core and back muscles that support the spine.

  • While leg or arm pain often improves dramatically and quickly, the surgical site may remain sore for several weeks during the healing process.

  • Over 80% of patients experience a significant reduction in radiating limb pain and an improved ability to walk longer distances.

  • Effectively halts the progression of neurological damage, such as permanent numbness or muscle wasting.

  • Restores the ability to engage in daily activities, hobbies, and work that were previously limited by spinal stenosis symptoms.

  • Provides a durable, long-term solution for mechanical compression that does not respond to non-surgical interventions.

Laminectomy
Laminectomy

Laminectomy, often called "decompression surgery," is a major spinal procedure used to relieve pressure on the spinal cord or nerve roots by removing the lamina—the bony arch that forms the back of the spinal canal. By removing this bone and any associated thickened tissue, the surgeon creates significantly more room for the nerves to function without compression.

  • Spinal Stenosis: Narrowing of the spinal canal that leads to persistent leg pain, numbness, or a "heavy" feeling in the limbs.

  • Neurogenic Claudication: Difficulty walking or standing for long periods due to leg cramping and weakness that is relieved by sitting or leaning forward.

  • Failed Conservative Management: When symptoms persist despite months of physical therapy, medication, or steroid injections.

  • Nerve Root Compression: Significant pinching of the nerves by bone spurs or thickened ligaments that interferes with daily activity.

  • Progressive Neurological Symptoms: Measurable loss of muscle strength or sensory function in the legs or feet.

  • Open Laminectomy: The traditional approach, providing the surgeon with a wide view to decompress multiple levels of the spine.

  • Micro-Laminectomy: A minimally invasive version using smaller incisions and an operating microscope to reduce tissue trauma.

  • Hemilaminectomy: Removing only one side of the lamina to relieve pressure on a specific side while preserving more of the natural bone structure.

  • Laminotomy: Removing only a small portion of the lamina to create a window, rather than removing the entire bony arch.

  • Laminectomy with Fusion: Performing decompression alongside a spinal fusion if there is underlying instability or "slippage" of the vertebrae.

  • Positioning: The patient is placed face-down (prone) on a specialized surgical frame to allow the spine to flex and open the spaces between vertebrae.

  • Incision: A midline incision (usually 2–5 inches long) is made over the affected area of the spine.

  • Exposure: The surgeon detaches the back muscles from the bone to access the posterior elements of the vertebrae.

  • Bone Removal: Using specialized tools like rongeurs or high-speed drills, the surgeon removes the lamina and the spinous process (the bony bump on the back).

  • Decompression: Thickened ligaments (ligamentum flavum) and bone spurs are removed to ensure the spinal cord and nerves can "breathe" within the enlarged canal.

  • Closure: The muscles are sewn back into place, and the skin is closed with stitches, staples, or surgical glue.

  • Diagnostic mapping via MRI to identify the exact levels of compression (e.g., L3-L4, L4-L5) and X-rays to assess spinal stability.

  • Blood thinners (like aspirin or clopidogrel) must be stopped 5–7 days prior to surgery to prevent the risk of bleeding in the spinal canal.

  • Fasting (NPO) for 8–12 hours before the procedure to ensure safety under general anesthesia.

  • Discussion of the recovery phase and the specialized "No BLT" movement restrictions that will be required.

  • Lumbar or Cervical MRI: The primary test to visualize the nerves and determine the exact location and severity of the narrowing.

  • X-rays (Flexion/Extension): Used to check if the spine is "wobbly" or if one bone is sliding over another (spondylolisthesis).

  • CT Myelogram: Sometimes used if an MRI is not possible, providing a detailed look at the space around the spinal cord using contrast dye.

  • Electrodiagnostic Studies (EMG): Performed to confirm that the leg or arm symptoms are caused by the spinal blockage rather than other nerve issues.

  • Hospital stays typically range from 1 to 3 days, though micro-procedures may be performed on a same-day basis.

  • Patients are required to stand and walk within 4–6 hours of surgery to promote circulation and prevent blood clots.

  • The "No BLT" Rule: For 6 weeks post-op, you must strictly avoid Bending at the waist, Lifting anything over 3kg, and Twisting the spine.

  • Stitches or staples are usually removed at 10–14 days, and the incision must be kept dry for the first 5 days.

  • Physical therapy usually begins at the 4–6 week mark to rebuild "core" strength and stabilize the back muscles.

  • Over 80% of patients report immediate and significant relief from radiating leg pain and cramping.

  • Dramatically increases walking distance and the ability to stand comfortably for longer periods.

  • Halts the progression of nerve damage that could otherwise lead to permanent weakness or muscle wasting.

  • Restores the ability to engage in daily activities and hobbies that were previously hindered by spinal stenosis.

Spinal Fusion Surgery

Spinal Fusion is a major surgical procedure designed to permanently connect two or more vertebrae, eliminating painful motion between them. The procedure is characterized by Minimally Invasive Spine Surgery (MISS) and robotic assistance, utilizing bone grafts and high-precision hardware to create a solid bone mass. This approach aims to stabilize the structural integrity of the spine while protecting the surrounding nerves and musculature.

  • Chronic Pain: Debilitating back or neck pain that has not responded to physical therapy, medications, or injections.

  • Neurological Symptoms: Persistent numbness, tingling, or weakness in the arms or legs caused by sustained nerve compression.

  • Mechanical Instability: Significant pain that worsens with specific movements, such as bending, twisting, or lifting.

  • Spinal Deformity: Visible curvature or a sensation of the spine "slipping," often associated with structural instability.

  • Functional Limitation: Difficulty standing or walking for extended periods due to structural spinal narrowing or collapse.

  • Trauma or Tumor: Severe pain or instability following a spinal fracture or the surgical removal of a spinal tumor.

  • Degenerative Disc Disease: Where worn-out discs cause painful friction and micro-motion between vertebrae.

  • Spondylolisthesis: A condition where one vertebra slips forward over the one below it, potentially pinching nerves.

  • Spinal Stenosis: Resulting in the narrowing of the spinal canal and significant nerve pressure.

  • Scoliosis or Kyphosis: Involving abnormal curvatures of the spine that require corrective alignment and stabilization.

  • Pseudoarthrosis: A condition where a previous fusion attempt failed to heal into a solid bone mass.

  • Minimally Invasive Spine Surgery (MISS): Techniques that use tubular retractors to spread muscles rather than cutting them, reducing blood loss and recovery time.

  • Robotic-Assisted Fusion: The use of advanced guidance systems to ensure screws and rods are placed with sub-millimeter accuracy.

  • Anterior Lumbar Interbody Fusion (ALIF): Accessing the spine through the abdomen to provide a large surface area for the fusion cage.

  • Lateral Interbody Fusion (XLIF/LLIF): A side-access approach that avoids major back muscles and the spinal canal, often allowing for faster mobilization.

  • Posterior Lumbar Interbody Fusion (PLIF): The traditional approach from the back, offering the most direct access to compressed nerves and the spinal canal.

  • Transforaminal Lumbar Interbody Fusion (TLIF): An evolution of the posterior approach that accesses the disc space from a more lateral angle to reduce nerve retraction.

  • Surgical Mapping: Digital mapping or Augmented Reality (AR) is used to project the patient's internal anatomy for the surgeon.

  • Access: Minimally invasive incisions are made to reach the spine from the most appropriate clinical angle (front, back, or side).

  • Disc Removal: The intervertebral disc or damaged bone is removed to decompress nerves and create space for the fusion.

  • Cage Insertion: A "cage" or spacer filled with bone graft material is inserted between the vertebrae to stimulate bone growth.

  • Hardware Stabilization: Robotic arms often assist in the precise placement of pedicle screws and rods to hold the vertebrae steady while they fuse.

  • Biological Stimulation: Bone Morphogenetic Proteins (BMP) or specialized bone grafts are applied to accelerate the natural bone-healing process.

  • Smoking Cessation: Patients must commit to a strict no-nicotine program, as smoking significantly increases the risk of fusion failure (non-union).

  • Pre-habilitation: Strengthening "core" stabilizer muscles through directed physical therapy to support the spine post-operatively.

  • Home Setup: Coordinate a "home recovery station" to avoid the need for bending, lifting, or twisting during the initial healing phase.

  • Bone Health Optimization: Undergo a bone density scan (DEXA) to ensure the vertebrae are strong enough to support surgical hardware.

  • Bracing Consultation: Discuss the use of a post-operative back brace with the surgical team to ensure proper fitting and sizing.

  • Standing X-rays and MRI: Used to identify the exact source of nerve compression and the degree of mechanical instability.

  • High-resolution CT Scan: Essential for 3D surgical planning and robotic navigation mapping.

  • Electrocardiogram (EKG): Along with comprehensive blood panels to confirm cardiovascular readiness for a major procedure.

  • Neurological Baseline Testing: Measuring nerve conduction and muscle strength to provide a comparison for post-operative recovery.

  • DEXA Scan: To evaluate the quality of the "host bone" for successful graft integration and hardware stability.

  • Immediate Recovery: Hospital stays typically last 1 to 3 days, with an emphasis on early, assisted walking to prevent blood clots.

  • The "No BLT" Rule: For the first 3 to 6 months, patients must strictly avoid Bending at the waist, Lifting over 3kg, and Twisting the spine.

  • Bracing: Wear a customized back brace as prescribed to maintain spinal alignment during the critical fusion window.

  • Phased Physical Therapy: Focusing on core stabilization and safe movement patterns once the initial bone healing is confirmed.

  • Long-term Monitoring: Routine follow-up imaging (X-rays or CT) is required to confirm the success of the bone bridge across the joint.

  • Activity Resumption: Gradual return to a more active lifestyle once the vertebrae have fused into a single, solid, and stable bone mass.

  • Significant Pain Reduction: Achieves a 70% to 90% success rate for patients with chronic instability-related pain.

  • Enhanced Precision: Utilizes AR and robotic technology to make surgery safer and more accurate than traditional "freehand" methods.

  • Neurological Protection: Stabilizes the spine to prevent further nerve injury or progressive physical deformity.

  • Accelerated Healing: Stimulates the body's natural recovery using bio-engineered proteins for faster bone growth.

  • Permanent Stability: Eliminates the painful micro-motion that causes chronic inflammation and structural wear.

Minimally Invasive Spine Surgery (MISS)

Minimally Invasive Spine Surgery (MISS) is an advanced surgical approach used to treat spinal conditions—such as herniated discs or spinal stenosis—through significantly smaller incisions than traditional "open" surgery. The primary objective is to achieve the same clinical results while minimizing trauma to the surrounding muscles and tissues, leading to faster recovery and less post-operative pain.

  • Herniated Discs: For procedures like a lumbar discectomy to relieve nerve pressure.

  • Spinal Stenosis: When a laminotomy or foraminotomy is required to enlarge the spinal canal or nerve exit points.

  • Spinal Instability: For spinal fusions (such as TLIF or XLIF) that require hardware stabilization.

  • Failed Conservative Care: When months of physical therapy and injections have failed to resolve chronic radiating pain.

  • Desire for Faster Recovery: For patients who wish to return to work and daily activities more quickly with less reliance on heavy pain medication.

  • Tubular Retraction: Using a series of dilating tubes to stretch muscle fibers apart rather than cutting them from the bone.

  • Endoscopic Spine Surgery: Utilizing a tiny camera (endoscope) through a "keyhole" incision to visualize the spinal anatomy on a high-definition monitor.

  • Microscopic MISS: Operating through a tubular retractor using a high-powered surgical microscope for enhanced lighting and 3D depth perception.

  • Percutaneous Hardware Placement: Inserting screws and rods through small skin punctures using real-time X-ray (fluoroscopy) or robotic guidance.

  • Lateral Access (XLIF/LLIF): Reaching the spine through the side of the body to avoid the major back muscles and the spinal canal.

  • Precision Mapping: Surgeons use pre-operative MRI or CT scans to create a precise "map" for the entry point, as the view during surgery is focused on a small area.

  • Keyhole Incision: Instead of a long midline incision, one or more small (1–2 cm) incisions are made over the target area.

  • Muscle Dilation: A thin guide wire is inserted, followed by progressively larger "tubular retractors" that gently push muscle fibers aside to create a tunnel to the spine.

  • Decompression or Repair: Using specialized long-handled miniature tools, the surgeon removes bone spurs or disc fragments through the tube.

  • Hardware Insertion (if needed): If a fusion is being performed, screws and rods are guided into place using robotic navigation or fluoroscopy through the same small ports.

  • Tube Removal: Once the repair is complete, the tube is withdrawn, and the muscle fibers naturally fall back into their original position.

  • Closure: The tiny skin incisions are closed with a single stitch or surgical glue, requiring only a small bandage.

  • Diagnostic confirmation via MRI or CT scan to ensure the surgical plan is tailored to the specific nerve compression site.

  • Fasting (NPO) for 8–12 hours prior to the procedure to ensure safety under anesthesia.

  • Smoking cessation is critical, particularly if a fusion is planned, as nicotine restricts blood flow and prevents the bone from growing and healing.

  • Pre-operative physical assessment to ensure the patient is a candidate for a same-day or outpatient surgical procedure.

  • High-Resolution MRI: To provide a detailed view of the soft tissues and the exact location of the disc herniation or stenosis.

  • CT Scan with 3D Reconstruction: Often used for surgical planning, especially when robotic navigation is being utilized for hardware placement.

  • X-ray (Flexion/Extension): To assess for any underlying spinal instability that might require a fusion instead of a simple decompression.

  • Blood Panels: To check for clotting factors and overall health markers before undergoing general anesthesia.

  • Hospital Stay: Frequently performed as an outpatient (same-day) procedure; patients often go home within 3–4 hours of waking up.

  • Pain Management: Patients typically experience significantly less muscle soreness and have a lower requirement for opioid painkillers than open surgery.

  • Mobilization: Walking is encouraged almost immediately—often within 2 hours of the procedure—to promote circulation.

  • Recovery Timeline: Most patients return to desk work within 1–2 weeks and can begin light exercise by 4–6 weeks post-op.

  • Wound Care: The small incisions must be kept dry for the first few days, but they generally heal very quickly with minimal scarring.

  • Reduced Tissue Trauma: By stretching rather than cutting muscles, the body heals much faster with less internal scarring.

  • Lower Infection Rates: Smaller incisions and less exposure of internal tissues to the environment significantly reduce the risk of post-operative infection.

  • Minimal Blood Loss: Many procedures result in less than a tablespoon of blood loss, virtually eliminating the need for transfusions.

  • Equal Clinical Outcomes: Long-term studies show that MISS is just as effective as traditional open surgery for pain relief and functional improvement.

Spine Fracture Fixation

Spinal Fracture Fixation is a major surgical procedure used to stabilize a broken vertebra (backbone) to protect the spinal cord and prevent deformity. It is primarily performed for "unstable" fractures caused by high-impact trauma, such as car accidents or falls, or for "pathological" fractures resulting from osteoporosis or cancer. By utilizing metal hardware or medical-grade cement, the procedure aims to restore the structural integrity of the spinal column.

  • Unstable Fractures: When the break is severe enough that the spine can no longer support the body's weight or maintain alignment.

  • Neurological Threat: If bone fragments are pressing on or have entered the spinal canal, risking damage to the spinal cord or nerve roots.

  • Progressive Deformity: To correct or prevent a "hunchback" deformity (kyphosis) caused by a collapsing vertebra.

  • Intractable Pain: When a compression fracture causes debilitating pain that does not respond to bracing or medication.

  • Pathological Risk: To stabilize a vertebra weakened by tumors or severe osteoporosis before a complete collapse occurs.

  • Open Reduction and Internal Fixation (ORIF): The traditional approach where an incision is made to manually realign the bones and secure them with screws and rods.

  • Kyphoplasty: A minimally invasive procedure where a balloon is inflated inside a compressed vertebra to restore height before injecting bone cement.

  • Vertebroplasty: Injecting medical-grade bone cement directly into a fractured vertebra to "glue" the cracks and provide immediate stability.

  • Percutaneous Pedicle Screw Fixation: A minimally invasive technique where screws are inserted through small skin punctures using robotic or X-ray guidance.

  • Decompression and Fusion: Removing bone fragments that are pinching the spinal cord (decompression) and then joining the vertebrae together (fusion).

  • Real-Time Imaging: The surgeon uses Fluoroscopy (live X-ray) or 3D navigation to visualize the fracture and plan the exact placement of hardware.

  • Hardware Placement: For trauma cases, titanium pedicle screws are drilled into the healthy vertebrae above and below the break.

  • Internal Splinting: Two metal rods are contoured and connected to the screws, acting as a permanent internal splint to hold the spine rigid.

  • Bone Grafting: Small pieces of bone (graft) are placed over the stabilized area to stimulate the vertebrae to grow together into one solid mass.

  • Cement Injection (for Compression): In kyphoplasty or vertebroplasty, a needle is guided into the bone, and polymethylmethacrylate (PMMA) cement is injected to stabilize the fracture.

  • Neuromonitoring: Throughout the procedure, electrical signals in the limbs are monitored to ensure the spinal cord remains safe while hardware is being installed.

  • Stabilization: Trauma patients often remain on "log-roll" precautions (moving the body as a single unit) and wear a rigid brace until the moment of surgery.

  • Diagnostic Mapping: Extensive imaging via CT Scan (to see bone fragments) and MRI (to assess ligament and spinal cord health).

  • Fasting (NPO): No food or drink for 8–12 hours prior to the procedure to ensure safety under general anesthesia.

  • Surgical Fitting: Measurement for a custom-fitted TLSO (hard plastic brace) that will be required immediately after the surgery.

  • CT Scan: Provides the most detailed 3D view of the bony architecture and the specific pattern of the break.

  • MRI Scan: Essential for checking the "soft tissues," including the spinal cord, discs, and the ligaments that hold the spine together.

  • Dynamic X-rays: Taken in different positions to check if the fracture site moves or "slides" when the patient shifts weight.

  • Blood Panels: Routine screens to assess for blood loss, infection, and readiness for a potentially long surgical procedure.

  • Hospital Stay: Typically ranges from 3 to 7 days, depending on the severity of the trauma and the patient's mobility.

  • Early Mobilization: Walking with assistance is encouraged within 24 hours to prevent blood clots and keep the lungs clear.

  • Bracing Requirements: Many patients must wear a custom-fitted TLSO brace whenever they are out of bed for 6 to 12 weeks.

  • The "No BLT" Rule: Strict avoidance of Bending, Lifting (over 2kg), and Twisting for at least 3 months to allow the bone to heal.

  • Healing Timeline: It takes 3 to 6 months for the bone graft to fully "knit" the vertebrae together into a solid fusion.

  • Prevents Paralysis: Stabilizing the spine immediately protects the spinal cord from further injury caused by moving bone fragments.

  • Pain Reduction: Provides a solid internal structure that eliminates the "grinding" and mechanical pain associated with a broken vertebra.

  • Deformity Correction: Restores the natural alignment of the spine, preventing a permanent "hunchback" posture.

  • Early Return to Mobility: Hardware provides enough immediate stability to allow patients to sit up and walk much sooner than traditional bed rest would allow.

  • Long-Term Durability: Titanium hardware is intended to be permanent, providing a lifelong scaffold for the stabilized spinal segment.

Pedicle Screw Fixation

Pedicle Screw Fixation is a major surgical procedure used to stabilize the spine by inserting specialized screws into the pedicles—the strongest, thickest parts of the vertebral bone. These screws act as permanent "anchor points" for metal rods that hold the spine in a fixed position, providing the necessary stability for a successful spinal fusion.

  • Spinal Instability: When vertebrae move excessively or abnormally, causing chronic pain or risk of nerve damage.

  • Severe Fractures: To stabilize a broken vertebra and protect the spinal cord while the bone heals.

  • Scoliosis or Kyphosis: To provide the mechanical leverage needed to straighten and hold the spine in a corrective alignment.

  • Spondylolisthesis: When one vertebra has slipped forward over another, requiring the bones to be pulled back into place and locked.

  • Multi-Level Fusion: For extensive degenerative disease where multiple segments of the spine need to be joined into a single, solid unit.

  • Open Fixation: The traditional approach involving a midline incision, giving the surgeon a direct and wide view of the bony anatomy.

  • Minimally Invasive (Percutaneous) Fixation: Inserting screws through small "keyhole" skin punctures using specialized guidance, which reduces muscle trauma.

  • Robotic-Assisted Fixation: Utilizing a robotic arm to guide the drill and screw into the pedicle with sub-millimeter precision based on a pre-operative CT map.

  • Computer-Navigated Fixation: Using real-time 3D "GPS-like" technology to track surgical instruments in relation to the patient's anatomy.

  • Fluoroscopic Guidance: Using continuous, real-time X-ray imaging during the procedure to verify the angle and depth of each screw.

  • Identification: Using real-time imaging or robotic navigation, the surgeon identifies the "entry point" on the pedicle, the narrow bridge of bone connecting the front and back of the vertebra.

  • Drilling & Tapping: A small pilot hole is drilled through the pedicle and into the vertebral body. The hole is then "tapped" (threaded) to ensure the screw fits securely.

  • Screw Insertion: Permanent titanium or stainless steel screws are driven deep into the bone. Typically, two screws are placed in each vertebra (one on each side).

  • Rod Placement: Once all levels are instrumented, a metal rod is contoured and dropped into the "heads" of the screws.

  • Final Locking: "Set screws" are tightened into the screw heads to lock the rod in place, creating a rigid internal scaffold.

  • Bone Grafting: Small pieces of bone are packed around the hardware to stimulate the growth of a permanent bone bridge (fusion).

  • Precision Mapping: Mandatory high-resolution CT scans or 3D X-rays are used to measure the exact width and angle of the pedicles, which vary significantly between patients.

  • Medication Adjustment: Blood thinners (such as aspirin or clopidogrel) must be stopped 5–7 days prior to prevent bleeding in the spinal canal.

  • Fasting (NPO): No food or drink for 8–12 hours before the procedure to ensure safety under general anesthesia.

  • Neuromonitoring Setup: Preparation for intra-operative electrical monitoring of the nerves in the legs to ensure safety during screw placement.

  • Thin-Cut CT Scan: Provides the most accurate measurement of the "pedicle diameter" to help the surgeon select the correct screw size.

  • MRI Scan: Used to visualize the proximity of the spinal cord and nerve roots to the planned screw path.

  • Bone Density Scan (DEXA): To ensure the bone is strong enough to hold the screws; in patients with osteoporosis, the screws may require specialized cement "augmentation."

  • Blood Panels: Routine screens to assess kidney function and clotting factors before a major surgical intervention.

  • Hospital Stay: Typically ranges from 2 to 5 days, depending on the complexity of the fusion.

  • Early Mobilization: Patients are encouraged to stand and take a few steps within 24 hours to prevent blood clots and promote recovery.

  • The "No BLT" Rule: For 3 to 6 months, you must strictly avoid Bending at the waist, Lifting anything over 2–4kg, and Twisting the spine.

  • Bracing: Many patients are required to wear a TLSO (hard plastic brace) for 6–12 weeks whenever they are out of bed to protect the hardware.

  • Hardware Status: The screws and rods are intended to stay in the body forever and are rarely removed unless they cause irritation or become infected.

  • Immediate Internal Stability: Provides a rigid structure that allows patients to move and walk much sooner than bone grafting alone would permit.

  • High Fusion Success Rate: Fixation achieves a solid bone bridge in over 90% of cases by preventing any micro-motion at the surgical site.

  • Corrective Power: Allows surgeons to mechanically realign a curved or slipped spine, restoring a more natural posture.

  • Neurological Protection: By locking the spine in place, it prevents the "shifting" that can lead to chronic nerve pinching or spinal cord injury.

  • Durable Support: Provides a lifelong permanent scaffold for the stabilized spinal segments.

Vertebroplasty/Kyphoplasty

Vertebroplasty and kyphoplasty are minimally invasive image-guided procedures used primarily to treat painful vertebral compression fractures. These fractures are most commonly caused by osteoporosis, but can also result from spinal tumors or trauma. Left untreated, these fractures can lead to chronic pain, height loss, and a hunched posture known as kyphosis.

  • Persistent Pain: Severe back pain caused by a vertebral compression fracture that does not respond to conservative management.

  • Limited Mobility: Difficulty performing daily activities or walking due to spinal instability and pain.

  • Height Loss: Noticeable decrease in stature or the development of a hunched back (kyphosis) following a fracture.

  • Osteoporosis Complications: Fractures occurring in patients with low bone density who require immediate stabilization.

  • Spinal Tumors: Compression fractures resulting from certain types of cancer or benign spinal lesions.

  • Trauma Impact: Acute fractures caused by a fall or injury that compromise the structural integrity of the spine.

  • Vertebroplasty: A procedure where a thin needle is guided via X-ray into the fractured vertebra to inject medical-grade bone cement directly for stabilization.

  • Kyphoplasty: A technique where a small balloon is inflated inside the vertebra to create a cavity and help restore lost height before injecting cement.

  • Synthetic Patching: Use of specialized bone cement (PMMA) to act as an internal cast and seal the fracture.

  • Device Occlusion: Deployment of balloons or needles to stabilize the bone without the need for major open surgery.

  • Diagnostic Synchronization: Utilization of X-ray (fluoroscopy) to guide the needle or balloon precisely into the fractured level.

  • Cavity Creation: In kyphoplasty cases, a balloon is expanded to create space and lift the compressed bone.

  • Cement Deployment: Medical-grade bone cement is injected into the fracture or the newly formed space to seal it permanently.

  • Monitoring: Real-time imaging ensures the cement is perfectly positioned and contained within the vertebra before finishing.

  • Short Procedure Time: These treatments typically take 30 to 60 minutes per vertebral level.

  • Fluoroscopic Guidance: Real-time X-ray mapping to ensure robotic-like precision during needle placement.

  • Balloon Inflation Systems: Advanced technology used in kyphoplasty to specifically target height restoration in collapsed vertebrae.

  • High-Viscosity Cements: Modern materials designed to reduce the risk of leakage and provide immediate structural support.

  • Minimally Invasive Access: Use of small puncture sites rather than traditional incisions, leading to faster healing and less scarring.

  • MRI or CT Scan: Detailed 3D mapping to confirm the age, location, and severity of the compression fracture.

  • Bone Density Test (DEXA): To evaluate the underlying health of the skeleton and the risk of future fractures.

  • Physical Examination: Assessment of localized tenderness and neurological function.

  • X-Ray Imaging: To determine the degree of vertebral collapse and spinal alignment.

  • Rapid Pain Relief: Approximately 70–90% of patients report significant improvement, often within 24 to 48 hours.

  • Improved Mobility: Restores the ability to walk and perform daily routines on the same day as the procedure.

  • Internal Stability: The hardened cement prevents the painful movement of bone fragments.

  • Reduced Mortality: Helps prevent complications related to prolonged immobility and bed rest.

  • Long-Term Cure: Provides a permanent stabilization of the fractured bone with high technical success rates.

  • Short Hospital Stay: Often performed as an outpatient procedure, allowing patients to return home the same day.

  • Activity Restrictions: Strenuous exertion and heavy lifting should be avoided for a few weeks to ensure proper healing.

  • Bone Health Management: Regular follow-ups often include bone-strengthening medications and nutritional supplements like Calcium and Vitamin D.

  • Immediate Improvement: Patients typically experience a swift return to light activity and significant reduction in chronic pain.

Spinal Tumor Removal

Spinal Tumor Removal is a complex procedure to remove abnormal growths from the spinal canal or the vertebrae. The primary goals are to decompress the spinal cord, stabilize the spine, and obtain a tissue sample (biopsy) to determine if the tumor is benign or malignant. By removing or debulking the mass, the surgeon aims to preserve neurological function and restore the structural integrity of the spinal column.

  • Spinal Cord Compression: When a tumor is pressing on the cord, causing progressive weakness, numbness, or loss of coordination.

  • Intractable Pain: Severe, localized back pain that does not respond to medication and often worsens at night or when lying down.

  • Neurological Deficits: Loss of bladder or bowel control, difficulty walking, or radiating pain in the arms or legs.

  • Pathological Fracture Risk: When a tumor has eaten away enough of the vertebral bone to make the spine unstable or prone to collapse.

  • Need for Diagnosis: To obtain a tissue sample to guide further cancer treatments like targeted radiation or chemotherapy.

  • Intradural-Intramedullary: Tumors that grow inside the actual tissue of the spinal cord (e.g., astrocytomas or ependymomas).

  • Intradural-Extramedullary: Tumors that grow inside the protective sac (dura) but outside the spinal cord itself (e.g., meningiomas or schwannomas).

  • Extradural: Tumors located outside the dura, usually within the bones of the vertebrae (most common in metastatic cancers).

  • Microsurgical Access: A midline incision is made over the tumor site, and a laminectomy (removing the back of the vertebrae) is performed to reach the spinal canal.

  • Durotomy: If the tumor is inside the protective sac, the surgeon uses an operating microscope to make a precise incision in the dura mater.

  • Ultrasonic Aspiration: Surgeons often use a CUSA (Cavitron Ultrasonic Surgical Aspirator), which uses sound waves to fragment and vacuum out the tumor without pulling on delicate nerves.

  • Tumor Resection: * Benign Tumors: The goal is usually "gross total resection" (complete removal).
    Malignant Tumors: If the tumor is wrapped around vital nerves, a "subtotal resection" (partial removal) may be performed to avoid causing paralysis.

  • Stabilization: If the tumor or the surgery has destroyed significant bone, pedicle screws and rods are installed to prevent the spine from collapsing.

  • Neuromonitoring: Throughout the surgery, electrical signals (SSEP/MEP) are monitored in the limbs to ensure the spinal cord remains safe.

[Image showing microscopic resection of an intradural tumor]

  • High-Dose Steroids: Patients often receive Dexamethasone for 24–48 hours before surgery to reduce spinal cord swelling and inflammation.

  • Diagnostic Mapping: High-resolution MRI with Contrast is used to visualize the tumor’s relationship to nerve roots and the spinal cord.

  • Systemic Screening: PET or CT scans may be used to determine if the spinal tumor has spread from a primary site elsewhere in the body.

  • Fasting (NPO): No food or drink for 8–12 hours prior to the procedure to ensure safety under general anesthesia.

  • MRI with Contrast: The gold standard for seeing the exact borders of the tumor and its vascularity.

  • CT Scan: Best for assessing how much of the vertebral bone has been destroyed or weakened by the growth.

  • PET Scan: Used to check for other tumor sites in the body if the spinal mass is suspected to be metastatic.

  • Neurological Baseline: A comprehensive exam to document muscle strength and sensation before surgery for post-operative comparison.

  • Hospital Stay: Typically 3 to 7 days; patients often spend the first 24 hours in a Neuro-ICU for close monitoring.

  • Immediate Recovery: Mobilization depends on the patient's neurological status, but sitting up and walking with assistance is encouraged as soon as possible.

  • Pain Management: A combination of patient-controlled analgesia (PCA) and specialized nerve pain medications (like Gabapentin) is common.

  • Follow-up Adjuvant Therapy: If the tumor was malignant, radiation or chemotherapy typically begins 4 to 6 weeks after the surgical wound has fully healed.

  • Long-Term Surveillance: Regular MRI scans (every 3–6 months initially) are mandatory to ensure the tumor does not return.

  • Preserves Mobility: Decompressing the spinal cord can prevent permanent paralysis and restore the ability to walk.

  • Significant Pain Relief: Removing the mass that is stretching the dura or compressing nerves provides major relief from localized and radiating pain.

  • Structural Stability: Fusion and hardware placement restore the spine's ability to support weight and maintain alignment.

  • Information for Treatment: Provides a definitive diagnosis, allowing oncologists to tailor the best possible follow-up cancer therapies.

Intradural Tumor Surgery

Intradural Tumor Surgery is a highly delicate neurosurgical procedure to remove tumors located inside the dura mater (the tough outer membrane protecting the spinal cord). These tumors are classified as Extramedullary (outside the cord but inside the membrane, like meningiomas) or Intramedullary (growing inside the spinal cord tissue itself). The surgery focuses on preserving neurological function while removing as much of the abnormal growth as possible.

  • Spinal Cord Compression: When the tumor’s growth begins to pinch the spinal cord, leading to a loss of coordination or "heaviness" in the limbs.

  • Progressive Weakness: Measurable loss of muscle strength in the arms or legs, or a change in your ability to walk.

  • Sensory Disturbances: Persistent numbness, tingling, or "electric shock" sensations that correlate with a mass seen on imaging.

  • Autonomic Dysfunction: New or worsening issues with bowel or bladder control, which may indicate urgent spinal cord pressure.

  • Radicular Pain: Severe, radiating pain that follows the path of a specific nerve root being compressed by the tumor.

  • Microsurgical Resection: The primary method, using a high-powered operating microscope to distinguish between the tumor and the delicate spinal cord tissue.

  • Laminectomy/Laminoplasty: Creating an opening in the back of the spinal column to provide the surgeon access to the dural sac.

  • Myelotomy: A specialized technique for intramedullary tumors where a precise incision is made in the back of the spinal cord to reach the growth inside.

  • Ultrasonic Aspiration (CUSA): Using sound waves to fragment and remove tumor tissue without the physical pulling or tugging associated with traditional tools.

  • Endoscopic-Assisted Surgery: Utilizing tiny cameras in certain cases to provide a better view of the tumor’s "hidden" edges.

[Image showing a microsurgical dural incision and tumor exposure]

  • Accessing the Dura: A midline incision is made over the tumor site, and a portion of the vertebral bone (lamina) is removed to expose the protective dural membrane.

  • Durotomy: The surgeon carefully opens the dura mater under high magnification to reveal the spinal cord and the tumor.

  • Micro-Dissection: Using specialized micro-instruments, the surgeon gently peels the tumor away from the spinal cord (for extramedullary tumors) or removes it from within the cord (for intramedullary tumors).

  • Neuromonitoring: Throughout the procedure, electrical signals (SSEP and MEP) are monitored to ensure the nerves are not being stressed or injured.

  • Dural Closure: The dura is stitched shut with extremely fine, water-tight sutures. A synthetic patch or surgical "fibrin glue" is often used to prevent any leaks of spinal fluid.

  • Final Closure: The spinal muscles are returned to their natural position, and the skin is closed with sutures or surgical glue.

  • Diagnostic Imaging: High-resolution MRI both with and without Gadolinium contrast is mandatory to differentiate the tumor from healthy nerve tissue.

  • Anti-Inflammatory Steroids: Patients are often started on Dexamethasone 24–48 hours before surgery to reduce spinal cord swelling and optimize safety.

  • Neuromonitoring Setup: Coordination with a specialized neuro-monitoring team to place electrodes for real-time tracking of nerve signals during the operation.

  • Fasting (NPO): No food or drink for 8–12 hours prior to the procedure to ensure safety under general anesthesia.

  • Contrast-Enhanced MRI: The most critical test to map the tumor’s size, location, and its relationship to the spinal cord.

  • CT Scan: Used to evaluate the bony anatomy and ensure the laminectomy can be performed safely without causing instability.

  • Pre-operative Baseline Neurological Exam: A detailed assessment of motor and sensory function to serve as a benchmark for recovery.

  • Blood Panels: Standard screens to check kidney function (for contrast processing) and ensure proper blood clotting.

  • Hospital Stay: Typically 3 to 7 days; the first 24 hours are usually spent in a Neuro-ICU for hourly neurological checks.

  • Flat Bed Rest: Depending on the strength of the dural seal, you may be required to lie perfectly flat for 24 to 48 hours to prevent a spinal fluid leak.

  • Rehabilitation: Most patients require 3–6 months of physical therapy. Nerve recovery is a slow process, and strength improvements can continue for up to a year.

  • Sensory Changes: It is common to experience temporary "altered sensation" (tingling or coldness) as the spinal cord adapts to the removal of the pressure.

  • Surveillance: Annual follow-up MRIs are mandatory for several years to ensure the tumor does not recur.

  • Halts Neurological Decline: Effectively stops the progression of paralysis or sensory loss caused by tumor growth.

  • High Cure Rate for Benign Growths: Many intradural tumors, such as schwannomas or meningiomas, can be cured with complete surgical removal.

  • Neurological Recovery: Removing the pressure often allows the spinal cord to heal, restoring strength and coordination over several months.

  • Definitive Diagnosis: Provides the tissue sample needed to determine if further treatments, such as radiation or targeted therapy, are necessary.

Cervical Laminoplasty

A Cervical Laminoplasty is a non-fusion, decompression surgical procedure performed in the neck to relieve pressure on the spinal cord and nerves. By expanding the spinal canal—which may be narrowed due to age-related changes or arthritis—this procedure effectively treats compression while preserving the natural motion of the spine.

This surgery is primarily recommended for patients with multi-level compression of the spinal cord who maintain a healthy natural neck curvature. Key indications include:

  • Cervical Spondylotic Myelopathy (CSM): Inadequate spinal cord function due to bone spurs or degenerative changes.

  • Ossification of the Posterior Longitudinal Ligament (OPLL): A condition where spinal ligaments harden into bone, pressing on the cord.

  • Congenital Narrowing: Being born with a naturally narrow spinal canal.

  • Fine Motor Skill Loss: Difficulty buttoning shirts, changes in handwriting, or loss of coordination.

  • Balance Issues: Noticeable gait disturbances or difficulty walking.

  • Open-Door Laminoplasty: The most common technique where one side of the lamina is hinged and the other is opened like a door.

  • French-Door Laminoplasty: A technique where the midline of the lamina is split and both sides are hinged to create an opening in the center.

  • Titanium Plate Fixation: Using tiny, specialized plates and screws to securely hold the "door" in its new, expanded position.

  • Bone Graft Wedging: Inserting small wedges of bone graft material to maintain the widened canal space during healing.

  • Surgical Access: A 3-to-4-inch incision is made in the back of the neck, and muscles are moved aside to expose the lamina (the back of the vertebrae).

  • Creating the Hinge: The surgeon carefully cuts a groove on one side of the lamina to act as a flexible hinge.

  • Opening the Canal: The opposite side of the lamina is cut through, allowing the bone to be "swung" outward, widening the canal by up to 30%.

  • Securing the Gap: Small titanium plates or bone wedges are placed in the gap to keep the canal permanently open.

  • Verification: Real-time imaging ensures the spinal cord is fully decompressed before the incision is closed.

  • Fasting: Patients are typically required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Blood tests, ECG, and chest X-rays are conducted to assess overall surgical health.

  • Medication Review: Discussing current medications with the surgical team to manage blood thinners or anti-inflammatory drugs.

  • Recovery Planning: Arranging for a support person to assist with home care during the initial weeks of recovery.

  • MRI Scan: The gold standard for visualizing the extent of spinal cord compression and soft tissue health.

  • CT Scan: Provides a detailed view of bony changes, such as OPLL or bone spurs.

  • X-rays: Used to evaluate the natural curvature (lordosis) of the neck, which is a key factor for surgical success.

  • EMG/Nerve Conduction Study: To confirm the specific nerve levels affected and rule out other neurological conditions.

  • Hospital Stay: Most patients remain in the hospital for 1 to 3 days, with walking encouraged just hours after surgery.

  • Short-Term Recovery: A return to light activities or desk work is typically possible within 1 to 4 weeks.

  • Activity Restrictions: Strenuous activities should be avoided for 6 to 12 weeks to allow for proper bone healing.

  • Long-Term Rehabilitation: Physical therapy is often initiated to rebuild neck muscle strength and maintain flexibility.

  • Motion Preservation: Unlike spinal fusion, this procedure maintains the natural movement and flexibility of the neck.

  • Extensive Decompression: Effectively treats multiple levels of the spine through a single approach.

  • Reduced Risk of Adjacent Segment Disease: By avoiding fusion, it reduces the extra stress placed on the discs above and below the surgical site.

  • Improved Neurological Function: Offers significant relief from radiating pain and helps prevent the progression of spinal cord damage.

Corpectomy (Vertebral Body Removal)

A Corpectomy, also known as a vertebrectomy, is a major spinal surgery involving the removal of all or part of a vertebral body to relieve significant pressure on the spinal cord and nerves. Unlike a discectomy, which only removes disc material, a corpectomy is used when disease or damage extends into the bone of the vertebra itself.

Surgeons typically recommend this procedure for severe conditions that cannot be treated with less invasive methods. Indications include:

  • Severe Spinal Stenosis: Confluent narrowing that extends behind the vertebral body.

  • Vertebral Tumors: Primary or metastatic tumors that destroy the bone and compress the spinal cord.

  • Spinal Fractures: Traumatic burst fractures where bone fragments are pushed into the spinal canal.

  • Bone Infections: Conditions like osteomyelitis or tuberculosis that cause vertebral collapse.

  • Cervical Myelopathy: Compression of the spinal cord in the neck causing loss of coordination or bladder control.

  • Anterior Cervical Corpectomy: Performed through the front of the neck to access the cervical spine.

  • Side-Access Lumbar Corpectomy: Approached from the side of the body for issues in the lower back.

  • Reconstruction with Strut Grafts: Using bone from the patient (autograft) or a donor (allograft) to fill the gap.

  • Reconstruction with Expandable Cages: Using titanium or synthetic mesh cages packed with bone graft for structural support.

  • Surgical Access: The surgeon makes an incision, most commonly through the front or side, depending on the location of the affected vertebra.

  • Vertebral Removal: The surgeon removes the damaged vertebral body along with the discs directly above and below it.

  • Reconstruction: To fill the resulting gap, the "anterior column" is rebuilt using a graft or a specialized expandable cage.

  • Stabilization: Metal plates and screws are attached to the remaining vertebrae to hold the reconstruction in place while the bones fuse.

  • Fasting: Patients must fast for 8–12 hours prior to the procedure.

  • Medical Clearances: Extensive blood tests, ECG, and chest X-rays are required to assess fitness for major surgery.

  • Medication Review: Guidance from the cardiology or surgical team on adjusting medications that may affect bleeding or healing.

  • Recovery Planning: Arranging for significant post-operative support and home modifications for the initial recovery phase.

  • MRI Scan: Essential for visualizing spinal cord compression and soft tissue involvement.

  • CT Scan: Provides detailed mapping of the bony structures and the extent of vertebral damage.

  • X-rays: Used to evaluate overall spinal alignment and stability.

  • Cardiac Catheterization or Stress Test: May be required for older patients or those with high-risk factors to measure heart health before major surgery.

  • Hospital Stay: Typically requires 1 to 3 days, though complex lumbar cases may stay longer.

  • Initial Restrictions: Patients often wear a cervical collar or back brace for 4 to 8 weeks to protect the fusion site.

  • Activity: Desk work and light daily activities can often be resumed within 3 to 6 weeks.

  • Long-term Healing: Complete bony fusion between the graft and the vertebrae typically takes 6 months to 1 year.

  • Spinal Cord Protection: Stops the progression of neurological damage and protects the lungs and body from further disability.

  • Structural Stability: Restores the integrity of the spinal column following trauma or tumor-related destruction.

  • Long-term Cure: Provides a definitive treatment for complex bone-related nerve compression with high success rates.

  • Functional Improvement: Significant improvement in coordination, strength, and overall physical stamina.

Microdiscectomy Surgery

In 2026, a Microdiscectomy (also called microdecompression) is the gold-standard surgical procedure for treating a herniated lumbar disc that is pressing on a spinal nerve. Unlike a traditional discectomy, this version uses high-powered magnification—either a microscope or an endoscope—to allow the surgeon to work through a very small incision.

  • Sciatica: Sharp, "electric" radiating leg pain caused by nerve root compression.

  • Herniated Lumbar Disc: When the inner "jelly-like" material of a disc leaks out and pinches a spinal nerve.

  • Neurological Deficits: Numbness, tingling, or weakness in the legs or feet.

  • Failure of Conservative Treatment: When physical therapy, epidural injections, and medications fail to provide relief after 6–12 weeks.

  • Severe Nerve Impingement: Evidence of significant pressure on the nerve root as confirmed by advanced imaging.

  • Micro-Decompression: Using high-powered microscopes to visualize and treat the spine through a 1–2 cm incision.

  • Endoscopic Discectomy: A ultra-minimally invasive approach using a camera-equipped tube to reach the herniated fragment.

  • Muscle Preservation: Utilizing tubular dilators to stretch back muscles apart rather than cutting them away from the bone.

  • Disc Annular Repair: Using specialized biological glues or closure devices to "plug" the hole in the outer disc rim.

  • Laminotomy: The removal of a tiny piece of the overlying bone to safely reach the spinal canal and nerve root.

  • Anesthesia: The procedure is performed under general anesthesia to ensure the patient remains perfectly still and comfortable.

  • Precision Access: A 1 to 2-centimeter incision is made directly over the affected disc level.

  • Nerve Retraction: The surgeon carefully moves the nerve root aside to access the disc space.

  • Fragment Removal: Only the "damaged" protruding part of the disc is removed, leaving the healthy portion to provide cushioning.

  • Annular Closure: Modern 2026 techniques may include sealing the disc wall to significantly reduce the risk of re-herniation.

  • Fasting: Patients must follow strict fasting protocols for 8–12 hours prior to surgery.

  • Imaging Review: A final review of high-resolution MRI scans to confirm the exact location of the herniation.

  • Medical Clearance: Blood tests and an ECG are conducted to ensure the patient is a safe candidate for anesthesia.

  • Medication Adjustment: Pausing anti-inflammatory or blood-thinning medications as directed by the surgical team.

  • Recovery Support: Arranging for a support person to drive the patient home after the same-day procedure.

  • Lumbar MRI: The definitive imaging tool to visualize the disc herniation and nerve compression.

  • CT Scan: Occasionally used to assess the bone structure surrounding the herniated disc.

  • Electromyography (EMG): To measure the electrical activity of muscles and the extent of nerve damage.

  • ECG: To monitor the heart's electrical rhythm as part of the standard pre-surgical screening.

  • Physical Examination: Assessing muscle strength, reflexes, and sensation in the lower extremities.

  • Hospital Stay: Almost always an outpatient procedure in 2026, with most patients returning home within 3–5 hours.

  • Immediate Relief: Radiating leg pain often disappears immediately upon waking from surgery.

  • The "No BLT" Rule: For six weeks, patients must strictly avoid Bending, Lifting (over 2kg), or Twisting.

  • Activity Resumption: Light walking is encouraged immediately; sedentary work can typically be resumed in 1–2 weeks.

  • Long-term Care: Post-operative physical therapy often focuses on core strengthening to protect the spine.

  • High Success Rate: Offers a 90% to 95% success rate for the immediate relief of radiating leg pain.

  • Minimally Invasive: The tiny 1–2 cm incision results in minimal scarring and reduced surgical trauma.

  • Rapid Recovery: Outpatient nature allows patients to recover in the comfort of their own homes.

  • Nerve Protection: Prevents further decline and permanent damage to the compressed nerve roots.

  • Innovative Sealing: 2026 annular repair technologies significantly lower the risk of future re-herniation.

Scoliosis Correction Surgery

Scoliosis Correction Surgery is a major reconstructive procedure used to treat an abnormal sideways curvature of the spine. The latest 2026 surgical standards focus on maximizing the degree of correction while utilizing motion-preserving technologies and advanced safety monitoring to ensure optimal patient outcomes.
Surgery is typically recommended when the spinal curve is progressive or has reached a severity that impacts physical health. Indications include:

  • Significant Curvature: Sideways curves generally exceeding 45 to 50 degrees.

  • Respiratory/Cardiac Impact: Severe curves that compress the lungs or heart, affecting breathing and stamina.

  • Visible Deformity: Significant rib humps, uneven shoulders, or a tilted pelvis that affects balance and gait.

  • Failed Conservative Treatment: When bracing or physical therapy has failed to stop the progression of the curve.

  • Spinal Fusion: The most established method, using bone grafts, metal rods, and pedicle screws to hold the spine straight while the vertebrae grow together.

  • Vertebral Body Tethering (VBT): A modern, motion-preserving option for growing patients that uses a flexible cord to guide the spine's growth into alignment.

  • Magnetically Controlled Growing Rods (MAGEC): Designed for young children, these rods are lengthened periodically using an external magnet, eliminating the need for repeat surgeries.

  • Posterior Spinal Instrumentation: A technique focused on the back of the spine to provide maximum stabilization and rotational correction.

  • Surgical Access: The surgeon makes an incision along the midline of the back (or side for VBT) to reach the affected vertebral segments.

  • Curve Realignment: Using rods and screws, the surgeon carefully maneuvers the vertebrae to reduce the sideways curve and correct any rotation.

  • Bone Grafting: For fusion cases, the surface of the vertebrae is prepared and bone graft material is added to facilitate the permanent joining of the bones.

  • Safety Monitoring: Throughout the procedure, real-time neuromonitoring tracks nerve signals to ensure the spinal cord is protected during the straightening process.

  • Fasting: Patients are required to fast for 8–12 hours before the surgery.

  • Medical Clearances: Extensive blood work, ECG, and pulmonary function tests are performed to ensure the heart and lungs are healthy for anesthesia.

  • Blood Preparation: Use of "cell saver" technology is planned to collect and recycle the patient's own blood during the procedure.

  • Medication Review: Discussing all supplements and medications with the surgical team to minimize bleeding risks.

  • Full-Spine X-rays: Taken while standing and bending to measure the "Cobb angle" and determine the flexibility of the curve.

  • MRI Scan: Used to rule out any underlying spinal cord abnormalities or syrinx before the correction.

  • CT Scan (3D): Provides a high-resolution map of the vertebrae for use with intraoperative "GPS" navigation systems.

  • Pulmonary Function Test (PFT): Measures lung capacity to assess the impact of the scoliosis on the respiratory system.

  • Hospital Stay: Typically involves a stay of 3 to 5 days, with mobilization (walking) starting as early as the first day post-op.

  • Short-Term Recovery: Most patients return to school or sedentary work within 3 to 4 weeks.

  • Activity Timeline: Light exercise like walking is encouraged at 6 weeks; swimming and jogging are typically permitted between 3 to 6 months.

  • Long-Term Outlook: Full bone fusion is usually achieved at the 1-year mark, allowing a return to most non-contact sports and normal activities.

  • Curvature Reduction: Significantly flattens the sideways curve and corrects the rotational "rib hump."

  • Prevention of Progression: Stops the spine from curving further, protecting long-term heart and lung function.

  • Restored Body Balance: Realigns the head and shoulders over the pelvis, improving posture and reducing muscle strain.

  • Improved Quality of Life: Provides a long-term solution that allows patients to lead active, healthy lives without the limitations of a severe spinal deformity.

Brain Tumor Removal (Craniotomy)

A craniotomy is the primary surgical procedure used to remove a brain tumor. It involves carefully removing a section of the skull, known as a "bone flap," to provide the surgeon direct access to the brain. Once the tumor is addressed, the bone flap is typically replaced and secured with small titanium plates and screws. This procedure is the cornerstone of neurosurgical oncology, allowing for both the removal of the mass and the acquisition of tissue for a precise diagnosis.

  • Primary Brain Tumors: For tumors that originate in the brain, such as gliomas or meningiomas, where removal can reduce pressure and slow progression.

  • Metastatic Tumors: When cancer from another part of the body has spread to the brain and is causing neurological symptoms or is surgically accessible.

  • Diagnostic Biopsy: When a tumor's type is unknown, a craniotomy allows for a larger tissue sample than a needle biopsy, leading to a more accurate treatment plan.

  • Intracranial Pressure Relief: To alleviate the "mass effect" caused by a tumor that is compressing healthy brain tissue, which can cause severe headaches, nausea, or vision loss.

  • Symptom Management: To stop or reduce seizures and focal neurological deficits (like weakness or speech issues) caused by the tumor’s location.

  • Mapping: Surgeons use Neuronavigation—a high-tech system similar to GPS for the brain—and pre-operative MRI scans to pinpoint the tumor's exact coordinates before making an incision.

  • Anesthesia: The surgery is performed under general anesthesia and can take anywhere from 3 to 7 hours depending on the tumor's location and complexity.

  • The Opening: A precise incision is made in the scalp, and a specialized surgical drill (craniotome) is used to remove a piece of the skull.

  • Tumor Removal (Resection):
    Gross Total Resection: The surgeon removes the entire visible tumor.
    Subtotal Resection: If the tumor is too close to critical areas (eloquent brain) controlling speech or movement, only a portion is removed to preserve function.

  • Advanced Tools: Surgeons may use an ultrasonic aspirator to break up the tumor or fluorescent dye (5-ALA), which makes tumor cells glow under a special light to help distinguish them from healthy tissue.

  • Closing: After the tumor is removed, the bone flap is put back in its original position, and the scalp is closed with stitches or surgical staples.

  • Awake Craniotomy: The patient is woken up during the middle of surgery to perform tasks like talking or moving fingers. This allows the surgeon to map and avoid "eloquent" areas responsible for speech or motor skills in real-time.

  • Endoscopic Craniotomy: A minimally invasive approach using a small hole and a camera (endoscope), often used for tumors located in the ventricles or deep within the brain.

  • Keyhole Craniotomy: A smaller, more targeted opening (often behind the ear or above the eyebrow) used to access specific areas with minimal disruption to surrounding tissue.

  • High-Resolution Imaging: Detailed MRI or CT scans with contrast to map the tumor’s size, vascularity, and relationship to functional brain zones.

  • Steroid Protocol: You may be started on medications like dexamethasone a few days before surgery to reduce brain swelling (edema) caused by the tumor.

  • Anti-Seizure Medication: Often prescribed preventatively to reduce the risk of a seizure during or after the procedure.

  • Fasting: Adhering to "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Scalp Preparation: The surgical area may be washed with a specialized antiseptic, and a small amount of hair may be trimmed along the incision line.

  • Functional MRI (fMRI): To identify specific areas of the brain used for speech, movement, and sensation relative to the tumor.

  • Diffusion Tensor Imaging (DTI): A specialized MRI that maps the white matter "wiring" of the brain to help the surgeon avoid critical pathways.

  • Blood Panels: A routine check of your blood count, electrolytes, and clotting factors to ensure a safe surgical experience.

  • ECG: A standard heart check to confirm cardiovascular stability for a multi-hour procedure.

  • Hospital Stay: Typically 3 to 7 days. You will likely spend the first night in the Neuro-ICU for intensive monitoring of your neurological status.

  • Initial Symptoms: It is common to experience headaches, fatigue, and "brain fog." You may also notice temporary swelling around the eyes or scalp.

  • Activity Restrictions: No heavy lifting or strenuous exercise for 6 to 8 weeks. Most patients can return to light desk work within 4–6 weeks.

  • Stitch Removal: Scalp stitches or staples are typically removed by the surgical team 10–14 days after the procedure.

  • Follow-up Treatment: Depending on the biopsy results (pathology), further treatments such as radiation or chemotherapy may begin a few weeks after the brain has had time to heal.

  • Maximum Safe Resection: The combination of neuronavigation and intraoperative mapping allows surgeons to remove the largest amount of tumor possible while protecting your personality and physical abilities.

  • Immediate Pressure Relief: Removing the tumor mass often leads to a rapid improvement in headaches and other symptoms caused by brain compression.

  • Precision Technology: Tools like fluorescent dyes and ultrasonic aspirators allow for cleaner margins and less trauma to the surrounding healthy brain tissue.

  • Multidisciplinary Expertise: Care is coordinated between neurosurgeons, neuro-oncologists, and rehabilitation specialists to provide a comprehensive path from surgery to recovery.

  • Definitive Diagnosis: A craniotomy provides the highest quality tissue samples, ensuring that follow-up treatments (like targeted therapy) are based on the exact molecular profile of the tumor.

Glioma Surgery
Glioma Surgery

Glioma surgery is a specialized craniotomy performed to remove tumors that arise from the "gluey" supportive cells (glial cells) of the brain. Because gliomas often blend into healthy brain tissue rather than having a clear border, the surgical goal is Maximal Safe Resection—removing as much tumor as possible while preserving vital functions like speech, vision, and movement.

  • New Diagnosis: When imaging shows a suspected glioma (Grade I–IV) that requires both removal and a tissue sample for molecular diagnosis.

  • Symptom Management: To reduce the "mass effect" that causes severe headaches, personality changes, or cognitive "brain fog."

  • Seizure Control: If a glioma is irritating the brain's surface and causing frequent or uncontrolled seizures.

  • Recurrent Glioma: When a previously treated tumor shows signs of regrowth on follow-up scans and requires further debulking.

  • Increased Intracranial Pressure: To alleviate pressure that may be affecting your vision or causing nausea and vomiting.

  • Neuronavigation: Surgeons use a 3D "GPS" system mapped from your pre-operative MRI to guide their instruments in real-time with sub-millimeter precision.

  • Anesthesia: The surgery is typically performed under general anesthesia (unless an "awake" approach is required) and takes between 4 to 7 hours.

  • Fluorescence-Guided Surgery (5-ALA/Glow): You may drink a specialized solution (Gliolan) before surgery that causes high-grade glioma cells to glow pink under a specific blue light, helping the surgeon distinguish the tumor from healthy brain tissue.

  • Intraoperative Monitoring: Small electrodes track your brain’s electrical activity throughout the procedure to ensure motor and sensory pathways remain intact.

  • The Resection: The surgeon uses an ultrasonic aspirator—a tool that uses high-frequency vibrations to break up the tumor while suctioning it away—to gently remove the mass.

  • Pathology: Pieces of the tumor are sent immediately to a pathologist to confirm the tumor grade and identify specific molecular markers that guide future treatments.

  • Awake Craniotomy: If the glioma is located near the "speech center" or motor strip, you may be woken up during surgery to talk or follow commands. This ensures the surgeon can remove the tumor without touching areas responsible for your communication.

  • Intraoperative MRI (iMRI): Some advanced neurosurgical centers use an MRI scanner located directly inside the operating room to scan the brain during the surgery. This allows the surgeon to see if any hidden tumor remains before the final closing.

  • Stereotactic Biopsy: In cases where a glioma is in a very deep or "inoperable" location, a tiny needle is used to take a sample through a small burr hole for diagnosis.

  • Molecular Mapping: Advanced MRI sequences (like Spectroscopy or DTI) to understand the chemical makeup and wiring of the tumor.

  • Steroid Protocol: You will likely be started on Dexamethasone several days before surgery to reduce brain swelling (edema) caused by the glioma.

  • Anti-Seizure Medication: Most patients are prescribed preventative medication to stabilize the brain's electrical activity before the procedure.

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Hair Preparation: A small strip of hair along the incision line may be trimmed, though many modern techniques allow for minimal hair removal.

  • Contrast-Enhanced MRI: The primary tool used to define the tumor's boundaries and its relationship to major blood vessels.

  • Functional MRI (fMRI): To map exactly where your brain processes language and movement relative to the glioma.

  • Blood Panels: A routine check of your blood count, electrolytes, and clotting factors to ensure a safe surgical experience.

  • ECG: A standard heart check to confirm cardiovascular stability for a multi-hour neurosurgical procedure.

  • Hospital Stay: Typically 3 to 5 days, usually beginning with one night in the Neuro-ICU for intensive monitoring.

  • Post-Op Steroids: Continued use of Dexamethasone for several days to manage temporary brain swelling, which can sometimes cause a brief worsening of symptoms.

  • Medication Management: Most patients stay on anti-seizure medications for several weeks or months post-op to prevent "electrical storms" in the brain.

  • Recovery Timeline: Stitches or staples are removed in 10–14 days. Most patients return to light activity within 4 weeks and can resume normal routines in 6 to 8 weeks.

  • Next Steps in Care: Because gliomas can be infiltrative, surgery is often followed by Radiation and Chemotherapy (such as Temozolomide) starting 3–4 weeks after the brain has healed.

  • Maximal Safe Resection: Utilizing real-time mapping and fluorescence allows for the removal of the maximum amount of tumor while protecting your quality of life.

  • Molecularly Targeted Care: The tissue obtained during surgery allows oncologists to tailor your follow-up chemotherapy to the specific genetic profile of your tumor.

  • Minimizes "Mass Effect": Removing the bulk of the glioma provides immediate relief from the pressure and headaches associated with brain tumors.

  • Neuro-Protective Technology: Intraoperative monitoring and awake mapping ensure that the "high-rent" areas of your brain are avoided, preserving your ability to speak and move.

  • Integrated Recovery: Care is managed by a multidisciplinary team of neurosurgeons, neuro-oncologists, and therapists to provide a seamless transition from surgery to long-term management.

Meningioma Surgery
Meningioma Surgery

Meningioma surgery is a specialized craniotomy performed to remove a tumor that grows from the meninges—the protective membranes surrounding the brain and spinal cord. Because the vast majority of meningiomas are benign (Grade 1) and grow outside the brain tissue rather than infiltrating it, the primary surgical goal is usually Gross Total Resection. This involves the complete removal of the tumor and its attachment point to the dura mater to prevent the tumor from growing back.

  • Symptomatic Growth: If the tumor is causing persistent headaches, seizures, or personality changes.

  • Neurological Deficits: When the mass compresses critical structures, leading to weakness, numbness, or loss of coordination.

  • Vision or Hearing Loss: For tumors located near the skull base that press against the optic or auditory nerves.

  • Documented Growth: If follow-up MRIs show the tumor is enlarging, even if you currently have few symptoms.

  • Mass Effect: To alleviate significant pressure on the brain tissue or shift of the brain's midline structures.

  • Image Guidance: Surgeons use Neuronavigation (a 3D GPS system mapped from your pre-operative MRI) to plan the exact entry point and trajectory, minimizing disruption to healthy tissue.

  • Anesthesia: The surgery is performed under general anesthesia and typically lasts 3 to 6 hours, depending on the tumor's size and its proximity to major blood vessels or nerves.

  • The Opening: A precise scalp incision is made, and a section of the skull (bone flap) is temporarily removed to provide direct access.

  • Tumor Removal:
    Since meningiomas are often firm, the surgeon may use an ultrasonic aspirator to hollow out the center of the tumor first.
    The "shell" of the tumor is then carefully peeled away from the brain surface, sensitive nerves, and major blood vessels.

  • Dural Repair: The piece of the meninges where the tumor was originally attached is removed to ensure no microscopic cells remain. The surgeon then patches this area with a synthetic graft or tissue from your own scalp (fascia).

  • Closing: The bone flap is secured back in place with small titanium plates and screws, and the scalp is closed with stitches or surgical staples.

  • Skull Base Surgery: For tumors at the very bottom of the brain (near the eyes or ears), specialized drilling techniques are used to reach the tumor without having to move or retract the brain significantly.

  • Endoscopic Endonasal Surgery: For specific meningiomas near the optic nerves or pituitary gland, some can be removed entirely through the nose using a high-definition camera (endoscope), leaving no external scars.

  • Keyhole Craniotomy: A minimally invasive approach using a much smaller opening, often hidden in the eyebrow or behind the hairline, for specifically located tumors.

  • Contrast MRI: A high-resolution scan to map the tumor’s blood supply and its relationship to the surrounding venous sinuses.

  • Steroid Protocol: You may be started on medications like dexamethasone a few days before surgery to reduce brain swelling (edema) caused by the tumor.

  • Anti-Seizure Medication: Often prescribed preventatively to stabilize the brain's electrical activity before and after the procedure.

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Physical Exam: A thorough check-up to ensure your heart and lungs are healthy enough for a multi-hour surgery.

  • Visual Field Testing: If the tumor is near the optic nerves, a detailed eye exam is necessary to establish a baseline.

  • Audiogram: For tumors near the hearing nerves (internal auditory canal) to document current hearing levels.

  • Blood Panels: A routine check of your blood count, electrolytes, and clotting factors.

  • ECG: A standard heart check to confirm cardiovascular stability for the duration of the procedure.

  • Hospital Stay: Typically 3 to 5 days, including at least one night in the Neuro-ICU for intensive neurological monitoring.

  • Initial Symptoms: Headaches and fatigue are common. You may also have temporary swelling or bruising around the eyes or forehead for about a week.

  • Activity Restrictions: No heavy lifting, straining, or high-impact exercise for 6 weeks to allow the bone and scalp to heal properly.

  • Return to Routine: Most patients can return to driving and light desk work within 4–8 weeks, depending on their recovery progress.

  • Long-term Monitoring: Even with a complete removal, you will need periodic MRIs (initially every 6–12 months) to ensure there is no recurrence over the long term.

  • Curative Potential: For most Grade 1 meningiomas, a successful surgical resection is considered a permanent cure.

  • Preserves Brain Function: Because these tumors grow outside the brain, skilled surgeons can usually remove them with minimal impact on your cognitive or physical abilities.

  • Advanced Tools: The use of ultrasonic aspirators and micro-dissection tools allows for the safe separation of the tumor from delicate nerves and arteries.

  • Immediate Pressure Relief: Removing the mass provides instant relief from the "dragging" sensation and headaches associated with intracranial pressure.

  • Minimal Scarring: Modern surgical planning allows for incisions that are often hidden within the hairline or natural skin creases.

Pituitary Tumor Surgery (Endoscopic)

Endoscopic Pituitary Surgery, also known as Endoscopic Transsphenoidal Surgery, is a minimally invasive procedure that uses the nostrils as natural pathways to reach and remove tumors from the pituitary gland. Because it avoids large incisions and brain retraction, it typically offers a faster recovery and fewer side effects than traditional open surgery. This approach allows surgeons to access the "master gland" at the base of the brain with extreme precision.

  • Hormone-Secreting Tumors: Such as those causing Cushing’s disease (excess cortisol), acromegaly (excess growth hormone), or prolactinomas.

  • Non-Functioning Macroadenomas: Large tumors that do not produce hormones but press on the optic nerves, causing vision loss, double vision, or chronic headaches.

  • Pituitary Apoplexy: An emergency condition where a tumor bleeds or outgrows its blood supply, requiring rapid decompression.

  • Failed Medical Management: When medications are unable to sufficiently control hormone levels or stop the growth of the tumor.

  • Rathke’s Cleft Cysts: Benign fluid-filled growths that can interfere with normal gland function or cause pressure symptoms.

  • Collaborative Team: The surgery is usually a joint effort between a neurosurgeon and an Ear, Nose, and Throat (ENT) surgeon, taking about 2 to 3 hours under general anesthesia.

  • Nasal Access: The ENT surgeon inserts a thin, lighted tube with a high-definition camera (endoscope) through one nostril to navigate to the very back of the nasal cavity.

  • Opening the Sphenoid Sinus: The surgeon opens the sphenoid sinus (an air-filled space behind the nose) to reach the sella turcica, the small bony compartment that houses the pituitary gland.

  • Tumor Removal: Using specialized long instruments through the other nostril, the neurosurgeon removes the tumor in small pieces. The endoscope provides a panoramic, high-magnification view of the area, including nearby carotid arteries and optic nerves.

  • Reconstruction: If needed, a small fat graft (often taken from the abdomen) or synthetic material is used to fill the space and seal the area to prevent cerebrospinal fluid (CSF) leaks.

  • Endocrine Evaluation: Comprehensive blood and urine tests to establish your baseline hormone levels (growth hormone, ACTH, prolactin, etc.).

  • High-Resolution MRI: A dedicated "pituitary protocol" scan to map the tumor’s exact size and its relationship to the optic chiasm.

  • Ophthalmology Exam: A detailed visual field test to document any current vision loss before the surgery.

  • Nasal Assessment: An ENT evaluation to ensure your nasal passages are clear and suitable for the endoscopic approach.

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Visual Field Testing: To measure peripheral vision, which is often the first thing affected by pituitary tumors.

  • Dynamic Hormone Testing: Specialized "stimulation" or "suppression" tests to confirm the type of secreting tumor.

  • Carotid Imaging: Occasionally required if the tumor is very large and wrapping around the main arteries of the brain.

  • ECG: A standard heart check to confirm cardiovascular stability for the duration of the procedure.

  • Hospital Stay: Typically 1 to 3 days, often starting with one night in the Intensive Care Unit (ICU) for close monitoring of your fluid balance and hormone levels.

  • Immediate Symptoms: It is normal to experience nasal congestion, mild headaches, and "watery" or blood-tinged nasal drainage for 1 to 2 weeks.

  • The "No" Rules: For 4 to 6 weeks, you must strictly avoid:
    Blowing your nose: To prevent pressure buildup that could cause a CSF leak.
    Lifting and Straining: No lifting objects over 5 lbs or heavy straining, which increases intracranial pressure.
    Drinking through straws: The suction can interfere with the healing of the nasal repairs.

  • Hormone Monitoring: You will work closely with an endocrinologist to check if your gland is producing the correct amount of hormones post-op.

  • Follow-up MRI: A baseline scan is usually performed 3 months after surgery to ensure the entire tumor was removed.

  • No External Scars: By using the natural pathway of the nose, there are no visible incisions on the face or scalp.

  • Superior Visualization: The endoscope allows surgeons to "see around corners," identifying tumor tissue that might be missed with traditional microscopic surgery.

  • Rapid Vision Improvement: Decompressing the optic nerves often leads to a quick and significant improvement in peripheral vision and clarity.

  • Preserves Gland Function: The high-magnification view helps surgeons distinguish between the tumor and the healthy part of the pituitary gland.

  • Reduced Brain Trauma: Because the brain is not "moved" or retracted to reach the tumor, post-operative headaches and recovery times are greatly reduced.

Aneurysm Clipping
Aneurysm Clipping

Aneurysm clipping is a specialized neurosurgical procedure used to treat a brain aneurysm by placing a small metal clip across its "neck." This prevents blood from entering the weakened, bulging area of the artery, effectively eliminating the risk of a life-threatening rupture or re-bleeding. Unlike endovascular coiling, which treats the aneurysm from the inside, clipping is an open surgical approach that provides a definitive, mechanical seal.

  • Ruptured Aneurysm: Performed as an emergency procedure to stop a subarachnoid hemorrhage (brain bleed) and prevent a second, often fatal, rupture.

  • Large Unruptured Aneurysms: A preventative measure for aneurysms that are growing or have reached a size where the risk of bursting outweighs the risk of surgery.

  • Complex Aneurysm Shape: For wide-necked or irregular aneurysms that may not be suitable for endovascular coiling.

  • Younger Patients: Clipping is often favored for younger patients as it typically offers a highly durable, lifelong solution with a very low rate of recurrence.

  • Mass Effect: When a large aneurysm is pressing on nearby cranial nerves, causing symptoms like double vision or facial pain.

  • Craniotomy: A precise incision is made in the scalp, usually behind the hairline. A small section of the skull (bone flap) is temporarily removed to provide the surgeon access to the brain's protective layers.

  • Anesthesia: The surgery is performed under general anesthesia and typically lasts 3 to 5 hours, depending on the aneurysm's location.

  • Microdissection: Using a high-powered operating microscope, the neurosurgeon carefully navigates the natural folds and fluid-filled spaces of the brain to locate the aneurysm without disturbing healthy tissue.

  • Clip Application: A tiny, permanent titanium clip is placed precisely across the neck of the aneurysm. This seals the bulge while allowing blood to flow normally through the main (parent) artery.

  • Flow Verification: Surgeons often use intraoperative fluorescence (ICG dye) or micro-Doppler ultrasound to confirm the aneurysm is completely closed and that all surrounding vessels remain open and healthy.

  • Closure: The bone flap is secured back in place with small titanium plates and screws, and the scalp is closed with stitches or surgical staples.

  • Cerebral Angiography: The "gold standard" diagnostic test to map the exact size, shape, and orientation of the aneurysm relative to other blood vessels.

  • Neurological Assessment: A detailed baseline exam of your motor skills, speech, and vision.

  • Steroid/Anti-Seizure Protocol: In some cases, medications are started before surgery to reduce brain irritation or the risk of a seizure.

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Medication Audit: You will be asked to stop taking blood thinners or anti-inflammatory medications (like aspirin or ibuprofen) several days before the procedure.

  • CTA or MRA Scan: High-resolution 3D imaging used to plan the surgical trajectory and identify the best "angle" for clip placement.

  • Blood Panels: A routine check of your blood count, electrolytes, and clotting factors to ensure a safe surgical experience.

  • ECG and Chest X-ray: Standard checks to confirm your heart and lungs are healthy enough for a multi-hour neurosurgical procedure.

  • Cerebrospinal Fluid (CSF) Analysis: For ruptured cases, this helps determine the extent of the initial bleed.

  • Hospital Stay: Patients with unruptured aneurysms typically stay 2 to 5 days. For ruptured cases, the stay often extends to 2 to 3 weeks in a specialized Neuro-ICU for intensive monitoring.

  • Initial Symptoms: Headaches, fatigue, and "clicking" or "popping" sensations in the scalp are common as the bone flap heals.

  • Activity Restrictions: No heavy lifting, straining, or vigorous exercise for 6 to 8 weeks. Most patients can return to driving and light desk work within one month.

  • Follow-up Imaging: While the clip is a permanent solution, periodic imaging (MRA or CTA) is performed to monitor the surgical site and ensure no new aneurysms develop.

  • Vasospasm Monitoring: For those who experienced a rupture, the team will monitor closely for "vasospasm" (narrowing of brain vessels) for up to 14 days following the initial bleed.

  • Definitive Mechanical Seal: Once clipped, the risk of the aneurysm ever bleeding again is extremely low, providing long-term peace of mind.

  • Preserves Parent Artery: Advanced micro-surgical techniques ensure that the "hammock" of the clip seals the bulge while maintaining 100% of the normal blood flow to the brain.

  • Real-Time Verification: Intraoperative dye (ICG) allows the surgeon to see blood flow through the vessels in real-time, ensuring the clip is perfectly positioned before the surgery ends.

  • Durability: Titanium clips are MRI-safe and designed to stay in place for a lifetime without needing adjustment or replacement.

  • Addresses Complex Cases: Surgery remains the gold standard for aneurysms that are technically difficult to treat via the "inside" catheter-based methods.

AVM Brain Surgery
AVM Brain Surgery

AVM (Arteriovenous Malformation) surgery, clinically known as surgical resection, is a major neurosurgical procedure to physically remove an abnormal tangle of blood vessels from the brain or spinal cord. The primary goal is to eliminate the risk of a life-threatening brain hemorrhage. Unlike other treatments that may take years to work, surgical resection provides an immediate and definitive "cure" by removing the malformation entirely in a single session.

  • Preventing Hemorrhage: AVMs carry a 2–4% annual risk of bursting; surgery is often the most definitive way to permanently eliminate this risk.

  • Ruptured AVM: Performed as an emergency to remove the malformation and any resulting blood clot (hematoma) to relieve life-threatening pressure on the brain.

  • Seizure Control: If the AVM is irritating the brain's surface and causing frequent seizures that are difficult to manage with medication.

  • Accessible Location: Surgery is highly effective for AVMs located on or near the surface of the brain where they can be reached without disturbing deep, critical structures.

  • Vascular Steal Syndrome: When the AVM "steals" blood from healthy surrounding brain tissue, leading to progressive neurological weakness or cognitive decline.

  • Craniotomy: The surgeon makes a precise incision in the scalp, usually behind the hairline, and temporarily removes a small section of the skull (bone flap) to access the brain.

  • Anesthesia: The surgery is performed under general anesthesia and typically lasts 4 to 8 hours depending on the size and complexity of the AVM.

  • Microdissection: Using a high-powered operating microscope, the neurosurgeon carefully separates the AVM from the surrounding healthy brain tissue with sub-millimeter precision.

  • Vessel Ligation: The "feeding" arteries that bring high-pressure blood into the AVM are identified and closed with tiny permanent clips or cautery. The "draining" veins are left for last to ensure blood does not back up and cause a rupture during the procedure.

  • Resection: Once the blood supply is completely cut off, the entire malformed tangle is lifted out of the brain cavity.

  • Closing: After confirming there is no remaining bleeding, the bone flap is replaced and secured with small titanium plates, and the scalp is closed with stitches or surgical staples.

  • Digital Subtraction Angiography (DSA): A detailed "road map" of the brain's blood vessels to identify every feeding artery and draining vein.

  • Functional MRI (fMRI): To map critical areas of the brain near the AVM responsible for speech, movement, or vision.

  • Pre-Surgical Embolization: In some cases, a catheter procedure is done a day or two before surgery to "glue" some of the vessels, making the final resection safer and reducing blood loss.

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Anti-Seizure Medication: Often started before the procedure to stabilize the brain's electrical activity.

  • CT and MRI Scans: To provide a 3D view of the AVM's volume and its exact relationship to the surrounding healthy brain tissue.

  • Diffusion Tensor Imaging (DTI): A specialized MRI that shows the white matter "wiring" near the AVM to help the surgeon avoid important pathways.

  • Blood Panels: A routine check of your blood count, electrolytes, and clotting factors to ensure a safe surgical experience.

  • ECG: A standard heart check to confirm cardiovascular stability for a multi-hour neurosurgical procedure.

  • Hospital Stay: Typically 3 to 7 days. For a ruptured AVM, the stay may extend to 2 or 3 weeks in a specialized Neuro-ICU for intensive recovery.

  • Initial Symptoms: Headaches, fatigue, and "brain fog" are common for the first few weeks. Some patients may also experience temporary scalp numbness or "clicking" sensations as the bone flap heals.

  • Activity Restrictions: No heavy lifting, straining, or vigorous exercise for 6 to 8 weeks. Most patients can return to light work or school within 1–2 months.

  • Final Confirmation: A follow-up angiogram is usually performed before discharge or a few months later to prove the AVM is 100% gone.

  • Rehabilitation: If the AVM was in a functional area, physical or occupational therapy may be recommended to help regain strength or coordination.

  • Immediate Risk Elimination: Once the AVM is removed, the risk of a future brain hemorrhage is effectively reduced to zero.

  • Definitive Cure: Unlike radiation therapy, which can take 2–3 years to close an AVM, surgical resection provides an instant resolution.

  • Advanced Micro-Neurosurgery: The use of high-definition microscopes and neuronavigation allows surgeons to navigate the brain's natural folds with minimal impact on healthy tissue.

  • Reduces Brain Irritation: Removing the physical tangle of vessels often leads to a significant reduction in chronic headaches and seizure activity.

  • Integrated Care Teams: Patients benefit from a multidisciplinary team including neurosurgeons, interventional neuroradiologists, and specialized nurses to manage every stage of the journey.

Endoscopic Skull Base Surgery

Endoscopic Skull Base Surgery is a minimally invasive technique used to reach tumors and abnormalities at the very bottom of the brain and the top of the spine. Instead of utilizing large incisions or traditional "open" craniotomies, surgeons use the nose and sinuses as natural corridors to reach the target area. This advanced approach allows for the treatment of complex conditions located deep within the head without the need to retract or move the brain.

  • Pituitary Adenomas: The most common use for this approach, particularly for tumors affecting hormone levels or vision.

  • Meningiomas & Chordomas: Tumors located at the base of the skull that would otherwise require highly invasive open surgery.

  • Craniopharyngiomas: Complex tumors located near the pituitary gland and optic nerves.

  • CSF Leaks: Repairing physical holes in the skull base where brain fluid is dripping from the nose.

  • Acoustic Neuromas: Certain tumors affecting the nerves responsible for balance and hearing.

  • Esthesioneuroblastoma: Rare tumors arising from the olfactory (smell) nerves at the roof of the nose.

  • Team Effort: The surgery is typically a collaborative effort between a Neurosurgeon and an ENT (Otolaryngologist), performed under general anesthesia over 3 to 7 hours.

  • Nasal Access: The ENT surgeon inserts a high-definition endoscope (a thin tube with a camera) through the nostrils. No external skin incisions are made on the face or scalp.

  • Navigation: Using a 3D "GPS" system mapped from your pre-operative MRI, the surgeons navigate through the sphenoid or ethmoid sinuses to reach the skull base bone.

  • Bone Opening: A small, precise window is created in the thin bone at the base of the skull to expose the protective lining of the brain (dura) or the tumor itself.

  • Tumor Removal: Using long, specialized micro-instruments through the other nostril, the tumor is removed in sections. The endoscope provides a close-up, panoramic view of critical structures like the optic nerves and carotid arteries.

  • Reconstruction: To prevent brain fluid leaks, the surgical opening is sealed using a nasoseptal flap (a flap of your own nasal tissue with its own blood supply), fat grafts, or specialized synthetic glues.

  • High-Resolution Imaging: Dedicated skull base MRI and CT scans to map the bone anatomy and vascular structures.

  • Endocrine Testing: Comprehensive blood panels to check pituitary hormone function before the gland is approached.

  • Ophthalmology Review: Detailed visual field and acuity testing if the tumor is near the optic nerves.

  • Nasal Endoscopy: A quick office-based look at your nasal passages to ensure there are no obstructions like polyps or a severely deviated septum.

  • Fasting: Adhering to "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • CT Navigation Scan: A specialized scan used to "sync" your anatomy with the surgical GPS system in the operating room.

  • Visual Field Test: To establish a baseline for your peripheral vision, which is often improved by the surgery.

  • Blood Panels: A routine check of your blood count, electrolytes, and clotting factors.

  • ECG: A standard heart check to confirm cardiovascular stability for a multi-hour procedure.

  • Hospital Stay: Typically 2 to 4 days, with the first night often spent in the Neuro-ICU for intensive monitoring.

  • Immediate Symptoms: Nasal congestion, "crusting" inside the nose, and mild headaches are normal for 2 to 3 weeks as the sinuses heal.

  • Nasal Care: You will need to perform frequent saline nasal rinses to keep the surgical area clean and moist.

  • The "No" Rules (4–6 Weeks): To protect the internal seal and prevent a CSF leak, you must strictly avoid:
    Blowing your nose: This can force air into the brain cavity.
    Straining: Stool softeners are usually prescribed to prevent internal pressure.
    Heavy lifting: Nothing over 5 kg (11 lbs).
    Drinking through a straw: The suction pressure can disrupt the nasal flap.

  • Long-term Follow-up: Regular nasal debridement (cleaning) by your ENT and follow-up MRIs are required to monitor healing and ensure no tumor recurrence.

  • No Visible Scars: By using the nose as a natural corridor, there are no incisions on the face, preserving your natural appearance.

  • Faster Recovery: Avoiding a traditional craniotomy means significantly less post-operative pain and a quicker return to daily activities.

  • Panoramic Visualization: The endoscope allows surgeons to see "around the corner" of critical nerves and arteries with better clarity than a traditional microscope.

  • Brain-Sparing Technique: Because the approach is from underneath the brain, there is no need for brain retraction, reducing the risk of post-operative swelling or cognitive changes.

  • Highly Precise Reconstruction: The use of vascularized nasoseptal flaps has revolutionized the success rate of sealing the skull base, making the procedure safer than ever before.

Acoustic Neuroma Surgery

Acoustic neuroma surgery (vestibular schwannoma resection) is a specialized craniotomy performed to remove a benign tumor growing on the hearing and balance nerves. Because these tumors are located in the cerebellopontine angle—a crowded space near the brainstem—the primary goal is to remove the tumor while preserving the facial nerve and, if possible, any remaining hearing. This surgery requires extreme precision to protect the delicate structures that control facial movement and balance.

  • Documented Growth: If follow-up MRI scans show the tumor is enlarging, increasing the risk of future nerve damage.

  • Brainstem Compression: Large tumors that press against the brainstem can become life-threatening and require surgical decompression.

  • Progressive Hearing Loss: When a tumor is still small enough that a hearing-preservation surgical approach is a viable option.

  • Balance Instability: Persistent vertigo or dizziness caused by the tumor’s pressure on the vestibular (balance) nerve.

  • Facial Twitching or Numbness: Signs that the tumor is beginning to impact the adjacent facial or trigeminal nerves.

  • Anesthesia: The surgery is performed under general anesthesia and typically lasts 4 to 10 hours, depending on the tumor's size and the chosen surgical approach.

  • Intraoperative Monitoring: Small electrodes are placed on the face and near the ear to provide real-time nerve monitoring. This provides the surgeon with immediate feedback if the facial or hearing nerves are being stressed.

  • Surgical Approaches:
    Translabyrinthine: The surgeon reaches the tumor through the inner ear bone (mastoid). This provides the best view of the facial nerve but results in permanent, total hearing loss in that ear.
    Retrosigmoid (Sub-occipital): An incision is made behind the ear to reach the tumor from behind. This offers a chance to preserve existing hearing.
    Middle Fossa: An opening is made above the ear, used primarily for very small tumors when the primary goal is to save hearing.

  • Tumor Removal: Using a high-powered microscope and an ultrasonic aspirator, the surgeon meticulously peels the tumor away from the brainstem and cranial nerves.

  • Fat Graft: If the inner ear was opened, a small piece of fat (usually taken from the abdomen) is used to seal the area and prevent cerebrospinal fluid (CSF) leaks.

  • Closing: The bone flap is replaced or the opening is covered with a titanium mesh or plate, and the scalp is closed with stitches.

  • High-Resolution MRI: A dedicated "internal auditory canal" protocol scan to map the tumor’s exact relationship to the nerves.

  • Audiogram and ABR: Detailed hearing tests to establish your baseline hearing level and the health of the auditory nerve.

  • Vestibular Testing: To evaluate how much your balance system has already been affected by the tumor.

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Medication Audit: You may be asked to stop taking blood thinners or anti-inflammatory medications several days before the procedure.

  • Contrast-Enhanced CT Scan: To provide a detailed map of the bone structures surrounding the inner ear and skull base.

  • Videonystagmography (VNG): A specialized test to record eye movements and determine the extent of balance nerve involvement.

  • Blood Panels: A routine check of your blood count, electrolytes, and clotting factors.

  • ECG: A standard heart check to confirm cardiovascular stability for a multi-hour neurosurgical procedure.

  • Hospital Stay: Typically 3 to 5 days, usually including at least one night in the Neuro-ICU for intensive monitoring.

  • Balance and Vertigo: Since the balance nerve is often removed with the tumor, significant dizziness and vertigo are common for the first few days. The brain usually adapts within a few weeks through "vestibular compensation."

  • Activity Restrictions: No heavy lifting or straining for 6 weeks. Most patients return to professional work within 6–12 weeks.

  • Vestibular Rehabilitation: Specialized balance therapy is often started shortly after surgery to speed up the brain's ability to compensate for the lost balance nerve.

  • Facial Nerve Recovery: If the facial nerve was stretched during surgery, temporary facial drooping may occur; specialized facial exercises and eye care (drops/gels) are necessary during the recovery phase.

  • Advanced Nerve Monitoring: The use of real-time electrical feedback significantly increases the chances of preserving the facial nerve and maintaining your natural appearance.

  • Tailored Surgical Approaches: Surgeons can choose the specific "pathway" to the tumor that best balances tumor removal with the goal of hearing preservation.

  • Microsurgical Precision: Utilizing high-definition operating microscopes allows for the safe separation of the tumor from the delicate brainstem surface.

  • Multidisciplinary Expertise: Care is coordinated between neurosurgeons and neuro-otologists (ear specialists) to manage both the neurological and hearing aspects of the condition.

  • Long-Term Tumor Control: For most benign vestibular schwannomas, a complete surgical resection provides a permanent cure with a very low risk of recurrence.

Brainstem Surgery
Brainstem Surgery

Brainstem surgery is one of the most complex and delicate procedures in neurosurgery. The brainstem controls vital life functions—including breathing, heart rate, and consciousness—and acts as the "highway" for all nerve signals traveling between the brain and the body. Because the brainstem is packed with critical nuclei and fiber tracts in a very small space, the surgical goal is usually Maximal Safe Resection or decompression while strictly avoiding these "high-rent" areas.

  • Focal Brainstem Gliomas: Specific types of tumors that can be safely separated from the surrounding healthy brainstem tissue.

  • Cavernous Malformations (Cavernomas): Small clusters of abnormal blood vessels that have bled or pose a high risk of future hemorrhage within the brainstem.

  • Brainstem Hemangioblastomas: Highly vascular tumors, often associated with Von Hippel-Lindau disease, that cause progressive pressure.

  • Symptomatic Cysts or Abscesses: Collections of fluid or infection that are causing life-threatening pressure on the body's respiratory or cardiac centers.

  • Tectal Plate Tumors: Lesions located in the back of the midbrain that can block the flow of cerebrospinal fluid, causing hydrocephalus.

  • Anesthesia: The surgery is performed under general anesthesia and typically lasts 6 to 10 hours due to the extreme precision required.

  • Surgical Approaches: The entry point is tailored to the exact location of the lesion:
    Suboccipital/Telovelar: Accessing the back of the brainstem (medulla or pons) through an incision at the very base of the skull.
    Retrosigmoid: Reaching the side of the brainstem, often used for issues near the cranial nerves.
    Endoscopic Endonasal: For specific lesions at the very front of the brainstem, surgeons may access the area through the nose.

  • Intraoperative Neuromonitoring (IONM): This is the most critical safety feature. Electrodes continuously monitor motor pathways, sensory pathways, and cranial nerves (eye movement, swallowing, and facial sensation) to warn the surgeon if they are near vital tissue.

  • Microsurgical Dissection: Using a high-powered microscope and specialized lasers or ultrasonic aspirators, the surgeon removes the lesion through "safe entry zones"—specific areas where the density of critical nerve fibers is lowest.

  • Closing: After ensuring all bleeding is controlled, the skull opening is meticulously closed with titanium plates or mesh, and the scalp is stitched.

  • Advanced Neuroimaging: Utilizing specialized MRI sequences like Tractography (DTI) to map the exact location of the "wiring" inside your brainstem.

  • Steroid Protocol: You will likely be started on high doses of Dexamethasone before surgery to minimize brainstem swelling (edema).

  • Neurological Baseline: A comprehensive assessment of your current motor strength, coordination, and cranial nerve function (swallowing, vision, facial movement).

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • Medication Audit: You must stop all blood thinners and anti-inflammatory medications several days before the procedure to prevent bleeding.

  • Brainstem Auditory Evoked Response (BAER): To check the integrity of the hearing pathways through the brainstem.

  • Somatosensory Evoked Potentials (SSEP): To monitor the sensory pathways that travel from your limbs to your brain.

  • Cerebrospinal Fluid (CSF) Study: To rule out active infection or check for specific tumor markers if the diagnosis is unclear.

  • ECG and Chest X-ray: Standard checks to ensure your heart and lungs can handle a long, intensive surgical procedure.

  • Hospital Stay: Typically 7 to 14 days. Most patients spend the first several days in a specialized Neuro-ICU for intensive monitoring of breathing and heart rate.

  • Initial Symptoms: Temporary "cranial nerve palsies" (double vision, facial numbness, or swallowing difficulty) are common as the brainstem heals from surgical manipulation.

  • Post-Op Steroids: Continued use of Dexamethasone is essential to manage swelling within the tight confines of the skull base.

  • Inpatient Rehabilitation: Most patients transition to specialized physical, occupational, and speech therapy for several weeks to regain coordination and strength.

  • Long-term Monitoring: Regular MRI scans and neurological check-ups are mandatory to monitor healing and ensure no recurrence of the lesion.

  • Protects Vital Functions: The use of real-time IONM monitoring provides an unparalleled safety net, allowing surgeons to stop immediately if vital pathways are at risk.

  • Targeted "Safe Zones": Advanced anatomical knowledge allows surgeons to enter the brainstem through areas that do not contain critical nerve centers, preserving your quality of life.

  • Immediate Decompression: For lesions causing pressure, surgery provides the fastest way to relieve strain on the centers that control breathing and heart rate.

  • Precision Technology: Ultrasonic aspirators allow for the gentle removal of tumor tissue without the "pulling" or "tugging" that can damage delicate brainstem fibers.

  • Multidisciplinary ICU Care: Recovery is managed by a team of neuro-intensivists and specialized nurses trained specifically to handle the unique needs of brainstem surgery patients.

Endoscopic Endonasal Surgery

Endoscopic Endonasal Surgery (EES) is a minimally invasive surgical technique that uses the nose and sinuses as natural "corridors" to reach and treat conditions at the base of the brain or the top of the spine. Unlike traditional "open" brain surgery, it requires no external incisions on the face or scalp and avoids the need to remove large parts of the skull. This advanced approach allows surgeons to access deep-seated tumors and vascular issues with minimal disruption to healthy brain tissue.

  • Pituitary Tumors: This is the primary and most common use for EES, particularly for adenomas affecting hormone levels or vision.

  • Skull Base Tumors: Including meningiomas, chordomas, and craniopharyngiomas located at the very bottom of the brain.

  • Cerebrospinal Fluid (CSF) Leaks: To repair physical holes or defects in the skull base where brain fluid is dripping through the nose.

  • Optic Nerve Compression: To decompress nerves that are being pinched by tumors, often leading to rapid vision improvement.

  • Sinus or Nasal Malignancies: For specialized removal of tumors that have invaded the bone separating the nose from the brain.

  • Top-of-Spine Disorders: To treat abnormalities where the skull meets the spinal column without traditional neck surgery.

  • Collaborative Team: The surgery is typically a joint effort between a neurosurgeon and an ENT (Otolaryngologist), performed under general anesthesia.

  • Access: A high-definition endoscope (a thin tube with a camera) is inserted through the nostrils. This provides a panoramic, high-magnification view of the surgical field.

  • Navigation: Surgeons use an image-guided system (neuronavigation), similar to a GPS for the brain, to map the exact location of the target in real-time using your pre-operative scans.

  • Removal: Specialized long-reach micro-instruments are passed through the nostrils to remove tumors or treat the affected area without any external skin cuts.

  • Reconstruction: To prevent brain fluid leaks, the surgeon may reconstruct the surgical site using a nasoseptal flap (the patient's own nasal tissue with its own blood supply) or specialized synthetic sealants.

  • Closing: Because there are no external incisions, no stitches are needed on the face or scalp; the internal nasal passages are simply cleaned and occasionally padded with temporary sponges.

  • Skull Base MRI and CT: High-resolution scans to provide a 3D "roadmap" of your bone structure and major blood vessels.

  • Endocrine Evaluation: Comprehensive blood tests to check your current pituitary hormone levels.

  • Visual Field Testing: A detailed eye exam to establish a baseline for your vision and peripheral awareness.

  • Nasal Assessment: An ENT check-up to ensure your nasal anatomy (like the septum) is suitable for the endoscopic instruments.

  • Fasting: Following "nothing by mouth" instructions for 8 hours prior to your scheduled anesthesia.

  • CT Navigation Scan: A specialized scan performed close to the surgery date to "calibrate" the surgical GPS system.

  • Hormone Panels: Specifically checking thyroid, adrenal, and growth hormones which may be impacted by the surgery.

  • Blood Panels: A routine check of your blood count, electrolytes, and clotting factors.

  • ECG: A standard heart check to confirm cardiovascular stability for the duration of the procedure.

  • Hospital Stay: Patients typically stay in the hospital for 1 to 5 days, often spending the first night in a specialized Neuro-ICU.

  • Immediate Symptoms: It is normal to experience nasal congestion, mild headaches, and blood-tinged nasal drainage for 1 to 2 weeks.

  • Nasal Care: Regular saline nasal rinses are essential to keep the nasal passages clean, moist, and free of crusting.

  • The "No" Rules (4–6 Weeks): To protect the internal seal and prevent a brain fluid leak, you must strictly avoid:
    Blowing your nose: This can force air into the brain cavity.
    Straining: Stool softeners are often prescribed to prevent internal pressure.
    Heavy lifting: Nothing over 5–7 kg (11–15 lbs).
    Bending over at the waist: Keep your head above your heart level at all times.
  • Follow-up Debridement: You will visit your ENT specialist several times in the first month to have the nasal passages professionally cleaned (debrided).

  • No External Scars: By utilizing natural pathways, there is no impact on your facial appearance or hairline.

  • Enhanced Visualization: The endoscope allows surgeons to see "around corners" and behind critical nerves that would be hidden in traditional surgery.

  • Faster Recovery: Avoiding a craniotomy (opening the skull) significantly reduces post-operative pain and shortens the hospital stay.

  • Direct Access: EES provides the shortest, most direct route to the pituitary gland and skull base, minimizing the "travel distance" through healthy brain tissue.

  • Superior Seal Techniques: The use of vascularized nasal flaps has revolutionized the safety of this procedure, dramatically reducing the risk of post-operative infections and leaks.

Chiari Decompression

Chiari decompression is a specialized neurosurgical procedure performed to treat Chiari malformation, a condition where the cerebellum extends into the foramen magnum. In the 2026 medical landscape, this surgery focuses on restoring the natural flow of cerebrospinal fluid and relieving pressure on the brainstem. By utilizing precision bone-sparing technology and advanced intraoperative imaging, the procedure aims to halt neurological progression and eliminate chronic pain.

  • Severe headaches at the base of the skull that intensify during coughing, sneezing, or straining.

  • Chronic neck pain that radiates into the shoulders or upper back.

  • Loss of fine motor skills or frequent episodes of dizziness and imbalance.

  • Persistent numbness or a tingling sensation in the hands and feet.

  • Difficulty swallowing or frequent choking episodes caused by brainstem compression.

  • New onset of weakness in the extremities that interferes with daily mobility.

  • Type I or Type II Chiari Malformation with documented descent of the cerebellar tonsils.

  • Syringomyelia, characterized by the formation of fluid-filled cysts within the spinal cord.

  • Hydrocephalus resulting from the obstruction of cerebrospinal fluid at the base of the skull.

  • Scoliosis or spinal curvature related to abnormal fluid pressure in the spinal canal.

  • Basilar invagination or other complex craniovertebral junction abnormalities.
[Image Placeholder: A sagittal Cine-MRI view showing the cerebellar tonsils protruding through the foramen magnum and obstructing fluid flow]

  • Pre-operative 3D surgical planning using high-definition MRI to map the exact anatomy of the posterior fossa.

  • Administration of general anesthesia with continuous neuro-monitoring of the brainstem and spinal cord.

  • A small vertical incision is made at the back of the head to access the base of the skull.

  • Precise removal of a small section of the occipital bone using ultrasonic bone-cutting tools.
  • Performance of a C1 laminectomy if the cerebellar tonsils have descended past the first cervical vertebra.

  • Application of a dural graft to expand the protective lining of the brain and ensure long-term decompression.

  • Ultrasonic Piezoelectric Surgery: Using high-frequency vibrations to selectively remove bone while protecting the delicate dura and neural tissues.

  • Intraoperative Color Doppler Ultrasound: Providing real-time visualization of cerebrospinal fluid pulse waves during the procedure to confirm successful decompression.

  • Synthetic Biomimetic Dural Grafts: Utilizing 2026 bio-engineered materials that integrate seamlessly with natural tissue and reduce the risk of leaks.

  • Cine-MRI Flow Analysis: Using movie-like imaging sequences to quantify the velocity and volume of fluid movement before and after surgery.

  • Endoscopic-Assisted Decompression: Employing micro-cameras to allow for smaller incisions and improved visualization of the cerebellar tonsils.

  • Laser-Assisted Duraplasty: Using precision laser technology to seal dural grafts, significantly lowering the incidence of post-operative fluid leaks.

[Image Placeholder: A neurosurgeon utilizing an intraoperative ultrasound probe to verify fluid circulation during a decompression procedure]

  • Comprehensive baseline neurological assessment to document existing motor and sensory function.

  • Participation in a 2026 pre-surgical optimization program to manage systemic inflammation and nutrition.

  • Discontinuation of anti-platelet medications or herbal supplements that may affect blood clotting.

  • Pre-surgical imaging using advanced flow-sensitive MRI sequences to identify the primary points of obstruction.

  • Coordination with a specialized neuro-rehabilitation team to plan for post-operative recovery milestones.

  • High-resolution Cine-MRI to evaluate the dynamic movement of cerebrospinal fluid around the brainstem.

  • CT scan of the craniovertebral junction to assess bone structure and potential anatomical variants.

  • Formal swallow evaluation to determine if brainstem compression is affecting the lower cranial nerves.

  • Standard 2026 pre-operative blood panels including metabolic and hematologic screening.

  • Audiology and vestibular testing to establish a baseline for balance and coordination.

  • Success rates for headache relief in 2026 range from 80% to 90% through optimized surgical techniques.

  • Early intervention effectively prevents the expansion of a syrinx and subsequent spinal cord damage.

  • Real-time intraoperative imaging ensures that the decompression is anatomically sufficient before the patient leaves the operating room.

  • Minimally invasive bone-sparing approaches lead to reduced post-operative neck pain and faster recovery times.

  • Improved dural sealants and graft materials have nearly eliminated the historical risk of cerebrospinal fluid leaks.

  • Hospitalization for 2 to 4 days for close monitoring of neurological status and wound healing.

  • Implementation of a specialized neck-strengthening program starting 4 to 6 weeks after the procedure.

  • Short-term use of modern non-narcotic pain management protocols to address post-operative stiffness.

  • Avoidance of high-impact activities or heavy lifting for at least 8 weeks to allow the bone and dura to heal.

  • First post-operative Cine-MRI at 3 months to verify the restoration of normal fluid dynamics.

  • Significant reduction or total elimination of "tussive" headaches triggered by physical exertion.

  • Stabilization or shrinkage of spinal cord syrinxes, leading to improved sensory and motor function.

  • Regular annual monitoring with non-invasive imaging to ensure continued spinal stability.

  • Resumption of most recreational activities and professional duties with improved focus and coordination.

  • Ongoing connection with 2026 digital health platforms for symptom tracking and long-term wellness support.

Deep Brain Stimulation (DBS)

Deep Brain Stimulation (DBS) is a neurosurgical procedure that uses a "brain pacemaker" to send electrical impulses to specific areas of the brain. As of 2026, it is an established standard of care for movement disorders and is increasingly used for psychiatric conditions when traditional medications fail.

  • Parkinson’s Disease symptoms such as tremors, rigidity, and "off" time that are no longer managed by medication.

  • Essential Tremor causing severe, uncontrollable shaking in the hands and arms.

  • Dystonia involving painful or involuntary muscle contractions.

  • Epilepsy characterized by refractory partial-onset seizures.

  • Treatment-resistant Obsessive-Compulsive Disorder (OCD).

  • Parkinson’s Disease: Significantly reduces tremors and motor fluctuations.

  • Essential Tremor: Suppresses severe shaking to improve daily function.

  • Dystonia: Helps control involuntary muscle movements and postures.

  • Epilepsy: Approved as an adjunctive therapy for difficult-to-treat seizures.

  • Obsessive-Compulsive Disorder (OCD): Used under a humanitarian device exemption for chronic, severe cases.

  • Adaptive DBS (aDBS): Systems that sense real-time brain activity and automatically adjust stimulation levels.

  • Directional Leads: Electrodes that allow surgeons to "steer" current toward targets to minimize side effects.

  • Personalized Programming: Precise digital adjustment of electrical pulses tailored to the patient's brain signals.

  • Sensing Technology: Capability to record brain signals (local field potentials) to monitor disease progression.

  • Improved Battery Life: Advances in battery chemistry providing longer intervals between replacements.

  • Brain Surgery (Stage 1): Fine leads are placed in specific brain targets, often while the patient is awake to test for relief.

  • Testing: Surgeons use microelectrode recording to ensure the leads are in the optimal location.

  • Chest Surgery (Stage 2): The pulse generator (battery) is implanted under the skin near the collarbone.

  • Connection: Extension wires are tunneled under the skin to connect the chest device to the brain leads.

  • Closing: Small incisions are closed with sutures or surgical staples.

  • Hospital Stay: Most patients stay for 1–3 days for observation.

  • Honeymoon Effect: Temporary symptom relief may occur immediately from the surgery itself.

  • Device Activation: Official programming and device "turn-on" typically occurs 2–4 weeks after surgery.

  • Rechargeable Models: Newer 2026 models can last up to 15 years before needing replacement.

  • Non-Rechargeable Models: Standard batteries typically last between 3–5 years.

  • Brain Bleed: There is a 1–3% risk of a brain bleed or stroke during lead placement.

  • Infection: A 3–5% risk of infection exists at the incision sites or around the hardware.

  • Hardware Issues: Potential for lead migration, wire breakage, or skin erosion over the device.

  • Side Effects: Stimulation can sometimes cause temporary speech, balance, or mood changes.

  • Programming Time: It may take several months of adjustments to find the most effective settings.

  • Substantial reduction in the need for daily medications and their associated side effects.

  • Significant improvement in the ability to perform activities of daily living.

  • Continuous, 24-hour symptom control that does not "wear off" like oral medication.

  • Reversible and adjustable technology that can be updated as the condition changes.

  • Enhanced quality of life and independence for patients with chronic movement disorders.

Epilepsy Surgery
Epilepsy Surgery

Epilepsy surgery in 2026 is a specialized neurosurgical field focused on achieving seizure freedom or significant reduction through the removal or modulation of specific neural networks. As a primary intervention for drug-resistant epilepsy, this surgery moves beyond traditional medication management to address the mechanical and electrical source of the condition. By integrating robotic-assisted mapping and minimally invasive thermal therapies, 2026 protocols offer personalized solutions that prioritize the preservation of cognitive function and long-term quality of life.

  • Failure of two or more appropriately chosen anti-seizure medications to provide complete seizure control.

  • Documented drug-resistant epilepsy that significantly interferes with employment, education, or social independence.

  • Presence of focal seizures that consistently originate from a single, identifiable region of the brain.

  • Experiencing severe "drop attacks" or tonic-clonic seizures that pose a high risk of physical injury.

  • Side effects from high-dose medications that impair memory, mood, or overall daily functioning.

  • Clear evidence of a structural lesion, such as a focal cortical dysplasia or hippocampal sclerosis, on high-resolution imaging.

  • Mesial Temporal Lobe Epilepsy (MTLE), often characterized by hippocampal scarring and high surgical success rates.

  • Lesional epilepsy caused by cortical malformations, cavernomas, or low-grade tumors.

  • Generalized or multifocal epilepsy where neuromodulation is the safest and most effective option.

  • Lennox-Gastaut Syndrome or other severe pediatric epilepsy syndromes requiring disconnection procedures.

  • Refractory focal epilepsy located in non-eloquent areas of the brain that are safe for resection.

  • Pre-surgical Phase I evaluation including prolonged video-EEG monitoring to capture and map seizure activity.

  • Phase II intracranial monitoring using robotic-assisted SEEG electrodes to pinpoint the seizure focus with sub-millimeter accuracy.

  • Administration of general anesthesia or, in specific functional cases, an awake craniotomy to map language and motor centers.

  • Precise resection of the seizure-generating tissue or the thermal ablation of the focus using laser fibers.

  • For neuromodulation, the surgical implantation of leads into the brain or chest connected to an intelligent pulse generator.

  • Real-time intraoperative neuro-monitoring to ensure the total preservation of surrounding healthy brain tissue and critical pathways.

  • Laser Interstitial Thermal Therapy (LITT): Utilizing a thin laser fiber to destroy seizure-causing tissue via a tiny 2mm incision, eliminating the need for a traditional craniotomy.

  • Responsive Neurostimulation (RNS): Deploying a smart intracranial device that acts as a brain computer, detecting abnormal activity and delivering a corrective pulse before a seizure starts.

  • Robotic-Assisted Stereoelectroencephalography (SEEG): Using high-precision robotic arms to place deep brain electrodes for the most accurate 3D seizure mapping available in 2026.

  • 7-Tesla High-Field MRI: Employing ultra-high-resolution imaging to identify subtle structural abnormalities that were invisible on standard 2026 scanners.

  • Focused Ultrasound: Using non-invasive sound waves to target and ablate deep brain seizure foci without any surgical incisions.

  • Magnetoencephalography (MEG): Measuring the magnetic fields produced by brain activity to provide a detailed functional map of seizure-prone networks.

  • Extensive neuropsychological evaluation to establish a baseline for memory, language, and cognitive processing.

  • Functional MRI (fMRI) or WADA testing to determine which hemisphere of the brain dominates speech and motor control.

  • Nutritional and lifestyle optimization to stabilize systemic health and prepare the body for the recovery phase.

  • Collaborative consultation between the patient, neurosurgeon, and epileptologist to set realistic seizure-reduction goals.

  • Mapping of "eloquent" brain regions to ensure the surgical plan avoids areas critical for daily functioning.

  • Multi-day Video-EEG monitoring to confirm the clinical and electrical correlation of seizure events.

  • Positron Emission Tomography (PET) scans to identify areas of the brain with abnormal glucose metabolism related to epilepsy.

  • Single-Photon Emission Computed Tomography (SPECT) to visualize blood flow changes specifically during a seizure event.

  • Comprehensive 2026 genetic testing to identify underlying metabolic or genetic causes of drug resistance.

  • High-density EEG caps to provide a non-invasive, high-resolution topographical map of electrical spikes.

  • Success rates for becoming completely seizure-free reach up to 80% for temporal lobe resections in 2026.

  • Minimally invasive laser techniques reduce the hospital stay to a single day and minimize post-operative pain.

  • Neuromodulation devices like RNS and DBS offer a 75% or greater reduction in seizures for those not eligible for resection.

  • Targeted interventions significantly lower the risk of Sudden Unexpected Death in Epilepsy (SUDEP).

  • Early surgical intervention in 2026 is proven to prevent the cognitive decline associated with chronic, uncontrolled seizures.

  • Variable hospital stays ranging from 24 hours for laser procedures to 5 days for traditional resections.

  • Gradual resumption of physical activity, with most patients returning to light work or school within 2 to 4 weeks.

  • Continuous monitoring of mood and cognitive health through specialized 2026 post-surgical support programs.

  • Strict adherence to anti-seizure medication schedules during the initial 6 to 12 month brain-healing phase.

  • Regular follow-up with a dedicated epilepsy team to evaluate seizure control and adjust device settings if applicable.

  • Potential for achieving long-term seizure freedom, allowing for the restoration of driving privileges and occupational independence.

  • Gradual reduction or elimination of anti-seizure medications under strict medical supervision after a seizure-free period.

  • Dramatic improvement in overall mental health, including reductions in anxiety and depression related to seizure unpredictability.

  • Enhanced social participation and improved family dynamics due to the removal of the burden of daily seizures.

  • Lifetime surveillance through a Level 4 Epilepsy Center to ensure ongoing neurological health and wellness.

Gamma Knife Surgery (Radiosurgery)

Gamma Knife Surgery, or Stereotactic Radiosurgery (SRS), is a non-invasive treatment that uses roughly 200 pinpoint beams of gamma radiation to treat brain abnormalities without an incision. As of 2026, it remains the "gold standard" for small, deep-seated lesions.

  • Diagnosis of small to medium malignant brain metastases.

  • Presence of benign tumors like meningiomas or acoustic neuromas.

  • Chronic facial pain caused by Trigeminal Neuralgia.

  • Deep-seated Arteriovenous Malformations (AVMs) unsuitable for traditional surgery.

  • Functional disorders such as essential tremors or OCD.

  • Elekta Esprit: The newest generation platform offering sub-millimeter accuracy for complex cases.

  • Frameless Mask Options: Modern standards allow for mask-based treatments, enabling fractionated doses over several days.

  • Lightning Inverse Planning: Automated, real-time software that reduces planning time and human error.

  • Non-Invasive Approach: High-dose radiation delivered with surgical precision without a single scalp incision.

  • Brain Tumors: Malignant and benign growths located deep within the brain.

  • Vascular Malformations: Correcting blood vessel tangles (AVMs).

  • Nerve Disorders: Targeted treatment for the trigeminal nerve root.

  • Functional Issues: Neurological conditions impacting movement or behavior.

  • Tumor Control: Generally ranges between 85% and 95% for small tumors.

  • Acoustic Neuromas: Approximately 90% of patients see growth stop or shrink.

  • Trigeminal Neuralgia: About 90% of patients achieve significant pain relief within one year.

  • Quick Recovery: Most procedures are outpatient; patients typically return home the same day.

  • Activity Resumption: You can usually return to normal daily activities within 24 to 48 hours.

  • Post-Op Care: Monitoring for mild headaches, fatigue, or minor scalp irritation.

  • Long-term Follow-up: Periodic MRI scans to track the shrinkage or stabilization of the treated area.

  • No general anesthesia is required for most adult patients.

  • Eliminates the risks of infection and bleeding associated with open brain surgery.

  • Extremely high precision spares the surrounding healthy brain tissue.

  • Cost-effective compared to traditional neurosurgery due to shorter hospital stays.

Microvascular Decompression (MVD)

Microvascular Decompression (MVD) is a highly specialized neurosurgical procedure designed to resolve cranial nerve compression at the brainstem. In the 2026 clinical landscape, it is recognized as the definitive restorative treatment for conditions like Trigeminal Neuralgia and Hemifacial Spasm. By physically separating pulsating blood vessels from hypersensitive nerve tissue and inserting protective medical-grade buffers, MVD addresses the mechanical root cause of chronic facial pain and involuntary spasms, offering a long-term cure rather than temporary symptom management.

  • Sudden, electric-shock-like stabs of facial pain triggered by light touch, shaving, or applying makeup.

  • Excruciating pain in the jaw or cheek while eating, drinking, or speaking that has become resistant to medication.

  • Involuntary twitching of the eyelid or facial muscles that has progressed to the lower face and neck.

  • Intense, sharp pain in the back of the throat or ear canal when swallowing or clearing the throat.

  • Failure to achieve adequate relief from pharmacological treatments or side effects from high-dose nerve-stabilizing drugs.

  • A desire for a permanent surgical solution to avoid the nerve-damaging effects of repeated radiation or chemical injections.

  • Trigeminal Neuralgia (Type 1 and Type 2) caused by neurovascular conflict at the root entry zone.

  • Hemifacial Spasm resulting from arterial compression of the seventh cranial nerve.

  • Glossopharyngeal Neuralgia causing severe paroxysmal pain in the tonsillar fossa or pharynx.

  • Geniculate Neuralgia, a rare condition involving deep ear pain and sensory nerve compression.

  • Recurrent facial pain syndromes where previous non-microvascular interventions have failed to provide lasting relief.

  • Pre-operative 2026 high-resolution FIESTA or 3D-CISS MRI sequences to visualize the exact vessel-nerve conflict.

  • Administration of general anesthesia with integrated intraoperative neuromonitoring (IONM) of the hearing and facial nerves.

  • Creation of a small, precise opening (retrosigmoid craniotomy) roughly the size of a postage stamp behind the ear.

  • Microsurgical dissection using high-definition visualization to identify the offending artery or vein pressing on the nerve.

  • Gentle repositioning of the vessel and the insertion of a permanent, non-reactive Teflon felt cushion to act as a barrier.

  • Multi-layer closure of the site using advanced 2026 surgical sealants to ensure a watertight seal of the cranial space.

  • Endoscopic-Assisted Microsurgery: Utilizing ultra-thin endoscopes to visualize hidden "around-the-corner" vascular loops that a traditional microscope might miss.

  • Real-Time Brainstem Auditory Evoked Potentials (BAEP): Continuous monitoring of hearing signals during surgery to provide the surgeon with instant feedback and preserve auditory function.

  • Stealth Neuronavigation: Using GPS-guided digital overlays to plan the most direct and least invasive surgical corridor to the brainstem.

  • Medical-Grade Teflon Buffers: Utilizing advanced, biocompatible materials designed to remain in place for decades without causing an inflammatory response.

  • Fused 3D Image Guidance: Integrating MRI and CT data into the surgical oculars, allowing the surgeon to see through bone and tissue layers digitally.

  • Laser-Assisted Micro-Dissection: Using low-heat lasers for the bloodless separation of delicate arachnoid tissues surrounding the compressed nerve.

  • Comprehensive dental evaluation to rule out localized tooth or jaw issues that may mimic facial pain.

  • Detailed baseline hearing test (audiogram) to establish a reference point for post-operative monitoring.

  • Optimization of blood pressure to ensure vascular stability before, during, and after the intracranial procedure.

  • Education on the 2026 "rapid recovery" protocol, which emphasizes early mobilization and specialized pain management.

  • Assessment of current nerve-stabilizing medications to create a post-operative weaning plan as pain subsides.

  • High-field (3T or 7T) MRI with 2026 neurovascular protocols to confirm the presence of a compressing blood vessel.

  • Magnetic Resonance Angiography (MRA) to map the arterial branches near the brainstem and identify the offending vessel.

  • Trigeminal Reflex Testing to assess the physiological integrity of the nerve pathways.

  • Routine 2026 cardiac and hematologic clearance to ensure the patient is a safe candidate for general anesthesia.

  • High-resolution CT of the temporal bone to plan the exact craniotomy entry point and avoid critical venous sinuses.

  • Success rates for immediate pain relief in 2026 exceed 90% for typical Trigeminal Neuralgia.

  • MVD is the only treatment that preserves natural nerve function rather than intentionally damaging or numbing the nerve.

  • The use of permanent cushions prevents the "short-circuiting" effect of pulsating vessels, leading to the lowest recurrence rates in neurosurgery.

  • Advanced intraoperative monitoring has reduced the risk of major complications, such as hearing loss, to less than 2-3% in specialized centers.

  • Patients often wake up from surgery completely free of the "electric" pain they have suffered from for years.

  • A typical 2026 hospital stay of 24 to 48 hours to ensure normal recovery from anesthesia and monitoring of fluid balance.

  • Immediate resolution of facial spasms or "shocks" is expected, though some mild numbness or tingling may temporarily occur.

  • Gradual resumption of soft foods and normal speaking as the facial triggers are no longer present.

  • Restriction of heavy lifting or strenuous exertion for 4 to 6 weeks to allow the surgical site and scalp to heal fully.

  • Short-term use of specialized anti-nausea and non-opioid pain medications during the first 72 hours post-op.

  • Permanent cessation of electric-shock facial pain, allowing for a return to normal social activities, eating, and grooming.

  • Systematic weaning from long-term anti-seizure or nerve-pain medications under the supervision of a neurologist.

  • Significant improvement in psychological well-being and elimination of the "fear of the next attack."

  • Annual 2026 digital follow-ups to track long-term wellness and ensure the continued success of the decompression.

  • Resumption

Spinal Cord Stimulator (SCS) Implantation

Spinal Cord Stimulator (SCS) Implantation is a specialized two-stage surgical process that utilizes a small device to send mild electrical pulses directly to the spinal cord. These pulses interfere with pain signals before they reach the brain, effectively "masking" chronic pain and replacing it with a soothing sensation.

SCS is primarily recommended for chronic neuropathic (nerve) pain that has not responded to conservative treatments or previous surgeries. Key indications include:

  • Failed Back Surgery Syndrome (FBSS): Persistent pain following one or more spinal surgeries.

  • Complex Regional Pain Syndrome (CRPS): A chronic condition typically affecting a limb after an injury.

  • Peripheral Neuropathy: Nerve damage often caused by diabetes or other underlying conditions.

  • Chronic Arachnoiditis: Inflammation and scarring of the spinal nerve linings.

  • Intractable Pain: Severe pain that has not been relieved by physical therapy, injections, or medication for at least 6 months.

  • Trial Phase (Stage 1): A "test drive" where temporary leads are inserted to evaluate if the therapy reduces pain by at least 50%.

  • Permanent Implantation (Stage 2): The surgical placement of permanent leads and a generator (IPG) under the skin.

  • Rechargeable Systems: Advanced 2026 models can last 10 to 25 years but require regular wireless charging.

  • Non-rechargeable Systems: Simpler devices that typically require surgical battery replacement every 2 to 5 years.

  • Burst or High-Frequency Stimulation: Modern programming modes that provide pain relief without the "tingling" sensation (paresthesia).

  • Trial Access: Under local anesthesia, temporary leads are inserted into the epidural space using a needle, and an external battery is worn for 7–10 days.

  • Permanent Surgical Access: For the permanent stage, an incision is made to place the leads precisely near the spinal cord and another to create a "pocket" for the generator.

  • Generator Placement: The pulse generator—similar to a pacemaker—is implanted under the skin, usually in the upper buttocks or abdomen.

  • Programming: The surgeon and device representative calibrate the remote control to ensure the electrical pulses are targeting the exact area of pain.

  • Closure: The incisions are closed with sutures, and the system is tested one final time before the patient leaves the operating room.

  • Fasting: Patients are typically required to fast for 8–12 hours before the permanent implantation.

  • Psychological Evaluation: Most insurance and clinical protocols require a brief evaluation to ensure the patient is a good candidate for the therapy.

  • Medical Clearances: Standard blood tests, ECG, and chest X-rays are performed to assess overall surgical health.

  • Medication Review: Adjusting or pausing blood thinners or anti-inflammatory drugs as directed by the surgical team.

  • MRI Scan: Essential to ensure there is enough space in the spinal canal for the leads and to identify any obstructions.

  • CT Scan: Provides detailed imaging of the bony anatomy to guide the placement of the leads.

  • X-rays (Fluoroscopy): Used during the procedure to provide real-time guidance for the precise positioning of the electrodes.

  • Trial Success Log: A documented period of 7–10 days where the patient tracks pain levels to confirm the effectiveness of the device.

  • Hospital Stay: Typically performed as a same-day outpatient procedure taking 1 to 3 hours.

  • Activity Restrictions: For the first 2 to 6 weeks, patients must avoid bending, lifting (over 5 lbs), and twisting to prevent the leads from shifting.

  • Short-Term Recovery: Most patients return to sedentary work within 1 to 2 weeks.

  • Long-Term Outlook: Full tissue healing and lead stabilization generally take 6 to 8 weeks, after which the patient can adjust settings using a handheld remote.

  • Significant Pain Reduction: Offers a 50% to 90% reduction in chronic nerve pain for many patients.

  • Reduced Medication Dependency: Often allows patients to significantly decrease their reliance on opioid pain medications.

  • Reversible Technology: Unlike fusion or other permanent changes to anatomy, the system can be turned off or removed if necessary.

  • Improved Quality of Life: Enables patients to return to daily activities, sleep better, and maintain higher physical stamina.

Peripheral Bypass Surgery (Leg Arteries)

Peripheral Bypass Surgery (also known as Lower Extremity Bypass) is a major vascular procedure used to reroute blood flow around a blocked artery in the leg. It is the primary surgical treatment for advanced Peripheral Artery Disease (PAD) to restore circulation, relieve severe pain, and prevent tissue death or amputation. By creating a new pathway for blood, the surgery ensures that oxygen and nutrients reach the lower leg and foot.

  • Critical Limb Ischemia: Severe leg pain that occurs even at rest, often waking you up at night.

  • Non-Healing Ulcers: Sores or wounds on the toes, feet, or legs that do not heal despite standard wound care.

  • Gangrene: Visible tissue death in the foot or toes due to a total lack of blood supply.

  • Failed Conservative Care: When walking exercise programs, smoking cessation, and medications have failed to improve symptoms.

  • Ineligible for Stenting: When the blockage is too long, too hard (calcified), or located in an area where a stent would easily fail or kink.

  • Autologous Vein Bypass (Gold Standard): Using the patient's own healthy vein (usually the Great Saphenous Vein) to create the new bridge. This has the highest long-term success rate.

  • Synthetic Graft Bypass: Utilizing a medical-grade plastic tube (such as PTFE or Dacron) if the patient's natural veins are too small or diseased.

  • In-Situ Bypass: Leaving the patient's vein in its natural place but stripping the internal valves and connecting it to the blocked artery above and below.

  • Reversed Vein Bypass: Harvesting the vein, turning it around so the valves don't block blood flow, and stitching it into the new position.

  • Composite Graft: Using a combination of a natural vein and a synthetic tube for very long bypasses that extend from the groin to the ankle.

  • Mapping: The surgeon uses pre-operative imaging to identify the exact "inflow" (healthy artery above) and "outflow" (healthy artery below) for the graft.

  • Incisions: Two main incisions are made—one in the groin to access the femoral artery and another near the knee or ankle to access the target artery.

  • Graft Preparation: The surgeon either harvests the patient's saphenous vein or prepares the synthetic graft for implantation.

  • Tunneling: The graft is carefully "tunneled" through the tissues, either under the skin or deep beneath the muscles, to bypass the clogged arterial segment.

  • Anastomosis: Using extremely fine sutures and magnification, the surgeon stitches the graft into the healthy sections of the artery at both ends.

  • Flow Verification: A completion angiogram (dye test) or Doppler ultrasound is performed in the operating room to ensure blood is pulsing through the new bypass without leaks or kinks.

  • Vascular Mapping: A CT Angiogram (CTA) or MR Angiogram (MRA) is mandatory to provide a detailed "road map" of the blockages.

  • Vein Ultrasound: A specialized ultrasound to check if the leg veins are large and healthy enough to be used as a graft.

  • Smoking Cessation: Patients must stop smoking for at least 4 weeks prior; nicotine causes the new graft to clog almost immediately and prevents wound healing.

  • Medication Review: Coordination of blood thinners and diabetic medications to ensure the body is ready for a long surgical procedure.

  • Fasting (NPO): No food or drink for 8–12 hours before the procedure to ensure safety under general or spinal anesthesia.

  • CT or MR Angiography: To visualize the exact length and location of the arterial blockages.

  • Duplex Ultrasound: To evaluate the quality of the "donor" veins and the speed of blood flow in the remaining healthy arteries.

  • Ankle-Brachial Index (ABI): A baseline measurement of the blood pressure in the legs compared to the arms to assess the severity of the PAD.

  • Cardiac Clearance: Because PAD often coexists with heart disease, an EKG or stress test is often required to ensure the heart can handle the surgery.

  • Hospital Stay: Typically 3 to 7 days; nurses will check the pulses in your foot every hour for the first 24 hours to ensure the graft is open.

  • Early Mobilization: You will be encouraged to stand and take short walks within 24–48 hours to prevent blood clots and pneumonia.

  • Leg Elevation: Keeping the leg elevated when sitting is critical for the first 4 weeks to manage the significant swelling that follows the return of blood flow.

  • Lifelong Medication: Daily aspirin and usually a second blood thinner (like Clopidogrel) are required indefinitely to keep the graft from clotting.

  • Surveillance: Regular Duplex Ultrasound scans are required every 3–6 months for the first two years to monitor the bypass and catch any narrowing early.

  • Limb Salvage: Effectively prevents the need for amputation in patients with critical limb ischemia and gangrene.

  • Dramatic Pain Relief: Restoring blood flow immediately eliminates the severe "rest pain" caused by a lack of oxygen to the tissues.

  • Heals Chronic Wounds: Provides the necessary circulation for long-standing ulcers and sores to finally heal.

  • Restores Mobility: Allows patients to walk significantly further without the cramping and weakness associated with PAD.

  • Long-Term Durability: When performed with a natural vein, the bypass can remain open and functional for many years, significantly improving quality of life.

Carotid Endarterectomy

Carotid Endarterectomy (CEA) is a major surgical procedure used to remove fatty deposits (plaque) from the carotid artery in the neck. This is the primary surgical method for stroke prevention when the artery is significantly narrowed (stenosis). By cleaning out the artery, the surgery restores healthy blood flow to the brain and removes the source of potential blood clots.

  • Significant Stenosis: When the carotid artery is blocked by more than 70%, even if you have not experienced symptoms.

  • Symptomatic Narrowing: When the artery is blocked by more than 50% and you have already experienced a stroke or a Transient Ischemic Attack (TIA/mini-stroke).

  • TIA (Mini-Stroke): Warning signs such as sudden numbness, facial drooping, or speech difficulty that resolve within 24 hours but indicate high stroke risk.

  • Amaurosis Fugax: Temporary loss of vision in one eye, often described as a "shade being pulled down," caused by a small piece of plaque blocking a retinal artery.

  • Failed Medical Management: When plaque continues to build up despite the use of blood thinners and high-dose cholesterol medications.

  • Traditional CEA: The standard method where the artery is opened vertically to peel out the plaque and then closed with a patch to widen the vessel.

  • Eversion CEA: A technique where the internal carotid artery is cut at its base, turned inside out to remove the plaque, and then reattached to the main artery.

  • CEA under Local/Regional Anesthesia: Performing the surgery while the patient is awake to allow the surgeon to monitor neurological function (speech and grip) in real-time.

  • CEA with Shunting: Using a temporary plastic tube to reroute blood to the brain while the artery is being cleaned, ensuring continuous oxygen delivery.

  • Patch Angioplasty: The use of a synthetic (Dacron) or biological (vein) patch during closure to prevent the artery from narrowing again.

  • Exposure: A vertical incision (approx. 7–10 cm) is made along the side of the neck, following a natural skin crease to minimize scarring.

  • Control: The surgeon identifies the common, internal, and external carotid arteries and places temporary surgical clamps to pause blood flow to the treatment site.

  • Plaque Removal: A vertical cut is made in the artery, and the surgeon meticulously "peels" out the yellow, waxy plaque from the inner lining of the vessel.

  • Widening: To ensure the artery remains wide and open, a patch made of synthetic material or a vein harvested from the leg is stitched over the incision.

  • Flushing and Restoration: The surgeon carefully flushes the artery to remove any debris before removing the clamps and restoring full blood flow to the brain.

  • Closure: A small drain may be left in the neck for 24 hours to prevent fluid buildup, and the skin is closed with fine sutures or surgical glue.

  • Vascular Mapping: Diagnosis is confirmed via Carotid Ultrasound, CT Angiography (CTA), or MR Angiography (MRA) to determine the exact location and "hardness" of the plaque.

  • Cardiac Clearance: Because carotid disease often coexists with heart disease, a cardiology evaluation is often required to ensure the heart is stable for surgery.

  • Medication Review: Patients are typically instructed to continue taking aspirin but may need to adjust other blood thinners under surgical guidance.

  • Fasting (NPO): No food or drink for 8–12 hours before the procedure to ensure safety during anesthesia.

  • Carotid Duplex Ultrasound: A non-invasive test that uses sound waves to measure the speed of blood flow and the degree of narrowing.

  • CT Angiography (CTA): Provides a detailed 3D map of the neck arteries and identifies calcified (hard) vs. soft plaque.

  • Electrocardiogram (EKG): To assess heart rhythm and check for underlying coronary artery disease before the stress of surgery.

  • Neurological Assessment: A baseline exam of speech, vision, and motor strength to allow for accurate post-operative comparisons.

  • Hospital Stay: Typically 24 to 48 hours; intensive blood pressure monitoring is critical during the first 12 hours to prevent stress on the repair.

  • Immediate Recovery: Soreness and numbness around the neck incision are common and can last for several weeks or months.

  • Activity Resumption: Most patients return to normal light activities within 1 to 2 weeks. Driving is usually restricted for one week until full neck rotation is comfortable.

  • Lifelong Medication: Daily Aspirin and Statins (cholesterol medication) are mandatory to prevent new plaque from forming in the repaired artery.

  • Long-Term Surveillance: A follow-up Carotid Ultrasound is typically performed at 1 month, 6 months, and then annually to ensure the artery remains open.

  • Significant Stroke Prevention: Reduces the risk of a future stroke on the operated side by over 60–80% compared to medication alone.

  • Restores Cerebral Blood Flow: Increases the volume of oxygenated blood reaching the brain, which can improve cognitive clarity and reduce "mini-stroke" symptoms.

  • Long-Term Durability: The artery remains open in approximately 95% of cases over a 10-year period.

  • Minimal Scarring: The use of skin-crease incisions and fine suturing techniques ensures a subtle cosmetic result once fully healed.

Laser Varicose Vein Treatment

Laser Varicose Vein Treatment, scientifically known as Endovenous Laser Ablation (EVLA) or EVLT, is a minimally invasive procedure used to seal shut diseased veins. Unlike traditional "vein stripping," this approach uses targeted laser heat to collapse the vein from the inside, naturally rerouting blood flow to healthier veins. It is considered the modern gold standard for treating the underlying cause of painful, bulging varicose veins.

  • Chronic Venous Insufficiency: When leaky valves in the leg veins cause blood to pool, leading to leg heaviness, aching, and swelling.

  • Bulging Varicose Veins: Large, twisted veins on the surface of the legs that are often painful or cause skin irritation.

  • Venous Ulcers: Open sores near the ankles caused by long-term high pressure in the leg veins.

  • Phlebitis: Recurrent inflammation or painful "clots" in the superficial veins.

  • Skin Changes: Brownish discoloration (hyperpigmentation) or thickening of the skin near the ankles, which indicates advanced vein disease.

  • Endovenous Laser Ablation (EVLA): The primary method using a specialized laser fiber to deliver heat energy directly to the vein wall.

  • Radiofrequency Ablation (RFA): A similar technique that uses high-frequency electrical energy instead of light to generate heat and close the vein.

  • Ultrasound-Guided Sclerotherapy: Often used as a secondary treatment to close smaller "branch" veins that remain after the main vein is sealed.

  • VenaSeal (Medical Adhesive): A non-thermal alternative that uses a specialized medical "glue" to seal the vein without the need for heat or tumescent numbing.

  • Clarivein (MOCA): A mechanical-chemical approach that uses a rotating wire and a liquid sclerosant to close the vein without heat.

  • Mapping: Under ultrasound guidance, the surgeon identifies the exact "leaky" segment of the Great Saphenous Vein or Small Saphenous Vein.

  • Access: A tiny needle is used to create a small "stab" entry point, usually near the knee or ankle.

  • Fiber Placement: A thin laser fiber is threaded through a catheter and positioned at the top of the diseased vein, near the groin or behind the knee.

  • Tumescent Anesthesia: A large volume of numbing fluid (lidocaine and saline) is injected around the vein. This "cushion" numbs the area and protects the skin and nerves from the laser's heat.

  • Laser Activation: As the surgeon slowly withdraws the fiber, the laser emits intense light energy that collapses and seals the vein wall.

  • Completion: The fiber is removed, and since the entry point is so small, no stitches are required—only a simple adhesive bandage.

[Image showing the steps of EVLT from catheter insertion to vein closure]

  • Venous Doppler Ultrasound: A mandatory "mapping" scan to identify the location of leaky valves and measure the diameter of the veins.

  • Compression Fitting: Patients should be measured for medical-grade compression stockings to be worn immediately after the procedure.

  • Attire: Wear loose-fitting clothing or shorts to the clinic to accommodate the bandages and stockings.

  • Medication: Most patients can continue their normal medications, as the procedure is performed under local rather than general anesthesia.

  • Duplex Ultrasound: The primary tool used to confirm "reflux" (blood flowing the wrong way) and plan the surgical path.

  • Visual Assessment: To document the presence of edema (swelling), skin changes, or ulcers for insurance and clinical staging.

  • Ankle-Brachial Index (ABI): Occasionally performed to ensure the arterial circulation in the legs is healthy before applying high-pressure compression.

  • Immediate Mobilization: This is a "walk-in, walk-out" procedure; you are required to walk for 15–20 minutes immediately after the session.

  • Compression Therapy: High-pressure stockings must be worn 24/7 for the first 3–7 days, and then during the day for another 1–2 weeks to ensure the vein remains closed.

  • Activity: Normal daily activities and walking can resume immediately. However, heavy weightlifting and hot baths should be avoided for 2 weeks.

  • Healing Sensations: It is normal to feel a "tightness" or a pulling sensation along the inner thigh for 5–10 days as the vein naturally turns into scar tissue.

  • Follow-up Scan: An ultrasound is typically performed within the first week to confirm the vein is successfully occluded and to rule out any deep vein clots.

  • Extremely High Success Rate: Over 95% of treated veins remain permanently closed and are eventually absorbed by the body.

  • No Surgical Incisions: Eliminates the need for large cuts, preventing scarring and significantly reducing the risk of infection.

  • Minimal Downtime: Most patients return to work the following day with very little discomfort.

  • Symptom Relief: Provides rapid relief from the "heavy leg" sensation, aching, and nighttime cramping associated with venous disease.

  • Cosmetic Improvement: Bulgy surface veins often shrink or disappear once the high-pressure "root cause" is sealed shut.

Embolectomy/Thrombectomy

Embolectomy and Thrombectomy are emergency surgical procedures used to remove a physical blockage from a blood vessel to restore blood flow. While these terms are often used interchangeably, an embolectomy specifically removes an embolus (a clot that traveled from elsewhere in the body), whereas a thrombectomy removes a thrombus (a clot that formed locally within the vessel). These are critical interventions used to prevent permanent tissue death, organ failure, or limb loss.

  • Acute Limb Ischemia: A sudden loss of blood flow to a leg or arm, characterized by the "6 Ps": Pain, Pallor (pale skin), Pulselessness, Paresthesia (numbness), Paralysis, and Perishing Cold.

  • Ischemic Stroke: When a large blood vessel in the brain is blocked, leading to sudden facial drooping, arm weakness, or speech difficulties.

  • Massive Pulmonary Embolism (PE): A large clot lodged in the lung arteries that causes severe shortness of breath, low blood pressure, and strain on the heart.

  • Failed Thrombolysis: When "clot-busting" medications (like tPA) are either unsafe for the patient or have failed to dissolve a large, stubborn blockage.

  • Organ Ischemia: Sudden blockage of the arteries supplying the kidneys or intestines (Mesenteric Ischemia), which is a surgical emergency.

  • Surgical (Open) Embolectomy: The traditional method where the vessel is opened manually to remove the blockage under direct vision.

  • Mechanical (Endovascular) Thrombectomy: A minimally invasive approach using specialized catheters to retrieve or dissolve the clot from within the vessel.

  • Aspiration Thrombectomy: Using high-powered suction catheters to "vacuum" the clot out of the artery or vein.

  • Stent-Retriever Thrombectomy: A mesh-like device is expanded into the clot, snagging it so it can be safely pulled out of the body; this is the gold standard for many stroke treatments.

  • Fogarty Balloon Catheterization: A classic surgical technique where a balloon is passed beyond the clot, inflated, and withdrawn to sweep the blockage out.

  • Rapid Access: For a surgical embolectomy, an incision is made directly over the affected artery (often in the groin). For mechanical procedures, a small puncture is made in the groin or wrist.

  • Navigation: Using real-time X-ray guidance (fluoroscopy), the surgeon steers a catheter to the exact location of the blockage.

  • Clot Extraction:
    Open: The surgeon opens the vessel, inserts a Fogarty catheter past the clot, inflates the balloon, and pulls the blockage out through the incision.
    Mechanical: A stent-retriever or suction device is deployed to capture and remove the thrombus through the catheter.

  • Flow Assessment: Contrast dye is injected to perform an angiogram, ensuring that blood flow is fully restored to all downstream branches.

  • Vessel Repair: In open surgery, the artery is meticulously sewn shut. In endovascular cases, the catheter is removed, and the small puncture site is closed with a pressure device or a special "plug."

  • Emergency Mapping: Rapid diagnosis via CT Angiogram (CTA) or Duplex Ultrasound is mandatory to locate the exact position and size of the clot.

  • Immediate Anticoagulation: Patients are typically started on high-dose Heparin immediately to prevent the existing clot from growing while they wait for surgery.

  • Vital Stabilization: Managing blood pressure and oxygen levels to keep the "starved" tissue alive as long as possible before the procedure.

  • Fasting (NPO): While these are emergencies, patients are kept from eating or drinking as soon as the diagnosis is suspected to prepare for potential general anesthesia.

  • CT Angiography (CTA): The most common test to provide a high-definition 3D map of the blocked vessels.

  • Duplex Ultrasound: A quick, bedside tool used to visualize clots in the limbs or neck.

  • Blood Panels: To check clotting times (PT/INR), kidney function (for contrast safety), and "markers" of muscle damage (CPK).

  • Electrocardiogram (EKG): To determine if a heart rhythm issue, such as Atrial Fibrillation, was the source of the wandering clot (embolus).

  • Hospital Stay: Typically 3 to 7 days, often starting in a specialized Intensive Care Unit (ICU) for close monitoring.

  • Frequent Checks: Nurses will perform hourly pulse checks, skin temperature assessments, and neurological exams to ensure the vessel remains open.

  • Fasciotomy Care: In severe cases of limb swelling (Compartment Syndrome), patients may have surgical incisions in their muscles that require specialized wound care.

  • Lifelong Anticoagulation: Most patients will require long-term blood thinners (like Eliquis or Warfarin) to prevent new clots from forming.

  • Rehabilitation: Physical therapy is often necessary to recover muscle strength or coordination lost during the time the tissue was without blood flow.

  • Life and Limb Salvage: Effectively prevents the need for amputation or the death of vital organ tissue.

  • Rapid Recovery of Function: In stroke cases, successful thrombectomy can lead to the immediate return of speech or movement.

  • Prevents Heart Strain: Removing a massive pulmonary embolism immediately reduces the workload on the heart, preventing right-sided heart failure.

  • High Technical Success: Modern mechanical devices allow surgeons to reach and remove clots in very small or deep vessels that were previously unreachable.

Arteriovenous Fistula Surgery

An Arteriovenous (AV) Fistula is a surgically created connection between an artery and a vein, designed to provide a reliable, long-term access point for hemodialysis. It remains the "gold standard" for vascular access because it is constructed entirely from the patient's own biological tissue. Compared to synthetic grafts or temporary catheters, an AV fistula offers a significantly lower risk of infection, fewer instances of clotting, and the longest functional lifespan, making it the foundation of high-quality renal care.

  • End-Stage Renal Disease (ESRD): When kidney function has declined to the point where regular hemodialysis is necessary to filter waste from the blood.

  • Long-Term Dialysis Planning: For patients expected to be on dialysis for several years, as the fistula provides the most durable access.

  • Vessel Health: When a patient has healthy, adequately sized veins and arteries in the arm that can support the increased blood flow.

  • Infection Prevention: For individuals who are highly susceptible to infections or have had complications with synthetic grafts or central venous catheters.

  • Home Hemodialysis: It is often the preferred access for patients performing their own treatments at home due to its reliability and safety profile.

  • Radiocephalic Fistula: Created at the wrist by joining the radial artery and cephalic vein; usually the first choice to preserve upper arm veins.

  • Brachiocephalic Fistula: Created at the elbow; often used when wrist veins are too small or have been damaged by previous medical procedures.

  • Brachiobasilic Transposition: A more complex surgery where a deep vein in the upper arm is moved closer to the skin to make it reachable for needles.

  • Endovascular (Percutaneous) Fistula: A modern, "no-scalpel" approach using radiofrequency energy to join vessels through a tiny needle stick, leaving no surgical scar.

  • Gracz Fistula: A specific type of elbow connection involving the perforating vein, often used when other elbow options are limited.

  • Vessel Mapping: Before surgery, an ultrasound is used to find the healthiest artery and vein to ensure the highest chance of success.

  • Anesthesia: The procedure is performed under local anesthesia with light sedation, or a regional "block" that numbs the entire arm.

  • The Connection: The surgeon makes a small incision and carefully stitches the side of the vein to the side (or end) of the artery.

  • Immediate Flow Check: Once the connection is made, the surgeon can usually feel a "thrill" (vibration), indicating arterial blood is successfully entering the vein.

  • Incision Closure: The skin is closed with small sutures or surgical glue, and a light protective dressing is applied.

  • Endovascular Alternative: If using a "no-scalpel" system, the vessels are fused using a specialized catheter under X-ray or ultrasound guidance.

  • Vein Preservation: The chosen arm must be "protected"—meaning no blood draws, IVs, or blood pressure checks should be performed on that arm once a fistula is planned.

  • Early Planning: Specialists recommend creating the fistula 3 to 6 months before you expect to start dialysis to ensure it is ready for use on day one.

  • Diagnostic Imaging: Undergoing a formal "vessel map" ultrasound to confirm the diameter and depth of the target vessels.

  • Fasting (NPO): Depending on the type of sedation used, you may be asked to fast for 8 hours prior to the procedure.

  • Duplex Ultrasound: To measure the size of the arteries and veins and check for any existing blockages or clots.

  • Allen's Test: A manual clinical test to ensure the hand has adequate blood supply from both the radial and ulnar arteries.

  • Blood Panels: Routine labs to check for anemia, electrolyte balance, and clotting factors before the minor surgical intervention.

  • Cardiac Evaluation: In some cases, to ensure the heart can handle the increased workload created by the new "shunt" in the circulation.

  • The "Ripening" Phase: A fistula needs 6 to 12 weeks to mature. During this time, the vein thickens and toughens so it can safely handle dialysis needles.

  • Fistula Exercises: Patients are often taught "stress ball" or "grip" exercises to strengthen the arm and encourage the vein to enlarge.

  • Daily Monitoring: Patients are taught to touch their fistula daily to feel for a constant vibration (the thrill) and listen for the whooshing sound (the bruit).

  • Arm Protection: 1. Never let anyone take blood pressure on the fistula arm. 2. Never let anyone draw blood or start an IV in that arm. 3. Avoid wearing tight jewelry or restrictive sleeves.

  • Activity: Once the initial surgical wound heals, patients can return to normal activities, though they should avoid sleeping with the fistula arm tucked under their body.

  • Superior Durability: Once matured, a fistula can last for many years, often outperforming all other types of dialysis access.

  • Lower Infection Rates: Since no foreign material is implanted, the risk of life-threatening bloodstream infections is significantly reduced.

  • High Blood Flow: It provides the robust, high-volume blood flow necessary for the dialysis machine to clean the blood effectively.

  • Better Health Outcomes: Studies consistently show that patients with a functioning AV fistula have better overall survival rates on dialysis.

  • Natural Healing: Because it is made of your own tissue, the site heals itself after each dialysis session, reducing the need for long-term maintenance.

Top Doctors at Apollo Hospital, Financial District in India

Dr P Banu Teja Reddy
Urologist, Kidney Transplant Surgeon
Apollo Hospital, Financial District, Hyderabad
11+years experience
Dr Rahul Lakshminarayanan
Vascular Surgeon
Apollo Hospital, Financial District, Hyderabad
8+years experience
Dr Srikanth Reddy S
Dr Srikanth Reddy S
Spine Surgeon, Neurosurgeon
Apollo Hospital, Financial District, Hyderabad
20+years experience

May we help you?

Enter digits only (6-15 digits). We'll add your country code.